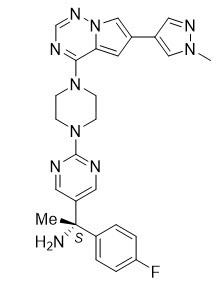
Limitations of Use:
AYVAKIT is not recommended for the treatment of patients with AdvSM with platelet counts of less than 50 × 109/L [see Warnings and Precautions (5.1)].
Limitations of Use:
AYVAKIT is not recommended for the treatment of patients with ISM with platelet counts of less than 50 × 109/L [see Warnings and Precautions (5.1)].
Gastrointestinal Stromal Tumors
Intracranial hemorrhage occurred in 3 of 267 patients (1.1%). Two (0.7%) of the events were Grade ≥ 3 and resulted in discontinuation of study drug. Events of intracranial hemorrhage occurred in a range from 1.7 months to 19.3 months after initiating AYVAKIT.
Advanced Systemic Mastocytosis
In patients with AdvSM who received AYVAKIT at 200 mg daily, intracranial hemorrhage occurred in 2 of 75 patients (2.7%) who had platelet counts ≥ 50 × 109/L prior to initiation of therapy and in 3 of 80 patients (3.8%) regardless of platelet counts.
In patients with AdvSM, a platelet count must be performed prior to initiating therapy; AYVAKIT is not recommended in patients with AdvSM with platelet counts < 50 × 109/L. Following treatment initiation, platelet counts must be performed every 2 weeks for the first 8 weeks regardless of baseline platelet count. After 8 weeks of treatment, monitor platelet counts every 2 weeks (or more frequently as clinically indicated) if values are less than 75 × 109/L, every 4 weeks if values are between 75 and 100 × 109/L, and as clinically indicated if values are greater than 100 × 109/L.
Manage platelet counts of < 50 × 109/L by treatment interruption or dose-reduction of AYVAKIT. Platelet support may be necessary [see Dosage and Administration (2.5)]. Dose-interruptions and dose-reductions for thrombocytopenia occurred in 20% and 22% of AYVAKIT-treated patients, respectively. Thrombocytopenia was generally reversible by reducing or interrupting AYVAKIT.
Indolent Systemic Mastocytosis
Cognitive adverse reactions occurred in 7.8% of patients with ISM who received AYVAKIT + best supportive care versus 7% of patients who received placebo + best supportive care in the PIONEER study; <1% were Grade 3. The median time to onset of the first cognitive adverse reaction was 2.3 months (range: 0 to 5.4 months). Median time to improvement to Grade 1 or complete resolution was 2.1 months (range: 0.4 to 2.1 months).
Gastrointestinal Stromal Tumors
Cognitive adverse reactions occurred in 41% of 601 patients with GIST who received AYVAKIT; 5% were Grade ≥ 3. Memory impairment occurred in 21% of patients; <1% of these events were Grade 3. Cognitive disorder occurred in 12% of patients; 1.2% of these events were Grade 3. Confusional state occurred in 6% of patients; <1% of these events were Grade 3. Amnesia occurred in 3% of patients; <1% of these events were Grade 3. Somnolence and speech disorder occurred in 2% of patients; none of these events were Grade 3. Other events occurred in less than 2% of patients.
The median time to onset of the first cognitive adverse reaction was 8.4 weeks (range: 1 day to 4 years). Among patients who experienced a cognitive effect of Grade 2 or worse (impacting activities of daily living), the median time to improvement to Grade 1 or complete resolution was 7.9 weeks. Overall, 2.7% of all patients who received AYVAKIT required permanent discontinuation for a cognitive adverse reaction, 13.5% required a dosage interruption, and 8.5% required dose reduction.
Advanced Systemic Mastocytosis
Cognitive adverse reactions occurred in 28% of 148 patients with AdvSM who received AYVAKIT; 3% were Grade ≥ 3. Memory impairment occurred in 16% of patients; all events were Grade 1 or 2. Cognitive disorder occurred in 10% of patients; <1% of these events were Grade 3. Confusional state occurred in 6% of patients; <1% of these events were Grade 3. Other events occurred in less than 2% of patients.
The median time to onset of the first cognitive adverse reaction was 13.3 weeks (range: 1 day to 1.8 years). Among patients who experienced a cognitive effect of Grade 2 or worse (impacting activities of daily living), the median time to improvement to Grade 1 or complete resolution was 8.1 weeks. Overall, 2% of all patients who received AYVAKIT required permanent discontinuation for a cognitive adverse reaction, 8.1% required a dosage interruption, and 8.8% required dose reduction.
Gastrointestinal Stromal Tumors
Unresectable or Metastatic GIST
The safety of AYVAKIT in patients with unresectable or metastatic GIST was evaluated in NAVIGATOR [see Clinical Studies (14.1)]. The trial excluded patients with history of cerebrovascular accident or transient ischemic attacks, known risk of intracranial bleeding, and metastases to the brain. Patients received AYVAKIT 300 mg or 400 mg orally once daily (n = 204). Among patients receiving AYVAKIT, 56% were exposed for 6 months or longer and 44% were exposed for greater than one year.
The median age of patients who received AYVAKIT was 62 years (range: 29 to 90 years), 60% were <65 years, 62% were male, and 69% were White. Patients had received a median of 3 prior kinase inhibitors (range: 0 to 7).
Serious adverse reactions occurred in 52% of patients receiving AYVAKIT. Serious adverse reactions occurring in ≥1% of patients who received AYVAKIT were anemia (9%), abdominal pain (3%), pleural effusion (3%), sepsis (3%), gastrointestinal hemorrhage (2%), vomiting (2%), acute kidney injury (2%), pneumonia (1%), and tumor hemorrhage (1%). Fatal adverse reactions occurred in 3.4% of patients. Fatal adverse reactions that occurred in more than one patient were sepsis and tumor hemorrhage (1% each).
Permanent discontinuation due to adverse reactions occurred in 16% of patients who received AYVAKIT. Adverse reactions requiring permanent discontinuation in more than one patient were fatigue, abdominal pain, vomiting, sepsis, anemia, acute kidney injury, and encephalopathy.
Dosage interruptions due to an adverse reaction occurred in 57% of patients who received AYVAKIT. Adverse reactions requiring dosage interruption in >2% of patients who received AYVAKIT were anemia, fatigue, nausea, vomiting, hyperbilirubinemia, memory impairment, diarrhea, cognitive disorder, and abdominal pain.
Dose reduction due to an adverse reaction occurred in 49% of patients who received AYVAKIT. Median time to dose reduction was 9 weeks. Adverse reactions requiring dosage reduction in more than 2% of patients who received AYVAKIT were fatigue, anemia, hyperbilirubinemia, memory impairment, nausea, and periorbital edema.
The most common adverse reactions (≥ 20%) were edema, nausea, fatigue/asthenia, cognitive impairment, vomiting, decreased appetite, diarrhea, increased lacrimation, abdominal pain, constipation, rash, dizziness, and hair color changes. Table 4 summarizes the adverse reactions observed in NAVIGATOR.
Table 4: Adverse Reactions (≥ 10%) in Patients with GIST Receiving AYVAKIT in NAVIGATOR| Adverse Reactions Per National Cancer Institute Common Terminology Criteria for Adverse Events (CTCAE) version 4.03 and 5.0 | AYVAKIT
N=204 |
|---|
All Grades
% | Grade ≥ 3
% |
|---|
| General |
| Edema Edema includes face swelling, conjunctival edema, eye edema, eyelid edema, orbital edema, periorbital edema, face edema, mouth edema, pharyngeal edema, peripheral edema, edema, generalized edema, localized edema, peripheral swelling, testicular edema. | 72 | 2 |
| Fatigue/asthenia | 61 | 9 |
| Pyrexia | 14 | 0.5 |
| Gastrointestinal |
| Nausea | 64 | 2.5 |
| Vomiting | 38 | 2 |
| Diarrhea | 37 | 4.9 |
| Abdominal pain Abdominal pain includes abdominal pain, upper abdominal pain, abdominal discomfort, lower abdominal pain, abdominal tenderness, and epigastric discomfort. | 31 | 6 |
| Constipation | 23 | 1.5 |
| Dyspepsia | 16 | 0 |
| Nervous System |
| Cognitive impairment Cognitive impairment includes memory impairment, cognitive disorder, confusional state, disturbance in attention, amnesia, mental impairment, mental status changes, encephalopathy, dementia, abnormal thinking, mental disorder, and retrograde amnesia. | 48 | 4.9 |
| Dizziness | 22 | 0.5 |
| Headache | 17 | 0.5 |
| Sleep disorders Sleep disorders includes insomnia, somnolence, and sleep disorder. | 16 | 0 |
| Taste effects Taste effects include dysgeusia and ageusia. | 15 | 0 |
| Mood disorders Mood disorders includes agitation, anxiety, depression, depressed mood, dysphoria, irritability, mood altered, nervousness, personality change, and suicidal ideation. | 13 | 1 |
| Metabolism and nutrition |
| Decreased appetite | 38 | 2.9 |
| Eye |
| Increased lacrimation | 33 | 0 |
| Skin and subcutaneous tissue |
| Rash Rash includes rash, rash maculo-papular, rash erythematous, rash macular, rash generalized, and rash papular. | 23 | 2.1 |
| Hair color changes | 21 | 0.5 |
| Alopecia | 13 | 0 |
| Respiratory, thoracic and mediastinal |
| Dyspnea | 17 | 2.5 |
| Pleural effusion | 12 | 2 |
| Investigations |
| Weight decreased | 13 | 1 |
Clinically relevant adverse reactions occurring in <10% of patients were:
Vascular: hypertension (8%)
Endocrine: thyroid disorders (hyperthyroid, hypothyroid) (3%)
Skin and subcutaneous: palmar-plantar erythrodysesthesia (1%)
Table 5 summarizes the laboratory abnormalities observed in NAVIGATOR.
Table 5: Select Laboratory Abnormalities (≥ 10%) Worsening from Baseline in Patients with GIST Receiving AYVAKIT in NAVIGATOR| Laboratory Abnormality | AYVAKIT The denominator used to calculate the rate varied from 154 to 201 based on the number of patients with a baseline value and at least one post-treatment value.
N=204 |
|---|
All Grades
(%) | Grade ≥ 3
(%) |
|---|
| Hematology |
| Decreased hemoglobin | 81 | 28 |
| Decreased leukocytes | 62 | 5 |
| Decreased neutrophils | 43 | 6 |
| Decreased platelets | 27 | 0.5 |
| Increased INR | 24 | 0.6 |
| Increased activated partial thromboplastin time | 13 | 0 |
| Chemistry |
| Increased bilirubin | 69 | 9 |
| Increased aspartate aminotransferase | 51 | 1.5 |
| Decreased phosphate | 49 | 13 |
| Decreases potassium | 34 | 6 |
| Decreased albumin | 31 | 2 |
| Decreased magnesium | 29 | 1 |
| Increased creatinine | 29 | 0 |
| Decreased sodium | 28 | 7 |
| Increased alanine aminotransferase | 19 | 0.5 |
| Increased alkaline phosphatase | 14 | 1 |
Advanced Systemic Mastocytosis
The safety of AYVAKIT in patients with AdvSM was evaluated in EXPLORER and PATHFINDER [see Clinical Studies (14.2)]. Patients received a starting dose of AYVAKIT ranging from 30 mg to 400 mg orally once daily (n = 131), including 80 patients who received the recommended starting dose of 200 mg once daily. Among patients receiving AYVAKIT, 70% were treated for 6 months or longer and 37% were exposed for greater than one year.
The median age of patients who received AYVAKIT was 68 years (range: 31 to 88 years), 38% were <65 years, 57% were male, and 88% were White.
Serious adverse reactions occurred in 34% of patients receiving the recommended starting dose of 200 mg once daily and in 50% of patients receiving AYVAKIT at all doses. Serious adverse reactions occurring in ≥1% of patients who received AYVAKIT were anemia (5%), subdural hematoma (4%), pleural effusion, ascites and pneumonia (3% each), acute kidney injury, gastrointestinal hemorrhage, intracranial hemorrhage, encephalopathy, gastric hemorrhage, large intestine perforation, pyrexia, and vomiting (2% each). Fatal adverse reactions occurred in 2.5% of patients receiving the recommended starting dose of 200 mg once daily and in 5.3% of patients receiving AYVAKIT at all doses. No specific adverse reaction leading to death was reported in more than one patient.
Permanent discontinuation due to adverse reactions occurred in 10% of patients receiving the recommended starting dose of 200 mg once daily and in 15% of patients who received AYVAKIT at all doses. Of patients receiving 200 mg once daily, subdural hematoma was the only adverse reaction requiring permanent discontinuation in more than one patient.
Dosage interruptions due to an adverse reaction occurred in 60% of patients receiving the recommended starting dose of 200 mg once daily and in 67% of patients who received AYVAKIT at all doses. Adverse reactions requiring dosage interruption in >2% of patients who received AYVAKIT at 200 mg once daily were thrombocytopenia, neutropenia, neutrophil count decreased, platelet count decreased, anemia, white blood cell decreased, cognitive disorder, blood alkaline phosphatase increased, and edema peripheral.
Dose reduction due to an adverse reaction occurred in 68% of patients receiving the recommended starting dose of 200 mg once daily and 70% of patients who received AYVAKIT at all doses. Median time to dose reduction was 1.7 months. Adverse reactions requiring dosage reduction in more than 2% of patients who received AYVAKIT at 200 mg once daily were thrombocytopenia, neutropenia, edema peripheral, neutrophil count decreased, platelet count decreased, periorbital edema, cognitive disorder, anemia, fatigue, arthralgia, blood alkaline phosphatase increased, and white blood cell count decreased.
The most common adverse reactions (≥ 20%) at all doses were edema, diarrhea, nausea, and fatigue/asthenia. Table 6 summarizes the adverse reactions observed in EXPLORER and PATHFINDER.
Table 6: Adverse Reactions (≥ 10%) in Patients with AdvSM Receiving AYVAKIT in EXPLORER and PATHFINDER| Adverse Reactions Per National Cancer Institute Common Terminology Criteria for Adverse Events (CTCAE) version 4.03 and 5.0 | AYVAKIT (200 mg once daily)
N=80 |
|---|
All Grades
% | Grade ≥ 3
% |
|---|
| General |
| Edema Edema includes face swelling, eyelid edema, orbital edema, periorbital edema, face edema, peripheral edema, edema, generalized edema, and peripheral swelling. | 79 | 5 |
| Fatigue/asthenia | 23 | 4 |
| Gastrointestinal |
| Diarrhea | 28 | 1 |
| Nausea | 24 | 1 |
| Vomiting | 18 | 3 |
| Abdominal pain Abdominal pain includes abdominal pain, upper abdominal pain, and abdominal discomfort. | 14 | 1 |
| Constipation | 11 | 0 |
| Nervous system |
| Headache | 15 | 0 |
| Cognitive effects Cognitive effects include memory impairment, cognitive disorder, confusional state, delirium, and disorientation. | 14 | 1 |
| Taste effects Taste effects include dysgeusia. | 13 | 0 |
| Dizziness | 13 | 0 |
| Musculoskeletal and connective tissue |
| Arthralgia | 10 | 1 |
| Respiratory, thoracic and mediastinal |
| Epistaxis | 11 | 0 |
Clinically relevant adverse reactions occurring in <10% of patients were:
Cardiac: cardiac failure (2.5%), and cardiac failure congestive (1.3%)
Gastrointestinal: ascites (5%), gastrointestinal hemorrhage (1.3%), and large intestine perforation (1.3%)
Hepatobiliary: cholelithiasis (1.3%)
Infections and infestations: upper respiratory tract infection (6%), urinary tract infection (6%), and herpes zoster (2.5%)
Vascular: flushing (3.8%), hypertension (3.8%), hypotension (3.8%), and hot flush (2.5%)
Nervous: insomnia (6%)
Musculoskeletal and connective tissue: pain in extremity (6%)
Respiratory, thoracic and mediastinal: dyspnea (9%), and cough (2.5%)
Skin and subcutaneous tissue: rash
Grouped terms
(8%), alopecia (9%), pruritus (8%), and hair color changes (6%)
Metabolism and nutrition: decreased appetite (8%)
Eye: lacrimation increased (9%)
Laboratory abnormality: decreased phosphate (9%)
Rash includes rash and rash maculo-papular
Table 7 summarizes the laboratory abnormalities observed in EXPLORER and PATHFINDER.
Table 7: Select Laboratory Abnormalities (≥ 10%) Worsening from Baseline in Patients with AdvSM Receiving AYVAKIT in EXPLORER and PATHFINDER| Laboratory Abnormality | AYVAKIT (200 mg once daily)
N=80 |
|---|
All Grades
(%) | Grade ≥ 3
(%) |
|---|
| Hematology |
| Decreased platelets | 64 | 21 |
| Decreased hemoglobin | 55 | 23 |
| Decreased neutrophils | 54 | 25 |
| Decreased lymphocytes | 34 | 11 |
| Increased activated partial thromboplastin time | 14 | 1 |
| Increased lymphocytes | 10 | 0 |
| Chemistry |
| Decreased calcium | 50 | 3 |
| Increased bilirubin | 41 | 3 |
| Increased aspartate aminotransferase | 38 | 1 |
| Decreased potassium | 26 | 4 |
| Increased alkaline phosphatase | 24 | 5 |
| Increased creatinine | 20 | 0 |
| Increased alanine aminotransferase | 18 | 1 |
| Decreased sodium | 18 | 1 |
| Decreased albumin | 15 | 1 |
| Decreased magnesium | 14 | 1 |
| Increased potassium | 11 | 0 |
Other Clinically Relevant Adverse Reactions in <10% of patients
In the pooled GIST and AdvSM safety populations, photosensitivity occurred in 2.5% of patients [see Warnings and Precautions (5.3)].
Indolent Systemic Mastocytosis
The safety of AYVAKIT in patients with ISM was evaluated in the randomized, blinded, placebo-controlled portion of PIONEER (Part 2) [see Clinical Studies (14.3)]. Patients received AYVAKIT 25 mg orally once daily with best supportive care (n = 141) or placebo once daily with best supportive care (n = 71).
Serious adverse reactions occurred in 1 patient (0.7%) who received AYVAKIT due to pelvic hematoma.
Permanent discontinuation of AYVAKIT due to an adverse reaction occurred in 1 patient (0.7%) due to dyspnea and dizziness.
Dosage interruptions of AYVAKIT due to an adverse reaction occurred in 5% of patients. Adverse reactions which required dosage interruption included dizziness, blood alkaline phosphatase increased, dyspnea, face edema, pelvic hematoma, liver transaminase increased and respiratory tract infection (1 patient each).
Table 8 summarizes the frequency of adverse reactions in the PIONEER study. The most common adverse reactions (≥ 10%) in the AYVAKIT group were eye edema, dizziness, peripheral edema and flushing. Of all adverse reactions, 55% were Grade 1, 38% were Grade 2 and 7% were Grade 3. Among patients with edema adverse reactions, 95% were Grade 1 and 5% were Grade 2. Among patients with hemorrhage adverse reactions, 86% were Grade 1 and 14% were Grade 2.
Table 8: Adverse Reactions Occurring in AYVAKIT-Treated Patients with Indolent Systemic Mastocytosis During PIONEER Trial (Part 2) | Adverse Reactions Adverse reactions that occurred in ≥5% of AYVAKIT-treated patients and ≥2% more than placebo-treated patients. ,Per National Cancer Institute Common Terminology Criteria for Adverse Events (CTCAE) version 5.0 | AYVAKIT (25 mg once daily) + BSC
N=141
% | Placebo + BSC
N=71
% |
|---|
| Abbreviations: BSC=best supportive care |
| Eye edema Eye edema includes periorbital edema, eye edema, swelling of eyelid, orbital edema, eye swelling, eyelid edema and eyelid ptosis. | 13 | 7 |
| Dizziness | 13 | 10 |
| Peripheral edema | 12 | 6 |
| Flushing | 11 | 4 |
| Respiratory tract infection Respiratory tract infection includes pneumonia, upper respiratory tract infection, bronchitis and respiratory tract infection. | 8 | 1 |
| Face edema | 7 | 1 |
| Rash | 6 | 4 |
| Liver transaminase increased | 6 | 3 |
| Insomnia | 6 | 3 |
| Hematoma Hematoma includes contusion, hematoma and pelvic hematoma. | 6 | 1 |
| Blood alkaline phosphatase increased | 6 | 1 |
| Hemorrhage Hemorrhage includes epistaxis, gingival bleeding, hematochezia, rectal hemorrhage, retinal hemorrhage. | 5 | 3 |
Clinically relevant adverse reactions occurring in <5% of patients were:
Skin and subcutaneous tissue: photosensitivity (2.8%)
The long-term safety of AYVAKIT in patients with ISM was evaluated in the open-label extension portion of the PIONEER study. Across the study, 226 patients received a 25 mg once daily dose for a median duration of 3 years (range 0.7 – 67.2 months). Of these, 65 patients had their dose increased to 50 mg once daily [see Clinical Studies (14.3)] and have been on the 50 mg dose for a median duration of 1 year (range 0.1 – 30.3 months).
Strong and Moderate CYP3A Inhibitors
Coadministration of AYVAKIT with a strong or moderate CYP3A inhibitor increases avapritinib plasma concentrations [see Clinical Pharmacology (12.3)], which may increase the incidence and severity of adverse reactions of AYVAKIT. Avoid coadministration of AYVAKIT with strong or moderate CYP3A inhibitors. If coadministration of AYVAKIT with a moderate CYP3A inhibitor cannot be avoided, reduce the dose of AYVAKIT [see Dosage and Administration (2.6)].
Strong and Moderate CYP3A Inducers
Coadministration of AYVAKIT with a strong or moderate CYP3A inducer decreases avapritinib plasma concentrations [see Clinical Pharmacology (12.3)], which may decrease efficacy of AYVAKIT. Avoid coadministration of AYVAKIT with strong or moderate CYP3A inducers.
Risk Summary
Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1)], AYVAKIT can cause fetal harm when administered to a pregnant woman. There are no available data on AYVAKIT use in pregnant women. Oral administration of avapritinib to pregnant rats during the period of organogenesis was teratogenic and embryotoxic at exposure levels approximately 31.4, 6.3 and 2.7 times the human exposure based on AUC at the 25 mg, 200 mg and 300 mg dose, respectively (see Data). Advise pregnant women of the potential risk to a fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data
Animal Data
In a reproductive toxicity study, administration of avapritinib to rats during the period of organogenesis resulted in decreased fetal body weights, post-implantation loss, and increases in visceral (hydrocephaly, septal defect, and stenosis of the pulmonary trunk) and skeletal (sternum) malformations at doses greater than or equal to 10 mg/kg/day (approximately 31.4, 6.3 and 2.7 times the human exposure based on AUC at the 25 mg, 200 mg and 300 mg dose, respectively).
Risk Summary
There are no data on the presence of avapritinib or its metabolites in human milk or the effects of avapritinib on the breastfed child or milk production. Because of the potential for serious adverse reactions in breastfed children, advise women not to breastfeed during treatment with AYVAKIT and for 2 weeks following the final dose.
Pregnancy Testing
Verify the pregnancy status of females of reproductive potential prior to initiating AYVAKIT [see Use in Specific Populations (8.1)].
Contraception
AYVAKIT can cause fetal harm when administered to pregnant women [see Use in Specific Populations (8.1)].
Females
Advise females of reproductive potential to use effective contraception during treatment with AYVAKIT and for 6 weeks after the final dose. See Drug Interactions (7.2) for recommendations on the concomitant use of AYVAKIT with hormonal contraception containing ethinyl estradiol.
Males
Advise males with female partners of reproductive potential to use effective contraception during treatment with AYVAKIT and for 6 weeks after the final dose.
Infertility
Females
Based on findings from animal studies, AYVAKIT may impair female fertility. These findings were not reversible within a two month recovery period [see Nonclinical Toxicology (13.1)].
Males
Based on findings from animal studies, AYVAKIT may impair male fertility. These findings were not reversible within a two month recovery period [see Nonclinical Toxicology (13.1)].
Exposure-Response Relationships
Gastrointestinal Stromal Tumors or Advanced Systemic Mastocytosis
Based on the data from four clinical trials conducted in patients with advanced malignancies and AdvSM, including NAVIGATOR, EXPLORER, and PATHFINDER, higher exposure was associated with increased risk of Grade ≥ 3 related adverse effects, any Grade pooled cognitive adverse effects, Grade ≥ 2 pooled cognitive adverse effects, and Grade ≥ 2 pooled edema adverse effects over the dose range of 30 mg to 400 mg (0.1 to 1.33 times the recommended dose for GIST and 0.15 to 2 times the recommended dose for AdvSM) once daily.
Based on exposure and efficacy data from EXPLORER and PATHFINDER (n=84), higher avapritinib exposure was associated with faster time to response over the dose range of 30 mg to 400 mg (0.15 to 2 times the recommended dose for AdvSM) once daily.
Cardiac Electrophysiology
The effect of AYVAKIT on the QTc interval was evaluated in an open-label, single-arm study in 27 patients administered doses of 300 mg or 400 mg (12 to 16 times the lowest recommended 25 mg dose, 1.33 times the highest recommended 300 mg dose) once daily. No large mean increase in QTc (i.e.> 20 ms) was detected at the mean steady state maximum concentration (Cmax) of 899 ng/mL.
Absorption
The median time to peak concentration (Tmax) ranged from 2 to 4 hours following single doses of avapritinib.
Effect of Food
The Cmax of avapritinib was increased by 59% and the AUC0-INF was increased by 29% when AYVAKIT was taken with a high-calorie, high-fat meal (approximately 909 calories, 58 grams carbohydrate, 56 grams fat and 43 grams protein) compared to those in the fasted state.
Distribution
The mean (CV %) apparent volume of distribution of avapritinib is 1310 L (51.5%) at 300 mg in patients with GIST, 1900 L (43.2%) at 200 mg in patients with AdvSM, and 1400 L (59.1%) at 25 mg in patients with ISM. In vitro protein binding of avapritinib is 98.8% and is independent of concentration. The blood-to-plasma ratio is 0.95.
Elimination
The mean plasma elimination half-life of avapritinib was 32 to 57 hours in patients with GIST, 20 to 39 hours in patients with AdvSM, and 38 to 45 hours in patients with ISM. The steady state mean (CV%) apparent oral clearance of avapritinib is 21.8 L/h (54.9%) at 300 mg in patients with GIST, 40.3 L/h (86.0%) at 200 mg in patients with AdvSM, and 21.6 L/h (58.1%) at 25 mg in patients with ISM.
Metabolism
Avapritinib is primarily metabolized by CYP3A4, CYP3A5 and to a lesser extent by CYP2C9 in vitro. Following a single oral dose of approximately 310 mg of radiolabeled avapritinib to healthy subjects, unchanged avapritinib (49%) and its metabolites M690 (hydroxy glucuronide; 35%) and M499 (oxidative deamination; 14%) were the major circulating compounds. The formation of the glucuronide M690 is catalyzed mainly by UGT1A3. Following oral administration of AYVAKIT 300 mg once daily in patients, the steady state AUC of M499 is approximately 80% of the AUC of avapritinib. M499 is not likely to contribute to efficacy at the recommended dose of avapritinib.
Excretion
Following a single oral dose of approximately 310 mg of radiolabeled avapritinib to healthy subjects, 70% of the radioactive dose was recovered in feces (11% unchanged) and 18% in urine (0.23% unchanged).
Specific Populations
No clinically significant differences in the pharmacokinetics of avapritinib were observed based on age (18 to 90 years), sex, race (White, Black, or Asian), body weight (39.5 to 156.3 kg), mild to moderate (CLcr 30 to 89 mL/min estimated by Cockcroft-Gault) renal impairment, or mild (total bilirubin ≤ ULN and AST > ULN or total bilirubin > 1 to 1.5 times ULN and any AST) to moderate (total bilirubin > 1.5 to 3 times ULN and any AST) hepatic impairment. In a dedicated hepatic impairment study following a single oral dose administration of 100 mg avapritinib, the mean unbound AUC was 61% higher in subjects with severe hepatic impairment (Child-Pugh Class C) as compared to matched healthy subjects with normal hepatic function. The effect of severe renal impairment (CLcr 15 to 29 mL/min) and end-stage renal disease (CLcr < 15 mL/min) on the pharmacokinetics of avapritinib is unknown.
Drug Interaction Studies
Clinical Studies and Model-Informed Approaches
Effect of Strong and Moderate CYP3A Inhibitors on Avapritinib: Coadministration of AYVAKIT 300 mg once daily with itraconazole 200 mg once daily (a strong CYP3A inhibitor) is predicted to increase avapritinib AUC by 600% at steady state.
Coadministration of AYVAKIT 300 mg once daily with fluconazole 200 mg once daily (a moderate CYP3A inhibitor) is predicted to increase avapritinib AUC by 210% at steady state [see Dosage and Administration (2.6), Drug Interactions (7.1)].
Effect of Strong and Moderate CYP3A Inducers on Avapritinib: Coadministration of AYVAKIT 400 mg as a single dose with rifampin 600 mg once daily (a strong CYP3A inducer) decreased avapritinib Cmax by 74% and AUC0-INF by 92%.
Coadministration of AYVAKIT 300 mg once daily with efavirenz 600 mg once daily (a moderate CYP3A inducer) is predicted to decrease avapritinib Cmax by 55% and AUC by 62% at steady state [see Drug Interactions (7.1)].
Effect of Acid-Reducing Agents on Avapritinib: No clinically significant differences in the pharmacokinetics of avapritinib were identified when coadministered with gastric acid reducing agents.
Effect of Avapritinib on Hormonal Oral Contraceptives: In a drug-drug interaction study of 15 subjects, coadministration of AYVAKIT 25 mg once daily with an oral contraceptive (levonorgestrel 0.15 mg/ethinyl estradiol 0.03 mg) resulted in a mean ethinyl estradiol AUC ratio of 1.15 (90% confidence interval [CI]: 1.04, 1.28) and a mean ethinyl estradiol Cmax ratio of 1.46 (90% CI: 1.17, 1.81) relative to participants administered the oral contraceptive alone. This increase in ethinyl estradiol Cmax may lead to an increased risk of ethinyl estradiol-related adverse events.
Effect of Avapritinib on CYP3A Substrates: In a drug-drug interaction study in 10 patients, coadministration of AYVAKIT 300 mg once daily with oral midazolam (a sensitive CYP3A substrate) resulted in a mean midazolam AUC ratio of 1.51 (90% CI: 1.17, 1.93) and a mean Cmax ratio of 1.20 (90% CI: 0.87, 1.66). Similar drug interaction effect is predicted with coadministration of AYVAKIT 200 mg once daily in patients with GIST. No clinically significant drug interaction is predicted with coadministration of AYVAKIT in patients with AdvSM or ISM.
In Vitro Studies
Cytochrome P450 (CYP) Enzymes: Avapritinib is an inhibitor of CYP2C9. Avapritinib is not an inhibitor of CYP1A2, CYP2B6, CYP2C8, CYP2C19, or CYP2D6.
Avapritinib is not an inducer of CYP1A2 or CYP2B6. Avapritinib is a substrate of CYP3A.
M499 is an inhibitor of CYP3A, CYP2C8, or CYP2C9. M499 is not an inhibitor of CYP1A2, CYP2B6, CYP2C19, or CYP2D6.
Transporter Systems: Avapritinib is an inhibitor of P-glycoprotein (P-gp), intestinal BCRP, MATE1, MATE2-K, and BSEP, but not an inhibitor of OATP1B1, OATP1B3, OAT1, OAT3, OCT1, or OCT2. Avapritinib is not a substrate of P-gp or BCRP, OAT1, OAT3, OCT1, OCT2, OATP1B1, OATP1B3, MATE1, MATE2-K and BSEP. The effect of M499 on transporter systems is unknown.
Patients with GIST Harboring a PDGFRA Exon 18 Mutation
Patients with unresectable or metastatic GIST harboring a PDGFRA exon 18 mutation were identified by local or central assessment using a PCR- or NGS-based assay. The assessment of efficacy was based on a total of 43 patients, including 38 patients with PDGFRA D842V mutations. The median duration of follow up for patients with PDGFRA exon 18 mutations was 10.6 months (range: 0.3 to 24.9 months).
The study population characteristics were median age of 64 years (range: 29 to 90 years), 67% were male, 67% were White, 93% had an ECOG PS of 0-1, 98% had metastatic disease, 53% had largest target lesion >5 cm, and 86% had prior surgical resection. The median number of prior kinase inhibitors was 1 (range: 0 to 5).
Efficacy results in patients with GIST harboring PDGFRA exon 18 mutations including the subgroup of patients with PDGFRA D842V mutations enrolled in NAVIGATOR are summarized in Table 10.
Table 10: Efficacy Results for Patients with GIST Harboring PDGFRA Exon 18 Mutations in NAVIGATOR| Efficacy Parameter | PDGFRA exon 18 Exon 18 mutations other than D842V included in this population are: deletion of D842_H845 (n=3); D842Y (n=1); and deletion of D842_H845 with insertion of V (n=1).
N = 43 | PDGFRA D842V
N = 38 |
|---|
| Abbreviations: CI=confidence interval; NR=not reached |
| Overall Response Rate (95% CI) | 84% (69%, 93%) | 89% (75%, 97%) |
| Complete Response, n (%) | 3 (7%) | 3 (8%) |
| Partial Response, n (%) | 33 (77%) | 31 (82%) |
| Duration of Response | n=36 | n=34 |
| Median in months (range) | NR (1.9, 20.3) | NR (1.9, 20.3) |
| Patients with DOR ≥ 6-months, n (%) 11 patients with an ongoing response were followed < 6 months from onset of response. | 22 (61%) | 20 (59%) |
Intracranial Hemorrhage
Advise patients to contact their healthcare provider immediately if experiencing neurological signs and symptoms that may be associated with intracranial hemorrhage (i.e., severe headache, vomiting, drowsiness, dizziness, confusion, slurred speech, or paralysis) [see Warnings and Precautions (5.1)].
Inform patients with AdvSM of the need to monitor platelet counts before and during treatment [see Warnings and Precautions (5.1)].
Cognitive Effects
Advise patients and caretakers to notify their healthcare provider if they experience new or worsening cognitive symptoms. Advise patients not to drive or operate hazardous machinery if they are experiencing cognitive adverse reactions [see Warnings and Precautions (5.2)].
Photosensitivity
Inform patients that there is a potential risk of photosensitivity reactions with AYVAKIT. Advise patients to limit direct ultraviolet exposure by using sunscreen and protective clothing during treatment with AYVAKIT [see Warnings and Precautions (5.3)].
Embryo-Fetal Toxicity
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.4), Use in Specific Populations (8.1)].
Advise females of reproductive potential to use effective contraception during treatment with AYVAKIT and for 6 weeks after the final dose [see Drug Interactions (7.2), Use in Specific Populations (8.3)].
Advise males with female partners of reproductive potential to use effective contraception during treatment with AYVAKIT and for 6 weeks after the final dose [see Use in Specific Populations (8.3), Nonclinical Toxicology (13.1)].
Lactation
Advise women not to breastfeed during treatment with AYVAKIT and for 2 weeks following the final dose [see Use in Specific Populations (8.2)].
Infertility
Advise females of reproductive potential that AYVAKIT may impair fertility at 200 mg or 300 mg [see Use in Specific Populations (8.3), Nonclinical Toxicology (13.1)]. Advise males of reproductive potential that AYVAKIT may decrease sperm production at 200 mg or 300 mg [see Use in Specific Populations (8.3), Nonclinical Toxicology (13.1)].
Drug Interactions
Advise patients and caregivers to inform their healthcare provider of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products [see Drug Interactions (7.1)].
Administration
Advise patients to take AYVAKIT on an empty stomach, at least 1 hour before or 2 hours after a meal [see Dosage and Administration (2.1)].
Manufactured for:
Blueprint Medicines Corporation, Cambridge, MA 02139, USA