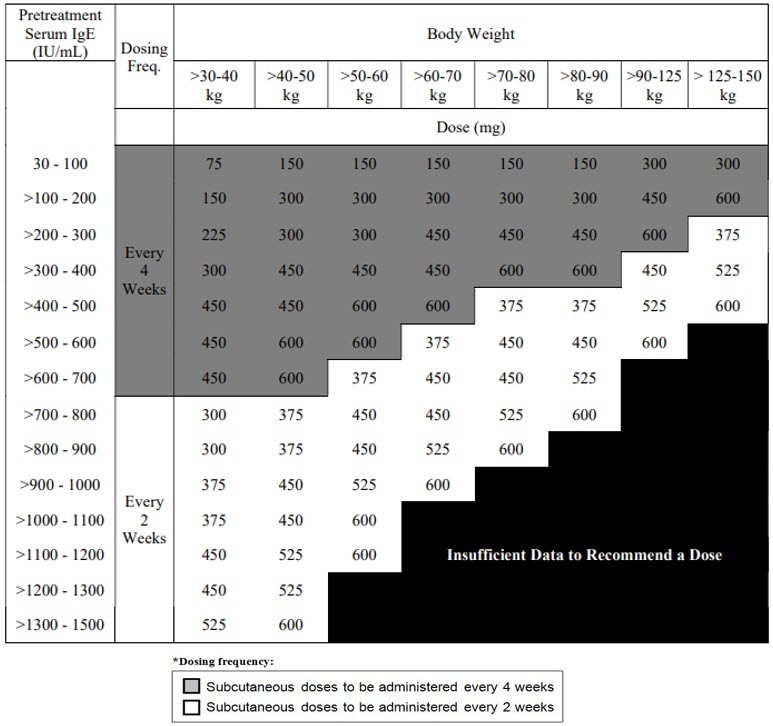
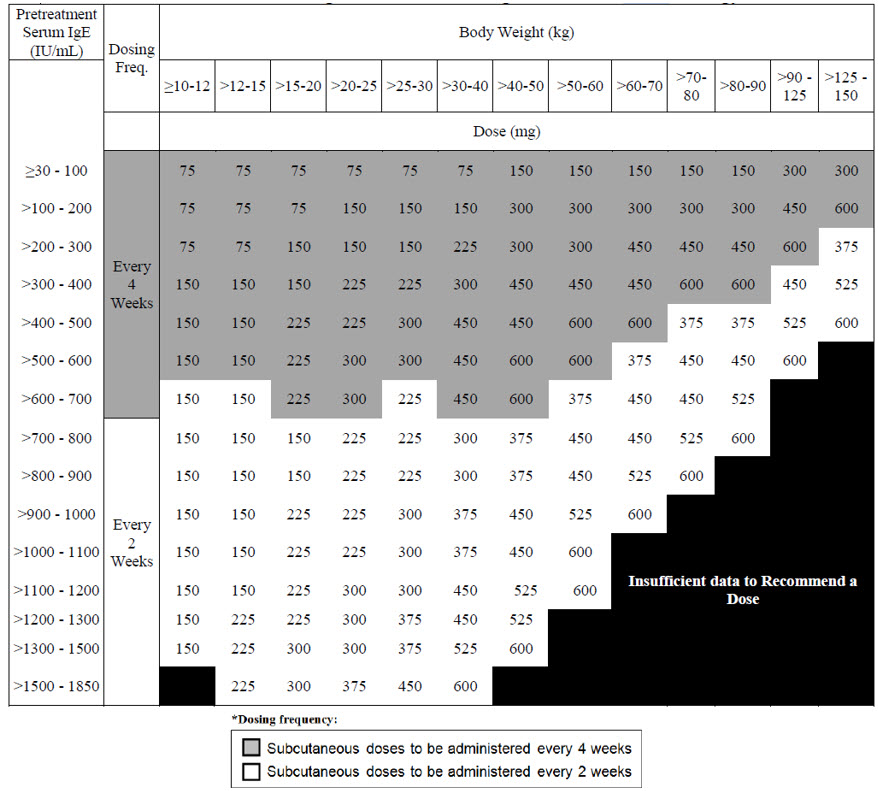
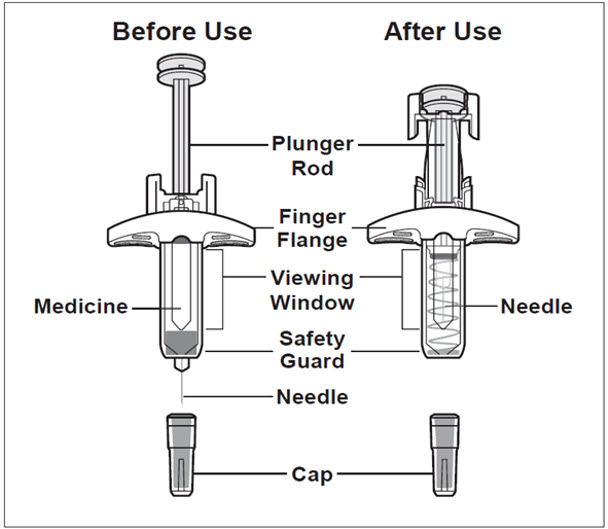
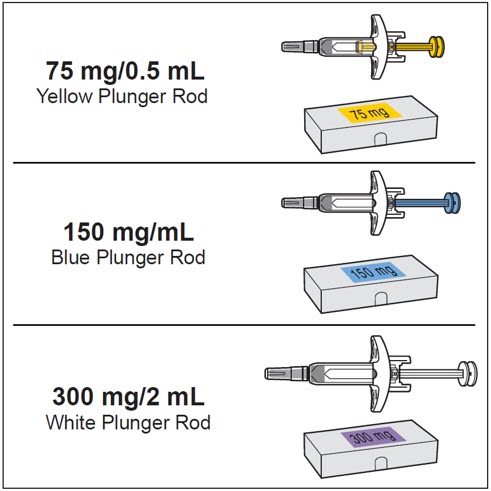
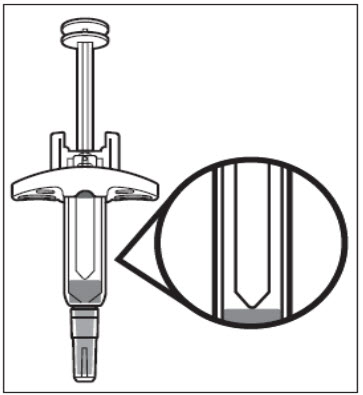
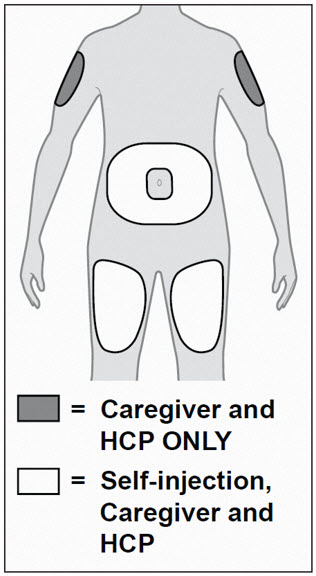
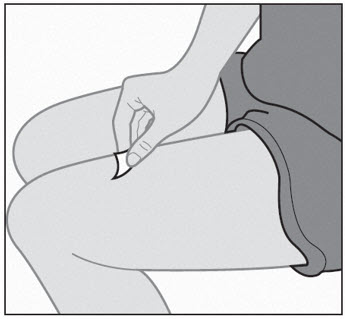
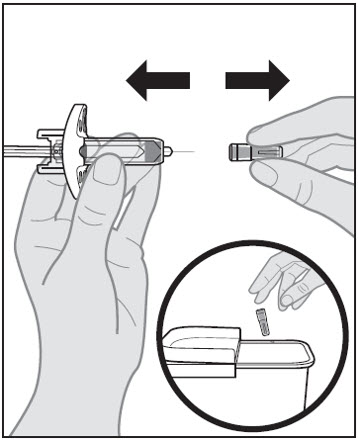
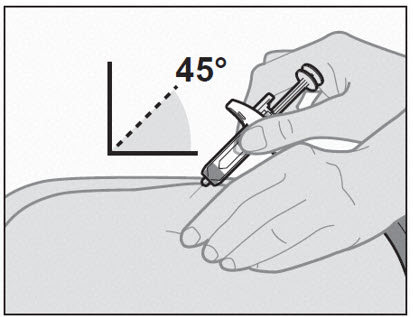
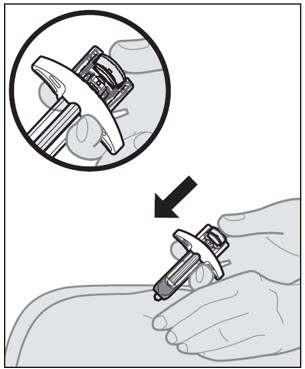
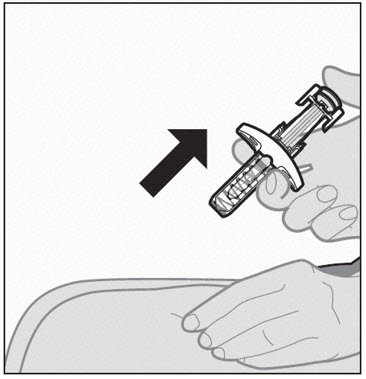
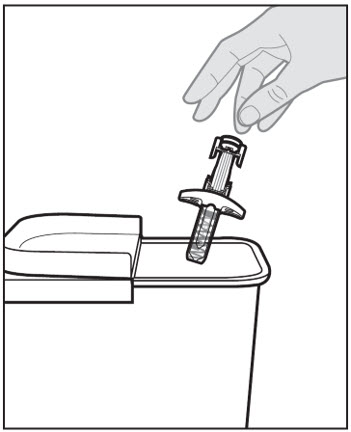
- Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. OMLYCLO prefilled syringe solution should be clear to opalescent and colorless to pale brownish yellow. Do not use the prefilled syringe if the medicine is distinctly cloudy, discolored, or contains particles.
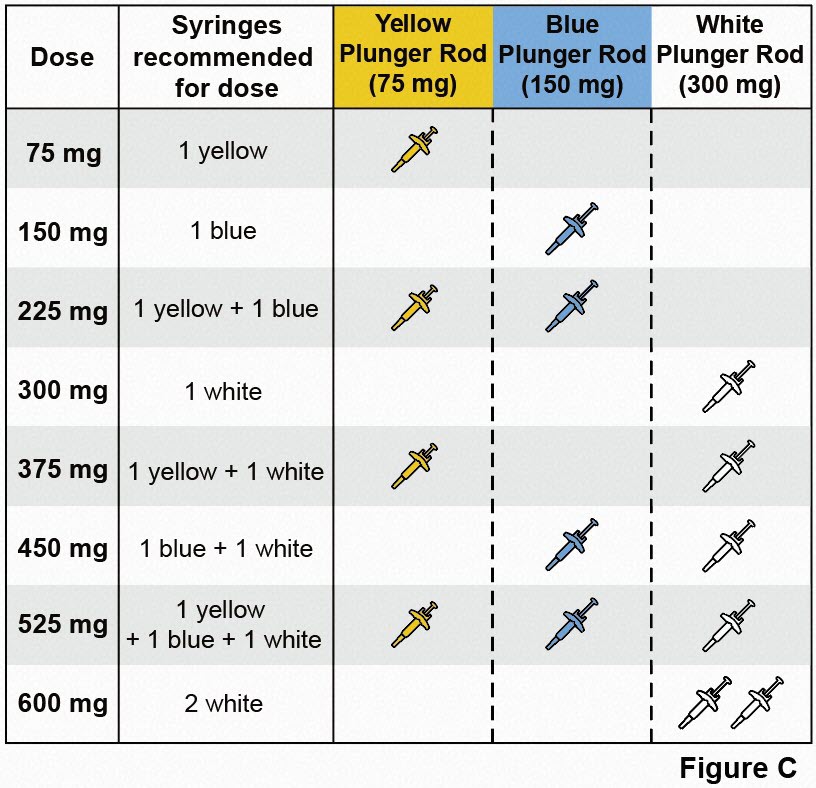
- Determine the number of prefilled syringes needed for patient's dosage (see Table 5). For pediatric patients 1 to 11 years of age, consideration should be given to the number of prefilled syringe injections needed and volume to be injected relative to the patient's body weight.
- For patients requiring more than 1 injection to complete a full dose, administer each injection at least 1-inch (2.5 cm) apart from other injection sites.
- Administer subcutaneous injection into the thigh or abdomen, avoiding the 2-inch (5 cm) area directly around the navel. The outer area of the upper arms may be used only if the injection is being given by a caregiver or healthcare provider [see Instructions for Use]. The injection may take up to 15 seconds to administer.
Table 5. Number of OMLYCLO Prefilled Syringes, Injections and Total Injection Volumes| OMLYCLO Dose | 75 mg | 150 mg | 300 mg | Total Volume Injected |
|---|
| 75 mg | 1 | 0 | 0 | 0.5 mL |
| 150 mg | 0 | 1 | 0 | 1 mL |
| 225 mg | 1 | 1 | 0 | 1.5 mL |
| 300 mg | 0 | 0 | 1 | 2 mL |
| 375 mg | 1 | 0 | 1 | 2.5 mL |
| 450 mg | 0 | 1 | 1 | 3 mL |
| 525 mg | 1 | 1 | 1 | 3.5 mL |
| 600 mg | 0 | 0 | 2 | 4 mL |
Adverse Reactions from Clinical Studies in Adult and Adolescent Patients 12 Years of Age and Older with Asthma
The data described below reflect omalizumab exposure for 2,076 adult and adolescent patients ages 12 and older, including 1,687 patients exposed for six months and 555 exposed for one year or more, in either placebo-controlled or other controlled asthma studies. The mean age of patients receiving omalizumab was 42 years, with 134 patients 65 years of age or older; 60% were women, and 85% Caucasian. Patients received omalizumab 150 mg to 375 mg every 2 or 4 weeks or, for patients assigned to control groups, standard therapy with or without a placebo.
The adverse reactions most frequently resulting in clinical intervention (e.g., discontinuation of omalizumab, or the need for concomitant medication to treat an adverse reaction) were injection site reaction (45%), viral infections (23%), upper respiratory tract infection (20%), sinusitis (16%), headache (15%), and pharyngitis (11%). These reactions were observed at similar rates in omalizumab-treated patients and control patients.
Table 6 shows adverse reactions from four placebo-controlled asthma trials that occurred ≥1% and more frequently in adult and adolescent patients 12 years of age and older receiving omalizumab than in those receiving placebo. Adverse reactions were classified using preferred terms from the International Medical Nomenclature (IMN) dictionary. Injection site reactions were recorded separately from the reporting of other adverse reactions.
Table 6. Adverse Reactions ≥1% More Frequent in omalizumab-Treated Adult or Adolescent Patients 12 years of Age and Older in Four Placebo-controlled Asthma Trials| Adverse reaction | Omalizumab
n=738 | Placebo
n=717 |
|---|
| Body as a whole | | |
| Pain | 7% | 5% |
| Fatigue | 3% | 2% |
| Musculoskeletal system | | |
| Arthralgia | 8% | 6% |
| Fracture | 2% | 1% |
| Leg pain | 4% | 2% |
| Arm pain | 2% | 1% |
| Nervous system | | |
| Dizziness | 3% | 2% |
| Skin and appendages | | |
| Pruritus | 2% | 1% |
| Dermatitis | 2% | 1% |
| Special senses | | |
| Earache | 2% | 1% |
There were no differences in the incidence of adverse reactions based on age (among patients under 65), gender or race.
Anaphylaxis Case Control Study
A retrospective case-control study investigated risk factors for anaphylaxis to omalizumab among patients treated with omalizumab for asthma. Cases with an adjudicated history of anaphylaxis to omalizumab were compared to controls with no such history. The study found that a self-reported history of anaphylaxis to foods, medications or other causes was more common among patients with omalizumab anaphylaxis (57% of 30 cases) compared to controls (23% of 88 controls) [OR 8.1, 95% CI 2.7 to 24.3]. Because this is a case-control study, the study cannot provide the incidence of anaphylaxis among omalizumab users. From other sources, anaphylaxis to omalizumab was observed in 0.1% of patients in clinical trials and at least 0.2% of patients based upon postmarketing reports. Approximately 60% to 70% of cases were reported to occur within the first three doses of omalizumab, with additional cases occurring sporadically beyond the third dose. The time to onset for anaphylaxis was reported to occur within 2 hours for the majority of cases (approximately 75%) [see Warnings and Precautions (5.1), Adverse Reactions (6.2)].
Injection Site Reactions
In adults and adolescents, injection site reactions of any severity occurred at a rate of 45% in omalizumab-treated patients compared with 43% in placebo-treated patients. The types of injection site reactions included: bruising, redness, warmth, burning, stinging, itching, hive formation, pain, indurations, mass, and inflammation.
Severe injection site reactions occurred more frequently in omalizumab-treated patients compared with patients in the placebo group (12% versus 9%).
The majority of injection site reactions occurred within 1 hour post injection, lasted less than 8 days, and generally decreased in frequency at subsequent dosing visits.
Adverse Reactions from Clinical Studies in Pediatric Patients 6 to <12 Years of Age with Asthma
The data described below reflect omalizumab exposure for 926 patients 6 to <12 years of age, including 583 patients exposed for six months and 292 exposed for one year or more, in either placebo-controlled or other controlled asthma studies. The mean age of pediatric patients receiving omalizumab was 8.8 years; 69% were male, and 64% were Caucasian.
Pediatric patients received omalizumab 75 mg to 375 mg every 2 or 4 weeks or, for patients assigned to control groups, standard therapy with or without a placebo. No cases of malignancy were reported in patients treated with omalizumab in these trials.
The most common adverse reactions occurring at ≥3% in the pediatric patients receiving omalizumab and more frequently than in patients treated with placebo were nasopharyngitis, headache, pyrexia, upper abdominal pain, pharyngitis streptococcal, otitis media, viral gastroenteritis, arthropod bite, and epistaxis.
The adverse reactions most frequently resulting in clinical intervention (e.g., discontinuation of omalizumab, or the need for concomitant medication to treat an adverse event) were bronchitis (0.2%), headache (0.2%) and urticaria (0.2%). These reactions were observed at similar rates in omalizumab-treated patients and control patients.
Adverse Reactions from Clinical Studies in Adult Patients with Chronic Rhinosinusitis with Nasal Polyps
The data described below reflect omalizumab exposure for 135 patients ≥ 18 years of age, exposed for six months in two placebo-controlled studies. The mean age of patients receiving omalizumab was 49.7 years; 64% were male, and 94% were Caucasian. Patients received omalizumab or placebo SC every 2 or 4 weeks, with dosage and frequency according to Table 3. All patients received background nasal mometasone therapy throughout the study. Table 7 lists the adverse reactions occurring in ≥3% of omalizumab-treated patients and more frequently than in patients treated with placebo in chronic rhinosinusitis with nasal polyps (CRSwNP) Trials 1 and 2; results were pooled.
Table 7. Adverse Reactions Occurring in ≥3% of omalizumab-Treated Patients and More Frequently than in Patients Treated with Placebo in CRSwNP Trials 1 and 2| Adverse reaction | Omalizumab
N=135 | Placebo
N=130 |
|---|
| CRSwNP = Chronic Rhinosinusitis with Nasal Polyps. |
| Gastrointestinal disorder |
| Upper abdominal pain | 4 (3.0%) | 1 (0.8%) |
| General disorders and administration site conditions |
| Injection site reactions Injection site reactions terms: 'injection site reaction', 'injection related reaction' and 'injection site pain'. Allinjection site reactions were mild to moderate severity and none resulted in study discontinuation | 7 (5.2%) | 2 (1.5%) |
| Musculoskeletal system and connective tissue disorders |
| Arthralgia | 4 (3.0%) | 2 (1.5%) |
| Nervous system disorders |
| Headache | 11 (8.1%) | 7 (5.4%) |
| Dizziness | 4 (3.0%) | 1 (0.8%) |
Adverse Reactions from a Clinical Study in Patients with IgE-Mediated Food Allergy
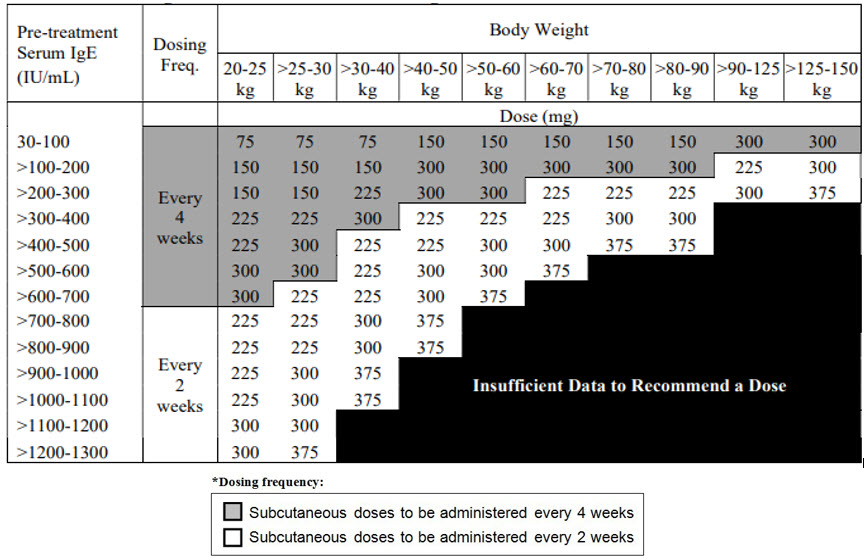
The safety of omalizumab in patients with IgE-mediated allergic reactions (Type I), including anaphylaxis, that may occur with accidental exposure to one or more foods, was based on data from the Food Allergy (FA) Trial, a randomized, double-blind, placebo-controlled trial in 168 patients (165 pediatric patients and 3 adults) who were allergic to peanut and at least two other foods [see Clinical Studies (14.3)]. Patients received a dosage of omalizumab or placebo subcutaneously every 2 or 4 weeks for 16 to 20 weeks according to the recommended dosage based on total IgE level (IU/mL), measured before the start of treatment, and by body weight (kg) provided in Table 4 [see Dosage and Administration (2.4)]. Safety data provided in Table 8 are from the primary analysis population of pediatric patients aged 1 years to 17 years. Safety data obtained from adults (n=3) in this trial was limited. Table 8 lists the adverse reactions occurring in ≥3% of omalizumab-treated pediatric patients and more frequently than in patients treated with placebo in the FA trial. There were no discontinuations due to adverse reactions.
Table 8. Adverse Reactions Occurring in ≥3% of omalizumab -Treated Pediatric Patients 1 Year of Age and Older and More Frequently than in Patients Treated with Placebo in FA Trial| Adverse reaction | Omalizumab
N=110 | Placebo
N=55 |
|---|
| General disorders and administration site conditions |
| Injection site reactions Injection site reactions terms: 'injection site reaction','injection site urticaria','injection site discomfort','injection site erythema','injection site pain' and 'injection site rash'. All injection site reactions were mild to moderate severity and none resulted in study discontinuation. | 17 (15.5%) | 6 (10.9%) |
| Pyrexia | 7 (6.4%) | 2 (3.6%) |
Adverse Reactions from Clinical Studies in Patients with Chronic Spontaneous Urticaria (CSU)
The safety of omalizumab for the treatment of chronic spontaneous urticaria (CSU) was assessed in three placebo-controlled, multiple-dose clinical trials of 12 weeks' (CSU Trial 2) and 24 weeks' duration (CSU Trials 1 and 3). In CSU Trials 1 and 2, patients received omalizumab 75 mg, 150 mg, or 300 mg or placebo every 4 weeks in addition to their baseline level of H1 antihistamine therapy throughout the treatment period. In CSU Trial 3 patients were randomized to omalizumab 300 mg or placebo every 4 weeks in addition to their baseline level of H1 antihistamine therapy. The data described below reflect omalizumab exposure for 733 patients enrolled and receiving at least one dose of omalizumab in the three clinical trials, including 684 patients exposed for 12 weeks and 427 exposed for 24 weeks. The mean age of patients receiving omalizumab 300 mg was 43 years, 75% were women, and 89% were white. The demographic profiles for patients receiving omalizumab 150 mg and 75 mg were similar.
Table 9 shows adverse reactions that occurred in ≥2% of patients receiving omalizumab (150 or 300 mg) and more frequently than those receiving placebo. Adverse reactions are pooled from CSU Trial 2 and the first 12 weeks of CSU Trials 1 and 3.
Table 9. Adverse Reactions Occurring in ≥2% in omalizumab-Treated Patients and More Frequently than in Patients Treated with Placebo (Day 1 to Week 12) in CSU Trials| Adverse Reactions by MedDRA (15.1) System Organ Class and Preferred Term | CSU Trials 1, 2 and 3 Pooled |
|---|
150 mg
(n=175) | 300 mg
(n=412) | Placebo
(n=242) |
|---|
| Gastrointestinal disorders | | | |
| Nausea | 2 (1.1%) | 11 (2.7%) | 6 (2.5%) |
| Infections and infestations | | | |
| Nasopharyngitis | 16 (9.1%) | 27 (6.6%) | 17 (7.0%) |
| Sinusitis | 2 (1.1%) | 20 (4.9%) | 5 (2.1%) |
| Upper respiratory tract infection | 2 (1.1%) | 14 (3.4%) | 5 (2.1%) |
| Viral upper respiratory tract infection | 4 (2.3%) | 2 (0.5%) | (0.0%) |
| Musculoskeletal and connective tissue disorders | | | |
| Arthralgia | 5 (2.9%) | 12 (2.9%) | 1 (0.4%) |
| Nervous system disorders | | | |
| Headache | 21 (12.0%) | 25 (6.1%) | 7 (2.9%) |
| Respiratory, thoracic, and mediastinal disorders | | | |
| Cough | 2 (1.1%) | 9 (2.2%) | 3 (1.2%) |
Additional reactions reported during the 24-week treatment period in CSU Trials 1 and 3 [≥2% of patients receiving omalizumab (150 mg or 300 mg) and more frequently than those receiving placebo] included: toothache, fungal infection, urinary tract infection, myalgia, pain in extremity, musculoskeletal pain, peripheral edema, pyrexia, migraine, sinus headache, anxiety, oropharyngeal pain, asthma, urticaria, and alopecia.
Injection Site Reactions in Patients with CSU
Injection site reactions of any severity occurred during the studies in more omalizumab-treated patients [11 patients (2.7%) at 300 mg, 1 patient (0.6%) at 150 mg] compared with 2 placebo-treated patients (0.8%). The types of injection site reactions included: swelling, erythema, pain, bruising, itching, bleeding, and urticaria. None of the events resulted in study discontinuation or treatment interruption.
Cardiovascular and Cerebrovascular Events from Clinical Studies in Patients with Asthma
A 5-year observational cohort study was conducted in patients ≥12 years of age with moderate to severe persistent asthma and a positive skin test reaction to a perennial aeroallergen to evaluate the long-term safety of omalizumab, including the risk of malignancy [see Warnings and Precautions (5.2)]. A total of 5,007 omalizumab-treated and 2,829 non–omalizumab-treated patients enrolled in the study. Similar percentages of patients in both cohorts were current (5%) or former smokers (29%). Patients had a mean age of 45 years and were followed for a mean of 3.7 years. More omalizumab-treated patients were diagnosed with severe asthma (50%) compared to the non–omalizumab-treated patients (23%) and 44% of patients prematurely discontinued the study. Additionally, 88% of patients in the omalizumab- treated cohort had been previously exposed to omalizumab for a mean of 8 months.
A higher incidence rate (per 1,000 patient-years) of overall cardiovascular and cerebrovascular serious adverse events (SAEs) was observed in omalizumab-treated patients (13.4) compared to non–omalizumab-treated patients (8.1). Increases in rates were observed for transient ischemic attack (0.7 versus 0.1), myocardial infarction (2.1 versus 0.8), pulmonary hypertension (0.5 versus 0), pulmonary embolism/venous thrombosis (3.2 versus 1.5), and unstable angina (2.2 versus 1.4), while the rates observed for ischemic stroke and cardiovascular death were similar among both study cohorts. The results suggest a potential increased risk of serious cardiovascular and cerebrovascular events in patients treated with omalizumab. However, the observational study design, the inclusion of patients previously exposed to omalizumab (88%), baseline imbalances in cardiovascular risk factors between the treatment groups, an inability to adjust for unmeasured risk factors, and the high study discontinuation rate limit the ability to quantify the magnitude of the risk.
A pooled analysis of 25 randomized double-blind, placebo-controlled clinical trials of 8 to 52 weeks in duration was conducted to further evaluate the imbalance in cardiovascular and cerebrovascular SAEs noted in the above observational cohort study. A total of 3,342 omalizumab-treated patients and 2,895 placebo-treated patients were included in the pooled analysis. The patients had a mean age of 38 years, and were followed for a mean duration of 6.8 months. No notable imbalances were observed in the rates of cardiovascular and cerebrovascular SAEs listed above. However, the results of the pooled analysis were based on a low number of events, slightly younger patients, and shorter duration of follow-up than the observational cohort study; therefore, the results are insufficient to confirm or reject the findings noted in the observational cohort study.
Anaphylaxis: Based on spontaneous reports and an estimated exposure of about 57,300 patients from June 2003 through December 2006, the frequency of anaphylaxis attributed to omalizumab use was estimated to be at least 0.2% of patients. Diagnostic criteria of anaphylaxis were skin or mucosal tissue involvement, and, either airway compromise, and/or reduced blood pressure with or without associated symptoms, and a temporal relationship to omalizumab administration with no other identifiable cause. Signs and symptoms in these reported cases included bronchospasm, hypotension, syncope, urticaria, angioedema of the throat or tongue, dyspnea, cough, chest tightness, and/or cutaneous angioedema. Pulmonary involvement was reported in 89% of the cases. Hypotension or syncope was reported in 14% of cases. Fifteen percent of the reported cases resulted in hospitalization. A previous history of anaphylaxis unrelated to omalizumab was reported in 24% of the cases.
Of the reported cases of anaphylaxis attributed to omalizumab, 39% occurred with the first dose, 19% occurred with the second dose, 10% occurred with the third dose, and the rest after subsequent doses. One case occurred after 39 doses (after 19 months of continuous therapy, anaphylaxis occurred when treatment was restarted following a 3-month gap). The time to onset of anaphylaxis in these cases was up to 30 minutes in 35%, greater than 30 and up to 60 minutes in 16%, greater than 60 and up to 90 minutes in 2%, greater than 90 and up to 120 minutes in 6%, greater than 2 hours and up to 6 hours in 5%, greater than 6 hours and up to 12 hours in 14%, greater than 12 hours and up to 24 hours in 8%, and greater than 24 hours and up to 4 days in 5%. In 9% of cases the times to onset were unknown.
Twenty-three patients who experienced anaphylaxis were rechallenged with omalizumab and 18 patients had a recurrence of similar symptoms of anaphylaxis. In addition, anaphylaxis occurred upon rechallenge with omalizumab in 4 patients who previously experienced urticaria only.
Eosinophilic Conditions: Eosinophilic conditions have been reported [see Warnings and Precautions (5.5)].
Fever, Arthralgia, and Rash: A constellation of signs and symptoms including arthritis/arthralgia, rash (urticaria or other forms), fever and lymphadenopathy similar to serum sickness have been reported in post-approval use of omalizumab products [see Warnings and Precautions (5.6)].
Hematologic: Severe thrombocytopenia has been reported.
Skin: Hair loss has been reported.
Risk Summary
A registry study of omalizumab exposure during pregnancy showed no increase in the rate of major birth defects or miscarriage. There was an increased rate of low birth weight among registry infants compared to infants in the other cohorts, despite average gestational age at birth; however, women taking omalizumab during pregnancy also had more severe asthma, which makes it difficult to determine whether the low birth weight is due to the drug or the disease severity [see Data]. There are risks associated with poorly or moderately controlled asthma in pregnancy [see Clinical Considerations].
Human IgG antibodies are known to cross the placental barrier; therefore, omalizumab products may be transmitted from the mother to the developing fetus.
In animal reproduction studies, no evidence of fetal harm was observed in Cynomolgus monkeys with subcutaneous doses of omalizumab up to approximately 5 times the maximum recommended human dose (MRHD) [see Data].
The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations
Disease-associated maternal and/or embryo/fetal risk
In women with poorly or moderately controlled asthma, evidence demonstrates that there is an increased risk of preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate. The level of asthma control should be closely monitored in pregnant women and treatment adjusted as necessary to maintain optimal control.
Data
Human Data
A prospective cohort pregnancy exposure registry study conducted in the US from 2006 to 2018, included 250 pregnant women with asthma treated with omalizumab. Of these, 246 patients were exposed to omalizumab in the first trimester of pregnancy, and the median exposure duration was 8.7 months.
The registry findings for applicable mother and infant subgroups were compared to age- adjusted frequencies in a disease-matched external cohort of 1,153 pregnant women with asthma (without exposure to omalizumab) identified from healthcare databases of residents in the Canadian province of Quebec, and referred to as the Quebec External Comparator Cohort ("comparator cohort").
Among applicable registry infants, the prevalence of major congenital anomalies (8.1%) was similar to that for infants in the comparator cohort (8.9%). Among applicable registry pregnancies, 99.1% led to live births, similar to 99.3% for the comparator cohort. There was an increased rate of low birth weight among registry infants (13.7%) as compared to the comparator cohort (9.8%); however, women taking omalizumab during pregnancy also had more severe asthma, which makes it difficult to determine whether the low birth weight is due to the drug or the disease severity.
The registry study cannot definitively establish the absence of any risk because of methodological limitations, including the observational nature of the registry, small sample size, and potential differences between the registry population and the comparator cohort.
Animal Data
Reproductive studies have been performed in Cynomolgus monkeys. There was no evidence of maternal toxicity, embryotoxicity, or teratogenicity when omalizumab was administered throughout the period of organogenesis at doses that produced exposures approximately 5 times the MRHD (on a mg/kg basis with maternal subcutaneous doses up to 75 mg/kg/week). Omalizumab did not elicit adverse effects on fetal or neonatal growth when administered throughout late gestation, delivery, and nursing.
Risk Summary
There is no information regarding the presence of omalizumab products in human milk, or the effects on milk production. However, omalizumab products are human monoclonal antibodies (IgG1 kappa), and immunoglobulin (IgG) is present in human milk in small amounts.
The majority of infants (80.9%, 186/230) in the pregnancy exposure registry were breastfed. Events categorized as "infections and infestations" were not significantly increased in infants who were exposed to omalizumab through breastfeeding compared with infants who were not breastfed, or infants who were breastfed without exposure to omalizumab.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for OMLYCLO and any potential adverse effects on the breastfed child from OMLYCLO or from the underlying maternal condition.
Asthma
Safety and effectiveness of OMLYCLO for moderate to severe persistent asthma who had a positive skin test or in vitro reactivity to a perennial aeroallergen and whose symptoms are inadequately controlled with inhaled corticosteroids, have been established in pediatric patients aged 6 years and older. Use of OMLYCLO for this indication is supported by evidence from adequate and well-controlled studies of omalizumab. Omalizumab was evaluated in 2 trials in 926 (omalizumab 624; placebo 302) pediatric patients 6 to <12 years of age with moderate to severe persistent asthma who had a positive skin test or in vitro reactivity to a perennial aeroallergen. One trial was a pivotal trial of similar design and conduct to that of adult and adolescent Asthma Trials 1 and 2. The other trial was primarily a safety study and included evaluation of efficacy as a secondary outcome. In the pivotal trial, omalizumab-treated patients had a statistically significant reduction in the rate of exacerbations (exacerbation was defined as worsening of asthma that required treatment with systemic corticosteroids or a doubling of the baseline ICS dose) [see Clinical Studies (14.1)].
Safety and efficacy of OMLYCLO in pediatric patients with asthma below 6 years of age have not been established.
Chronic Rhinosinusitis with Nasal Polyps
Safety and effectiveness of OMLYCLO in pediatric patients with chronic rhinosinusitis with nasal polyps (CRSwNP) below 18 years of age have not been established.
IgE-Mediated Food Allergy
The safety and effectiveness of OMLYCLO for the reduction of allergic reactions (Type I), including anaphylaxis, that may occur with accidental exposure to one or more foods have been established in pediatric patients aged 1 year and older with IgE-mediated food allergy. Use of OMLYCLO for this indication is supported by evidence from an adequate and well-controlled study that included a total of 165 pediatric patients; 61 patients aged 1 year to less than 6 years of age and 104 patients aged 6 to less than 18 years of age. A significantly greater percentage of omalizumab-treated patients compared to placebo-treated patients was able to consume a single dose of food (peanut, cashew, milk, egg) without dose-limiting symptoms [see Clinical Studies (14.3)].
Safety and effectiveness in pediatric patients with IgE-mediated food allergy below 1 year of age have not been established.
Chronic Spontaneous Urticaria
The safety and effectiveness of OMLYCLO for chronic spontaneous urticaria (CSU) who remain symptomatic despite H1 antihistamine treatment have been established in pediatric patients aged 12 years and older. Use of OMLYCLO in this population is supported by evidence from adequate and well-controlled studies of omalizumab. Adolescent patients with CSU were evaluated in 39 patients 12 to 17 years of age (omalizumab 29, placebo 10) included in three randomized, placebo-controlled CSU trials. A numerical decrease in weekly itch score was observed, and adverse reactions were similar to those reported in patients 18 years and older.
Safety and effectiveness of OMLYCLO in pediatric patients with CSU below 12 years of age have not been established.
OMLYCLO Injection (Prefilled Syringe)
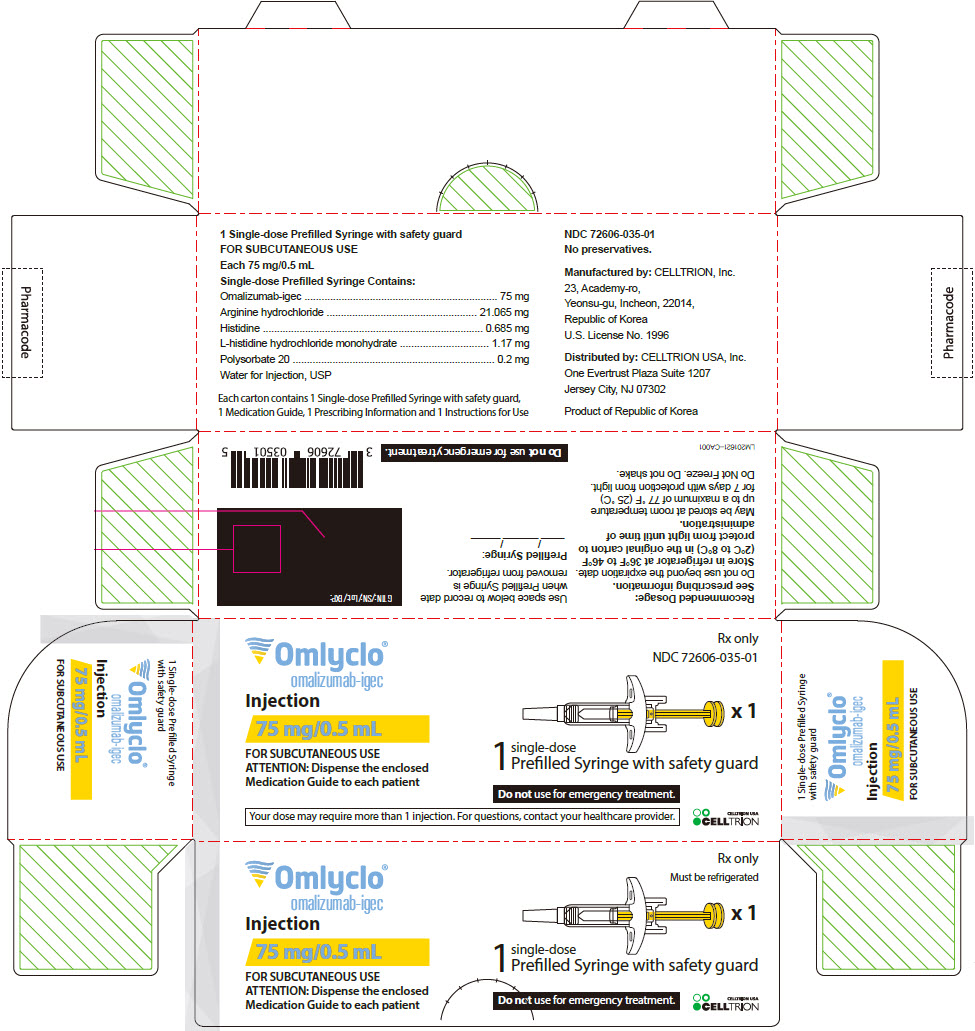
OMLYCLO (omalizumab-igec) injection is supplied as a sterile, preservative-free, clear to opalescent and colorless to pale brownish-yellow solution for subcutaneous injection.
OMLYCLO (omalizumab-igec) injection is available as a single-dose prefilled syringe.
Each 75 mg prefilled syringe delivers 75 mg omalizumab-igec in 0.5 mL and contains arginine hydrochloride (21.065 mg), histidine (0.685 mg), L-histidine hydrochloride monohydrate (1.17 mg), and polysorbate 20 (0.2 mg) in Water for Injection (WFI), USP. The pH of the product is 6.0.
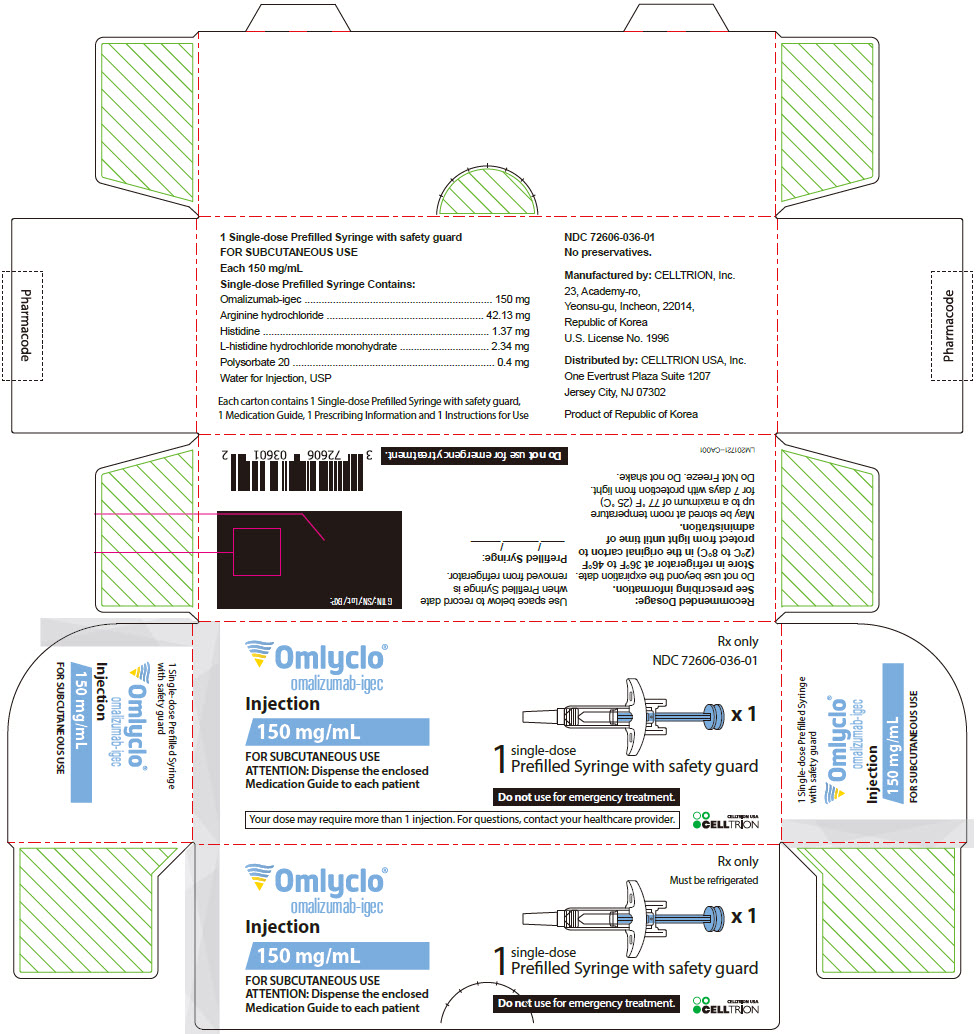
Each 150 mg prefilled syringe delivers 150 mg omalizumab-igec in 1 mL and contains arginine hydrochloride (42.13 mg), histidine (1.37 mg), L-histidine hydrochloride monohydrate (2.34 mg), and polysorbate 20 (0.4 mg) in WFI, USP. The pH of the product is 6.0.
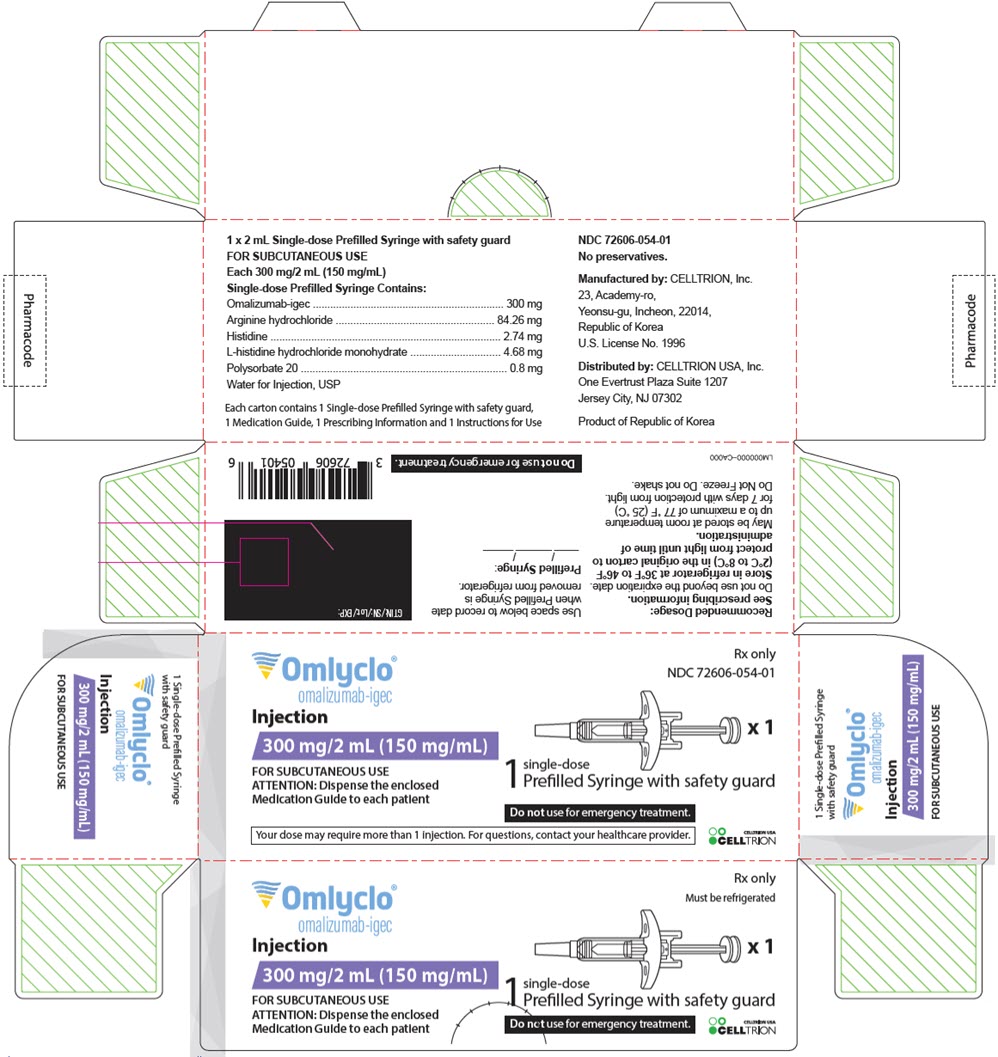
Each 300 mg prefilled syringe delivers 300 mg omalizumab-igec in 2 mL and contains arginine hydrochloride (84.26 mg), histidine (2.74 mg), L-histidine hydrochloride monohydrate (4.68 mg), and polysorbate 20 (0.8 mg) in WFI, USP. The pH of the product is 6.0.
Asthma, Chronic Rhinosinusitis with Nasal Polyps, and IgE-Mediated Food Allergy
Omalizumab products inhibit the binding of IgE to the high-affinity IgE receptor (FcεRI) on the surface of mast cells, basophils, and dendritic cells, resulting in FcεRI down-regulation on these cells.
In allergic asthmatics, treatment with omalizumab products inhibit IgE-mediated inflammation, as evidenced by reduced blood and tissue eosinophils and reduced inflammatory mediators, including IL-4, IL-5, and IL-13.
Chronic Spontaneous Urticaria
Omalizumab products bind to IgE and lowers free IgE levels. Subsequently, IgE receptors (FcεRI) on cells down-regulate. The mechanism by which these effects of omalizumab products result in an improvement of chronic spontaneous urticaria (CSU) symptoms is unknown.
Asthma
In clinical studies, serum free IgE levels were reduced in a dose-dependent manner within 1 hour following the first dose and maintained between doses. Mean serum free IgE decrease was greater than 96% using recommended doses. Serum total IgE levels (i.e., bound and unbound) increased after the first dose due to the formation of drug:IgE complexes, which have a slower elimination rate compared with free IgE. At 16 weeks after the first dose, average serum total IgE levels were five-fold higher compared with pre-treatment when using standard assays. After discontinuation of omalizumab dosing, the omalizumab -induced increase in total IgE and decrease in free IgE were reversible, with no observed rebound in IgE levels after drug washout. Total IgE levels did not return to pre-treatment levels for up to one year after discontinuation of omalizumab.
Chronic Rhinosinusitis with Nasal Polyps
In clinical studies in chronic rhinosinusitis with nasal polyps (CRSwNP) patients, omalizumab treatment led to a reduction in serum free IgE and an increase in serum total IgE levels, similar to the observations in asthma patients. The mean total IgE concentrations at baseline were 168 IU/mL and 218 IU/mL in CRSwNP Trial 1 and 2, respectively. After repeated dosing every 2 or 4 weeks, with dosage and frequency according to Table 3, the mean predose free IgE concentrations at Week 16 were 10.0 IU/mL in CRSwNP Trial 1 and 11.7 IU/mL in CRSwNP Trial 2 and remained stable at 24 weeks of treatment. Total IgE levels in serum increased due to the formation of omalizumab-IgE complexes, which have a slower elimination rate compared with free IgE. After repeated dosing every 2 or 4 weeks, with dosage and frequency according to Table 3, mean and median predose serum total IgE levels at Week 16 were 3- to 4- fold higher compared with pre-treatment levels, and remained stable between 16 and 24 weeks of treatment.
IgE-Mediated Food Allergy
In a clinical study in patients with IgE-mediated food allergy, omalizumab treatment led to a reduction in serum free IgE and an increase in serum total IgE levels, similar to the observations in asthma patients. The mean total IgE concentration at baseline was 810 IU/mL. After repeated dosing every 2 or 4 weeks, with dosage and frequency according to Table 4, the mean pre-dose free IgE concentration at Week 16 was 10.0 IU/mL. Mean total IgE levels in serum increased about 2.4-fold due to the formation of omalizumab-IgE complexes, which have a longer half-life compared with free IgE.
Chronic Spontaneous Urticaria
In clinical studies in chronic spontaneous urticaria (CSU) patients, omalizumab treatment led to a dose-dependent reduction of serum free IgE and an increase of serum total IgE levels, similar to the observations in asthma patients. Maximum suppression of free IgE was observed 3 days following the first subcutaneous dose. After repeat dosing once every 4 weeks, predose serum free IgE levels remained stable between 12 and 24 weeks of treatment. Total IgE levels in serum increased after the first dose due to the formation of omalizumab-IgE complexes which have a slower elimination rate compared with free IgE. After repeat dosing once every 4 weeks at 75 mg up to 300 mg, average predose serum total IgE levels at Week 12 were two- to three-fold higher compared with pre-treatment levels, and remained stable between 12 and 24 weeks of treatment. After discontinuation of omalizumab dosing, free IgE levels increased and total IgE levels decreased towards pre-treatment levels over a 16-week follow-up period.
Specific Populations
Asthma
The population pharmacokinetics of omalizumab was analyzed to evaluate the effects of demographic characteristics in patients with asthma. Analyses of these data suggested that no dose adjustments are necessary for age (6 to 76 years), race, ethnicity, or gender.
Chronic Rhinosinusitis with Nasal Polyps
The population pharmacokinetics analyses of omalizumab suggested that the pharmacokinetics of omalizumab in chronic rhinosinusitis with nasal polyps (CRSwNP) were consistent with that in asthma. Graphical covariate analyses were performed to evaluate the effects of demographic characteristics and other factors on omalizumab exposure and clinical responses. These analyses demonstrate that no dose adjustments are necessary for age (18 to 75 years) or gender. Race and ethnicity data are too limited in CRSwNP studies to inform dose adjustment.
IgE-Mediated Food Allergy
Population pharmacokinetic (PK) analyses of omalizumab suggested that the PK of omalizumab in patients with IgE-mediated food allergy were generally consistent with that in patients with asthma. Covariate analyses were performed to evaluate the effects of demographic characteristics and other factors on omalizumab exposure and clinical responses. These analyses demonstrate that no dose adjustments are necessary for age (1 year and older), race, ethnicity, or gender.
Chronic Spontaneous Urticaria
The population pharmacokinetics of omalizumab was analyzed to evaluate the effects of demographic characteristics and other factors on omalizumab exposure in patients with chronic spontaneous urticaria (CSU). Covariate effects were evaluated by analyzing the relationship between omalizumab concentrations and clinical responses. These analyses demonstrate that no dose adjustments are necessary for age (12 to 75 years), race/ethnicity, gender, body weight, body mass index, or baseline IgE level.
Adult and Adolescent Patients 12 Years of Age and Older
The safety and efficacy of omalizumab were evaluated in three randomized, double-blind, placebo-controlled, multicenter trials.
The trials enrolled patients 12 to 76 years old, with moderate to severe persistent (NHLBI criteria) asthma for at least one year, and a positive skin test reaction to a perennial aeroallergen. In all trials, omalizumab dosing was based on body weight and baseline serum total IgE concentration.
All patients were required to have a baseline IgE between 30 and 700 IU/mL and body weight not more than 150 kg. Patients were treated according to a dosing table to administer at least 0.016 mg/kg/IU (IgE/mL) of omalizumab or a matching volume of placebo over each 4-week period. The maximum omalizumab dose per 4 weeks was 750 mg.
In all three trials an exacerbation was defined as a worsening of asthma that required treatment with systemic corticosteroids or a doubling of the baseline ICS dose. Most exacerbations were managed in the outpatient setting and the majority were treated with systemic steroids. Hospitalization rates were not significantly different between omalizumab and placebo-treated patients; however, the overall hospitalization rate was small. Among those patients who experienced an exacerbation, the distribution of exacerbation severity was similar between treatment groups.
Asthma Trials 1 and 2
At screening, patients in Asthma Trials 1 and 2 had a forced expiratory volume in one second (FEV1) between 40% and 80% predicted. All patients had a FEV1 improvement of at least 12% following beta2-agonist administration. All patients were symptomatic and were being treated with inhaled corticosteroids (ICS) and short-acting beta2-agonists. Patients receiving other concomitant controller medications were excluded, and initiation of additional controller medications while on study was prohibited. Patients currently smoking were excluded.
Each trial was comprised of a run-in period to achieve a stable conversion to a common ICS (beclomethasone dipropionate), followed by randomization to omalizumab or placebo. Patients received omalizumab for 16 weeks with an unchanged corticosteroid dose unless an acute exacerbation necessitated an increase. Patients then entered an ICS reduction phase of 12 weeks during which ICS dose reduction was attempted in a step-wise manner.
The distribution of the number of asthma exacerbations per patient in each group during a study was analyzed separately for the stable steroid and steroid-reduction periods.
In both Asthma Trials 1 and 2 the number of exacerbations per patient was reduced in patients treated with omalizumab compared with placebo (Table 10).
Measures of airflow (FEV1) and asthma symptoms were also evaluated in these trials. The clinical relevance of the treatment-associated differences is unknown. Results from the stable steroid phase Asthma Trial 1 are shown in Table 11. Results from the stable steroid phase of Asthma Trial 2 and the steroid reduction phases of both Asthma Trials 1 and 2 were similar to those presented in Table 11.
Table 10. Frequency of Asthma Exacerbations per Patient by Phase in Asthma Trials 1 and 2 | Stable Steroid Phase (16 wks) |
| Asthma Trial 1 | Asthma Trial 2 |
| Exacerbations per patient | omalizumab
N=268 | Placebo
N=257 | omalizumab
N=274 | Placebo
N=272 |
| 0 | 85.8% | 76.7% | 87.6% | 69.9% |
| 1 | 11.9% | 16.7% | 11.3% | 25.0% |
| ≥2 | 2.2% | 6.6% | 1.1% | 5.1% |
| p-Value | 0.005 | <0.001 |
| Mean number exacerbations/patient | 0.2 | 0.3 | 0.1 | 0.4 |
| Steroid Reduction Phase (12 wks) |
| Exacerbations per patient | omalizumab
N=268 | Placebo
N=257 | omalizumab
N=274 | Placebo
N=272 |
| 0 | 78.7% | 67.7% | 83.9% | 70.2% |
| 1 | 19.0% | 28.4% | 14.2% | 26.1% |
| ≥2 | 2.2% | 3.9% | 1.8% | 3.7% |
| p-Value | 0.004 | <0.001 |
| Mean number exacerbations/patient | 0.2 | 0.4 | 0.2 | 0.3 |
Table 11. Asthma Symptoms and Pulmonary Function During Stable Steroid Phase of Asthma Trial 1 | omalizumab
N=268Number of patients available for analysis ranges 255-258 in the omalizumab group and 238-239 in the placebo group. | Placebo
N=257 |
|---|
| Endpoint | Mean Baseline | Median Change
(Baseline to Wk 16) | Mean Baseline | Median Change
(Baseline to Wk 16) |
|---|
| Asthma symptom scale: total score from 0 (least) to 9 (most); nocturnal and daytime scores from 0 (least) to 4 (most symptoms). |
| Total asthma symptom score | 4.3 | –1.5 Comparison of omalizumab versus placebo (p < 0.05). | 4.2 | –1.1 |
| Nocturnal asthma score | 1.2 | –0.4 | 1.1 | –0.2 |
| Daytime asthma score | 2.3 | –0.9 | 2.3 | –0.6 |
| FEV1 % predicted | 68 | 3 | 68 | 0 |
Asthma Trial 3
In Asthma Trial 3, there was no restriction on screening FEV1, and unlike Asthma Trials 1 and 2, long-acting beta2-agonists were allowed. Patients were receiving at least 1000 μg/day fluticasone propionate and a subset was also receiving oral corticosteroids. Patients receiving other concomitant controller medications were excluded, and initiation of additional controller medications while on study was prohibited. Patients currently smoking were excluded.
The trial was comprised of a run-in period to achieve a stable conversion to a common ICS (fluticasone propionate), followed by randomization to omalizumab or placebo. Patients were stratified by use of ICS-only or ICS with concomitant use of oral steroids. Patients received omalizumab for 16 weeks with an unchanged corticosteroid dose unless an acute exacerbation necessitated an increase. Patients then entered an ICS reduction phase of 16 weeks during which ICS or oral steroid dose reduction was attempted in a step-wise manner.
The number of exacerbations in patients treated with omalizumab was similar to that in placebo-treated patients (Table 12). The absence of an observed treatment effect may be related to differences in the patient population compared with Asthma Trials 1 and 2, study sample size, or other factors.
Table 12. Percentage of Patients with Asthma Exacerbations by Subgroup and Phase in Asthma Trial 3 | Stable Steroid Phase (16 wks) |
| Inhaled Only | Oral + Inhaled |
| omalizumab
N=126 | Placebo
N=120 | omalizumab
N=50 | Placebo
N=45 |
| % Patients with ≥1 exacerbations | 15.9% | 15.0% | 32.0% | 22.2% |
Difference
(95% CI) | 0.9
(–9.7, 13.7) | 9.8
(–10.5, 31.4) |
| Steroid Reduction Phase (16 wks) |
| omalizumab
N=126 | Placebo
N=120 | omalizumab
N=50 | Placebo
N=45 |
| % Patients with ≥1 exacerbations | 22.2% | 26.7% | 42.0% | 42.2% |
Difference
(95% CI) | –4.4
(–17.6, 7.4) | –0.2
(–22.4, 20.1) |
In all three of the trials, a reduction of asthma exacerbations was not observed in the omalizumab-treated patients who had FEV1>80% at the time of randomization. Reductions in exacerbations were not seen in patients who required oral steroids as maintenance therapy.
Pediatric Patients 6 to <12 Years of Age
The safety and efficacy of omalizumab in pediatric patients 6 to <12 years of age with moderate to severe asthma is based on one randomized, double-blind, placebo controlled, multi-center trial (Asthma Trial 4 [NCT00079937]) and an additional supportive study (Asthma Trial 5).
Asthma Trial 4 was a 52-week study that evaluated the safety and efficacy of omalizumab as add-on therapy in 628 pediatric patients ages 6 to <12 years with moderate to severe asthma inadequately controlled despite the use of inhaled corticosteroids (fluticasone propionate DPI ≥200 mcg/day or equivalent) with or without other controller asthma medications. Eligible patients were those with a diagnosis of asthma >1 year, a positive skin prick test to at least one perennial aeroallergen, and a history of clinical features such as daytime and/or night-time symptoms and exacerbations within the year prior to study entry. During the first 24 weeks of treatment, steroid doses remained constant from baseline. This was followed by a 28-week period during which inhaled corticosteroid adjustment was allowed.
The primary efficacy variable was the rate of asthma exacerbations during the 24-week, fixed steroid treatment phase. An asthma exacerbation was defined as a worsening of asthma symptoms as judged clinically by the investigator, requiring doubling of the baseline inhaled corticosteroid dose for at least 3 days and/or treatment with rescue systemic (oral or IV) corticosteroids for at least 3 days. At 24 weeks, the omalizumab group had a statistically significantly lower rate of asthma exacerbations (0.45 vs. 0.64) with an estimated rate ratio of 0.69 (95% CI: 0.53, 0.90).
The omalizumab group also had a lower rate of asthma exacerbations compared to placebo over the full 52-week double-blind treatment period (0.78 vs. 1.36; rate ratio: 0.57; 95% CI: 0.45, 0.72). Other efficacy variables such as nocturnal symptom scores, beta-agonist use, and measures of airflow (FEV1) were not significantly different in omalizumab-treated patients compared to placebo.
Asthma Trial 5 was a 28-week randomized, double blind, placebo-controlled study that primarily evaluated safety in 334 pediatric patients, 298 of whom were 6 to <12 years of age, with moderate to severe asthma who were well-controlled with inhaled corticosteroids (beclomethasone dipropionate 168-420 mcg/day). A 16-week steroid treatment period was followed by a 12-week steroid dose reduction period. Patients treated with omalizumab had fewer asthma exacerbations compared to placebo during both the 16-week fixed steroid treatment period (0.18 vs. 0.32; rate ratio: 0.58; 95% CI: 0.35, 0.96) and the 28-week treatment period (0.38 vs. 0.76; rate ratio: 0.50; 95% CI: 0.36, 0.71).
Adult Patients 18 Years of Age and Older
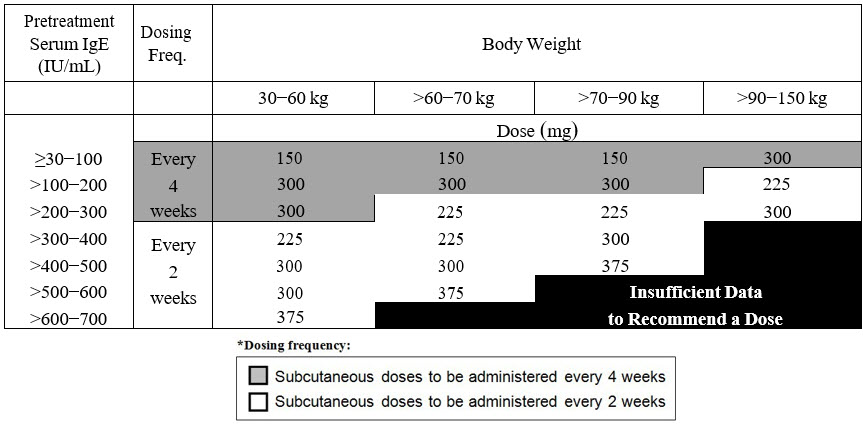
The safety and efficacy of omalizumab was evaluated in two, randomized, multicenter, double- blind, placebo-controlled clinical trials (CRSwNP Trial 1 [NCT03280550] and CRSwNP Trial 2 [NCT03280537]) that enrolled patients with chronic rhinosinusitis with nasal polyps (CRSwNP) with inadequate response to nasal corticosteroids (CRSwNP Trial 1, n=138; CRSwNP Trial 2, n=127). Patients received omalizumab or placebo SC every 2 or 4 weeks, with omalizumab dosage and frequency according to Table 3, for 24 weeks followed by a 4-week follow-up period. All patients received background nasal mometasone therapy during both the treatment period and during a 5-week run-in period. Prior to randomization, patients were required to have evidence of bilateral polyps as determined by a nasal polyp score (NPS) ≥ 5 with NPS ≥ 2 in each nostril, despite use of nasal mometasone during the run-in period. NPS was measured via endoscopy and scored (range 0-4 per nostril: 0= no polyps; 1=small polyps in the middle meatus not reaching below the inferior border of the middle turbinate; 2=polyps reaching below the lower border of the middle turbinate; 3=large polyps reaching the lower border of the inferior turbinate or polyps medial to the middle turbinate; 4=large polyps causing complete obstruction of the inferior nasal cavity) for a total NPS (range 0-8). Patients were furthermore required to have a weekly average of nasal congestion score (NCS) > 1 prior to randomization, despite use of nasal mometasone. Nasal congestion was measured by a daily assessment on a 0 to 3 point severity scale (0=none, 1=mild, 2=moderate, 3=severe). Prior sino-nasal surgery or prior systemic corticosteroid usage were not required for inclusion in the trials and sinus CT scans were not performed to evaluate for sinus opacification.
Demographics and baseline characteristics, including allergic comorbidities, are described in Table 13.
Table 13. Demographics and Baseline Characteristics of CRSwNP Trials 1 and 2| Parameter | CRSwNP Trial 1
(n=138) | CRSwNP Trial 2
(n=127) |
|---|
| CRSwNP= chronic rhinosinusitis with nasal polyps; SD=standard deviation; NPS=nasal polyp score; IgE = Immunoglobulin E; IU=international units. For NPS, NCS, sense of smell, post nasal drip, and runny nose, higher scores indicate greater disease severity. |
| Mean age (years) (SD) | 51 (13) | 50 (12) |
| % Male | 64 | 65 |
| Patients with systemic corticosteroid use in the previous year (%) | 19 | 26 |
| Patients with prior surgery for nasal polyps (%) | 79 (57) | 79 (62) |
| Mean bilateral endoscopic NPS (SD), range 0-8 | 6.2 (1.0) | 6.3 (0.9) |
| Mean nasal congestion score (SD) range 0-3 | 2.4 (0.6) | 2.3 (0.7) |
| Mean sense of smell score (SD) range 0-3 | 2.7 (0.7) | 2.7 (0.7) |
| Mean post nasal drip score (SD) range 0-3 | 1.8 (0.9) | 1.7 (0.9) |
| Mean runny nose score (SD) range 0-3 | 2.0 (0.8) | 1.9 (0.9) |
| Mean blood eosinophils (cells/mcL) (SD) | 346 (284) | 335 (188) |
| Mean total IgE IU/mL (SD) | 161 (140) | 190 (201) |
| Asthma (%) | 54 | 61 |
| Aspirin exacerbated respiratory disease (%) | 20 | 35 |
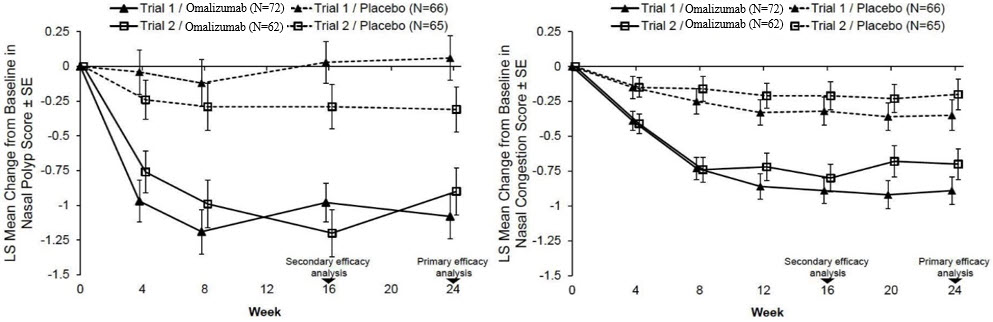
The co-primary endpoints in CRSwNP Trials 1 and 2 were NPS and average daily NCS at Week 24. In both trials, patients who received omalizumab had a statistically significant greater improvement from baseline at Week 24 in NPS and weekly average NCS, than patients who received placebo. Results from CRSwNP Trials 1 and 2 are shown in Table 14.
The greater improvements in NPS and NCS in the omalizumab group compared to the placebo group were observed as early as the first assessment at Week 4 in both studies, as seen in Figure 1.
Table 14. Change from Baseline at Week 24 in Nasal Polyp Score and 7-day Average of Daily Nasal Congestion Score in CRSwNP Trials 1 and 2 | Trial 1 | Trial 2 |
|---|
| Placebo | omalizumab | Placebo | omalizumab |
|---|
| CRSwNP= chronic rhinosinusitis with nasal polyps; LS=least-square. Change from baseline was analyzed using a mixed-effect model of repeated measures (MMRM) model with baseline score, baseline score/timepoint (week) interaction as covariates, and the following factors: geographic region, asthma/aspirin sensitivity comorbidity status, timepoint, treatment group, treatment/timepoint interaction. |
| Number of patients | 65 | 72 | 65 | 62 |
| Nasal Polyp Score |
| Mean Baseline Score | 6.3 | 6.2 | 6.1 | 6.4 |
| LS Mean Change From Baseline at Week 24 | 0.1 | -1.1 | -0.3 | -0.9 |
| Difference in LS means vs. placebo | -1.1 | -0.6 |
| 95% CI for difference | -1.6, -0.7 | -1.1, -0.1 |
| p-value | <0.0001 | 0.0140 |
| 7-day Average of Daily Nasal Congestion Score |
| Mean Baseline Score | 2.5 | 2.4 | 2.3 | 2.3 |
| LS Mean Change From Baseline at Week 24 | -0.4 | -0.9 | -0.2 | -0.7 |
| Difference in LS means vs. placebo | -0.6 | -0.5 |
| 95% CI for difference | -0.8, -0.3 | -0.8, -0.2 |
| p-value | 0.0004 | 0.0017 |
The mean NPS and NCS at each study week by treatment group is shown in Figure 1.
Figure 1. Mean Change from Baseline in Nasal Congestion Score and Mean Change from Baseline in Nasal Polyp Score by Treatment Group in CRSwNP Trials 1 and 2
Omalizumab had statistically significant improvements on sense of smell score compared to placebo. Sense of smell was measured by a daily assessment on a 0 to 3 point severity scale (0=no symptoms, 1=mild symptoms, 2=moderate symptoms, 3=severe symptoms). The LS mean difference for change from baseline at Week 24 in sense of smell score in omalizumab compared to placebo was -0.3 (95% CI: -0.6, -0.1) in CRSwNP Trial 1 and -0.5 (95% CI: -0.7, -0.2) in CRSwNP Trial 2.
Omalizumab had statistically significant improvements on post-nasal drip compared to placebo. The LS mean difference for change from baseline at Week 24 in post-nasal drip score in omalizumab compared to placebo was -0.6 (95% CI: -0.8, -0.3) in CRSwNP Trial 1 and -0.5 (95% CI: -0.8, -0.3) in CRSwNP Trial 2.
Omalizumab had statistically significant improvements on runny nose compared to placebo. The LS mean difference for change from baseline at Week 24 in runny nose score in omalizumab compared to placebo was -0.4 (95% CI: -0.7, -0.2) in CRSwNP Trial 1 and -0.6 (95% CI: -0.9, -0.4) in CRSwNP Trial 2.
In a pre-specified pooled analysis of systemic corticosteroid use during the 24-week treatment period, there was no significant reduction in systemic corticosteroid use between the treatment arms. The proportion of patients taking systemic corticosteroid in omalizumab was 2.3% compared to 6.2% in placebo. The odds-ratio of systemic corticosteroid use with omalizumab compared to placebo was 0.4 (95% CI: 0.1, 1.5).
There were no sino-nasal surgeries reported, in either placebo or omalizumab arms, in either Trial.
Adult and Adolescent Patients 12 Years of Age and Older
The safety and efficacy of omalizumab for the treatment of chronic spontaneous urticaria (CSU), previously referred to as chronic idiopathic urticaria (CIU) was assessed in two placebo-controlled, multiple-dose clinical trials of 24 weeks' duration (CSU Trial 1; n= 319, [NCT01287117]) and 12 weeks' duration (CSU Trial 2; n=322, [NCT01292473]). Patients received omalizumab 75 mg, 150 mg, or 300 mg or placebo by SC injection every 4 weeks in addition to their baseline level of H1 antihistamine therapy for 24 or 12 weeks, followed by a 16-week washout observation period. A total of 640 patients (165 males, 475 females) were included for the efficacy analyses. Most patients were white (84%) and the median age was 42 years (range 12–72).
Disease severity was measured by a weekly urticaria activity score (UAS7, range 0–42), which is a composite of the weekly itch severity score (range 0–21) and the weekly hive count score (range 0–21). All patients were required to have a UAS7 of ≥16, and a weekly itch severity score of ≥8 for the 7 days prior to randomization, despite having used an H1 antihistamine for at least 2 weeks.
The mean weekly itch severity scores at baseline were fairly balanced across treatment groups and ranged between 13.7 and 14.5 despite use of an H1 antihistamine at an approved dose. The reported median durations of CSU at enrollment across treatment groups were between 2.5 and 3.9 years (with an overall subject-level range of 0.5 to 66.4 years).
In both CSU Trials 1 and 2, patients who received omalizumab 150 mg or 300 mg had greater decreases from baseline in weekly itch severity scores and weekly hive count scores than placebo at Week 12. Representative results from CSU Trial 1 are shown (Table 16); similar results were observed in CSU Trial 2. The 75-mg dose did not demonstrate consistent evidence of efficacy and is not approved for use.
Table 16. Change from Baseline to Week 12 in Weekly Itch Severity Score and Weekly Hive Count Score in CSU Trial 1Modified intent-to-treat (mITT) population: all patients who were randomized and received at least one dose of study medication.
| Omalizumab
75 mg | Omalizumab
150 mg | Omalizumab
300 mg | Placebo |
|---|
| n | 77 | 80 | 81 | 80 |
| Weekly Itch Severity Score |
| Mean Baseline Score (SD) | 14.5 (3.6) | 14.1 (3.8) | 14.2 (3.3) | 14.4 (3.5) |
| Mean Change Week 12 (SD) | −6.46 (6.14) | −6.66 (6.28) | −9.40 (5.73) | −3.63 (5.22) |
| Difference in LS means vs. placebo | −2.96 | −2.95 | −5.80 | |
| 95% CI for difference | −4.71, −1.21 | −4.72, −1.18 | −7.49, −4.10 | - |
| Weekly Hive Count Score Score measured on a range of 0–21 |
| Mean Baseline Score (SD) | 17.2 (4.2) | 16.2 (4.6) | 17.1 (3.8) | 16.7 (4.4) |
| Mean Change Week 12 (SD) | −7.36 (7.52) | −7.78 (7.08) | −11.35 (7.25) | −4.37 (6.60) |
| Difference in LS means vs. placebo | −2.75 | −3.44 | −6.93 | |
| 95% CI for difference | −4.95, −0.54 | −5.57, −1.32 | −9.10, −4.76 | - |
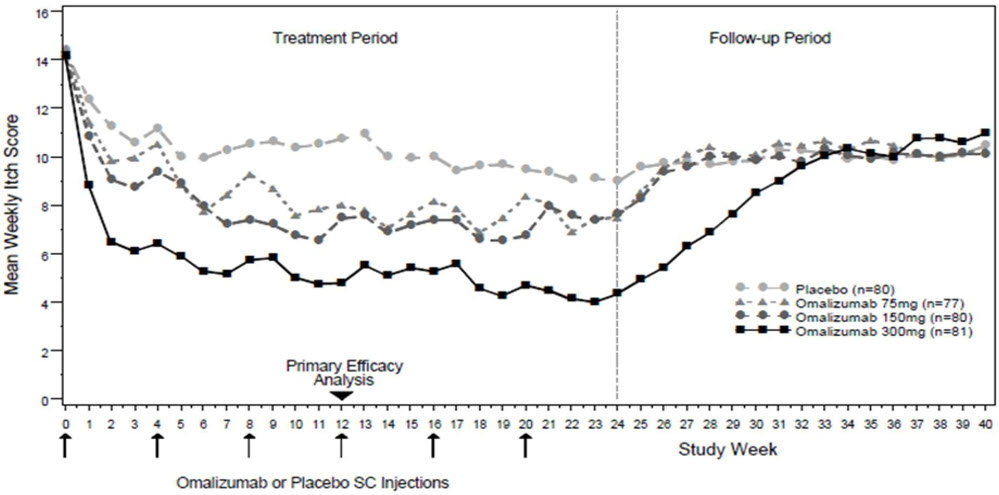
The mean weekly itch severity score at each study week by treatment groups is shown in Figure 2. Representative results from CSU Trial 1 are shown; similar results were observed in CSU Trial 2. The appropriate duration of therapy for CSU with omalizumab has not been determined.
Figure 2. Mean Weekly Itch Severity Score by Treatment Group Modified Intent to Treat Patients in CSU Trial 1
In CSU Trial 1, a larger proportion of patients treated with omalizumab 300 mg (36%) reported no itch and no hives (UAS7=0) at Week 12 compared to patients treated with omalizumab 150 mg (15%), omalizumab 75 mg (12%), and placebo group (9%). Similar results were observed in CSU Trial 2.
Injection (Prefilled Syringe)
OMLYCLO (omalizumab-igec) injection is a clear to opalescent and colorless to pale brownish-yellow solution for subcutaneous use.
OMLYCLO injection is provided in a single-dose prefilled glass syringe with a 27-gauge special thin wall needle. The syringe plunger stopper and needle cap are not made with natural rubber latex.
OMLYCLO is available as prefilled syringe as described in Table 17.
Table 17. OMLYCLO Prefilled Syringe Strengths and Package Configurations| Package Configuration | Strength | NDC | Syringe Counts |
|---|
| 1 prefilled syringe with a 27-gauge staked needle syringe with a yellow plunger rod | 75 mg/ 0.5 mL | 72606-035-01 | 1 |
| 1 prefilled syringe with a 27-gauge staked needle syringe with a blue plunger rod | 150 mg/mL | 72606-036-01 | 1 |
| 1 prefilled syringe with a 27-gauge staked needle syringe with a white plunger rod | 300 mg/2 mL (150 mg/mL) | 72606-054-01 | 1 |
| 2 prefilled syringes with a 27-gauge staked needle syringe with a white plunger rod | 300 mg/2 mL (150 mg/mL) | 72606-054-02 | 2 (2 × 1) (multipack) |
The OMLYCLO prefilled syringe is not made with natural rubber.
Anaphylaxis
Inform patients of the risk of life-threatening anaphylaxis with OMLYCLO including the following points [see Boxed Warning and Warnings and Precautions (5.1)]:
- There have been reports of anaphylaxis occurring up to 4 days after administration of omalizumab products
- Initiate OMLYCLO only in a healthcare setting by healthcare providers
- Observe patients closely following administration
- Inform patients of the signs and symptoms of anaphylaxis
- Instruct patients to seek immediate medical care should such signs or symptoms occur
Potential Medication Error Related to Emergency Treatment of Anaphylaxis
Advise patients, parents, or caregivers that OMLYCLO should not be used for the emergency treatment of allergic reactions, including anaphylaxis [see Warnings and Precautions (5.9)].
Continuation of Other Medications
Instruct patients receiving OMLYCLO not to decrease the dose of, or stop taking any other asthma, CRSwNP, CSU or IgE-mediated food allergy medications or allergen immunotherapy unless otherwise instructed by their physician. Inform patients that they may not see immediate improvement in their asthma, CRSwNP, CSU or IgE-mediated food allergy symptoms after beginning OMLYCLO therapy.
Instruction on Injection Technique
If a patient or caregiver is to administer subcutaneous OMLYCLO prefilled syringe, instruct on injection technique and assess ability to inject subcutaneously to ensure proper administration of OMLYCLO. For patients who require more than 1 injection to complete their prescribed dose, instruct patients to administer all injections consecutively and in one sitting [See Dosage and Administration (2.7), Warnings and Precautions (5.1), and Instructions for Use].
Manufactured by:
CELLTRION, Inc.
23, Academy-ro, Yeonsu-gu,
Incheon, 22014,
Republic of Korea
U.S. License Number: 1996
Distributed by:
CELLTRION USA, Inc.
1 Evertrust Plaza Suite 1207,
Jersey City, NJ, 07302
Revised Date: 12/2025