Hepatotoxicity and Elevated Liver Function Tests
In the phase 3 trial, a total of 19 patients (11.6%) in the prednisone group and 22 patients (13.3%) in the TAVNEOS group had hepatic-related adverse reactions, including hepatobiliary adverse reactions and liver enzyme abnormalities. Study medication was paused or discontinued permanently due to hepatic-related adverse reactions in 5 patients (3.0%) in the prednisone group and 9 patients (5.4%) in the TAVNEOS group. Serious hepatic-related adverse reactions were reported in 6 patients (3.7%) in the prednisone group and 9 patients (5.4%) in the TAVNEOS group. A serious hepatic-related adverse reaction was reported in 1 patient in the TAVNEOS group in the phase 2 studies.
Angioedema
In the phase 3 trial, 2 patients (1.2%) in the TAVNEOS group had angioedema; one event was a serious adverse reaction requiring hospitalization.
Elevated Creatine Phosphokinase
In the phase 3 trial, 1 patient (0.6%) in the prednisone group and 6 patients (3.6%) in the TAVNEOS group had increased creatine phosphokinase. One TAVNEOS-treated patient discontinued treatment due to increased creatine phosphokinase.
Risk Summary
There are no adequate and well-controlled studies with TAVNEOS in pregnant women to inform a drug-associated risk. In animal reproduction studies, oral administration of avacopan to pregnant hamsters and rabbits during the period of organogenesis produced no evidence of fetal harm with exposures up to approximately 5 and 0.6 times, respectively, the exposure at the maximum recommended human dose (MRHD) of 30 mg twice daily (on an area under the curve [AUC] basis). Avacopan caused an increase in the number of abortions in rabbits at an exposure 0.6 times the MRHD (see Animal Data).
The background risk of major birth defects and miscarriage for the indicated population are unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data
Animal Data
In an embryo-fetal development study with pregnant hamsters dosed by the oral route during the period of organogenesis from gestation days 6 to 12, avacopan produced an increase in the incidence of a skeletal variation, described as supernumerary ribs, at an exposure that was 5 times the MRHD (on an AUC basis with a maternal oral dose of 1000 mg/kg/day). No structural abnormalities were noted with exposures up to 5 times the MRHD (on an AUC basis with maternal oral doses up to 1000 mg/kg/day).
In an embryo-fetal development study with pregnant rabbits dosed by the oral route during the period of organogenesis from gestation days 6 to 18, avacopan caused an increase in the number of abortions at an exposure 0.6 times the MRHD (on an AUC basis with a maternal oral dose of 200 mg/kg/day), however, no evidence of fetal harm was observed with such exposures. Maternal toxicity, as evidenced by decreased body weight gains, was observed at exposures 0.6 times and higher than the MRHD (on an AUC basis with maternal oral doses of 30 mg/kg/day and higher).
In a prenatal and postnatal development study with pregnant hamsters dosed by the oral route during the periods of gestation and lactation from gestation day 6 to lactation day 20, avacopan had no effects on the growth and development of offspring with exposures up to approximately 5 times the MRHD (on an AUC basis with maternal oral doses up to 1000 mg/kg/day).
Risk Summary
There are no available data on the effects of avacopan on the breast-fed child or on milk production. It is unknown whether avacopan is secreted in human milk. Avacopan was detected in the plasma of undosed hamster pups nursing from drug-treated dams (see Animal Data). The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for TAVNEOS and any potential adverse effects on the breast-fed infant from TAVNEOS or from the underlying maternal condition.
Animal Data
Avacopan has not been measured in the milk of lactating animals; however, it was detected in the plasma of nursing offspring in a pre- and post-natal development study with hamsters at a pup to maternal plasma ratio of 0.37. This finding suggests that avacopan is secreted into the milk of lactating hamsters [see Nonclinical Toxicology (13.1)].
Cardiac Electrophysiology
At the approved recommended dose, TAVNEOS does not prolong the QT interval to any clinically relevant extent.
Distribution
The plasma protein binding (e.g., to albumin and α1-acid glycoprotein) of avacopan and metabolite M1 is greater than 99.9%. The apparent volume of distribution of avacopan is estimated to be 345 L.
Elimination
Based on population pharmacokinetic analysis, the estimated total apparent body clearance (CL/F) of avacopan is 16.3 L/h. Following a single dose of 30 mg avacopan with food, the mean elimination half-lives of avacopan and M1 are 97.6 hours and 55.6 hours, respectively, in healthy subjects.
Metabolism
CYP3A4 is the major enzyme responsible for the clearance of avacopan and for the formation and clearance of the major circulating metabolite M1, a mono-hydroxylated product of avacopan. M1 was present at ~12% of the total drug-related materials in plasma and has approximately the same activity as avacopan on the C5aR.
Excretion
The main route of clearance of avacopan is metabolism followed by biliary excretion of the metabolites into feces. Following oral administration of radiolabelled avacopan, about 77% and 10% of the radioactivity was recovered in feces and urine, respectively, and 7% and < 0.1% of the radioactive dose was recovered as unchanged avacopan in feces and urine, respectively.
Specific Populations
No clinically significant differences in plasma exposure of avacopan and metabolite M1 were observed based on race (White, Asian, Black), gender (female 31%), age (18 to 83 years), body weight (40.3-174 kg), and renal function (eGFR 14-170 mL/min/1.73 m2 at baseline).
Patients with Hepatic Impairment
Mild (Child-Pugh A) or moderate (Child-Pugh B) hepatic impairment had no clinically relevant effect on avacopan and M1 plasma exposure. In subjects with mild or moderate hepatic impairment, avacopan AUC increased by 12% and 12%, respectively, Cmax decreased by 13% and 17%, respectively, compared to subjects with normal liver function. In subjects with mild or moderate hepatic impairment, M1 AUC increased by 11% and 18%, respectively, Cmax decreased by 5% and 16%, respectively, compared to subjects with normal liver function.
TAVNEOS has not been studied in subjects with severe hepatic impairment (Child-Pugh Class C).
Drug Interaction Studies
Effects of Other Drugs on TAVNEOS
Avacopan is primarily metabolized by CYP3A4. In vitro studies indicate that avacopan is not a substrate of BCRP and P-gp efflux, and OATP1B1 and OATP1B3 uptake transporters. M1 is a substrate of P-gp but is not a substrate of BCRP efflux, and OATP1B1 and OATP1B3 uptake transporters. Summary of results from a clinical study which evaluated the effect of co-administered drugs on avacopan and M1 plasma exposures is shown in Table 2.
Table 2. Changes in Pharmacokinetics of Avacopan and M1 in the Presence of Co-administered Drugs| Co-administered Drug | Regimen of Co-administered Drug | Ratio (90% CI) Ratios for Cmax and AUC comparing co-administration of the medication with avacopan vs. administration of avacopan alone. |
|---|
| Cmax | AUC |
|---|
| CI: Confidence interval |
| Strong CYP3A4 inhibitor: itraconazole | 200 mg once daily for 4 days | Avacopan | 1.87
(1.70, 2.06) | 2.19
(2.00, 2.41) |
| M1 | 1.03
(0.95, 1.11) | 1.19
(1.11, 1.28) |
| Strong CYP3A4 inducer: rifampin | 600 mg once daily for 11 days | Avacopan | 0.21
(0.18, 0.25) | 0.07
(0.06, 0.10) |
| M1 | 0.27
(0.23, 0.31) | 0.07
(0.06, 0.09) |
Proton-pump inhibitors such as omeprazole are not expected to have a clinically relevant effect on avacopan plasma exposure.
Effect of TAVNEOS on Other Drug Substances
In vitro studies indicate that avacopan does not inhibit CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, and CYP2D6, and does not induce CYP1A2 and CYP2B6, but shows induction and time-dependent inhibition of CYP3A4. In vitro studies indicate that M1 does not inhibit CYP1A2, CYP2B6, CYP2C8, CYP2C19, and CYP2D6, and has a low potential to induce CYP3A4, CYP1A2 and CYP2B6, but may inhibit CYP2C9 and CYP3A4.
In vitro studies indicate that avacopan and M1 do not inhibit the transporters P-gp, BCRP, OATP1B1, OATP1B3, OCT2, OAT1, OAT3, MATE1, and MATE2K at clinically relevant concentrations.
Summary of results from clinical studies which evaluated the effect of avacopan on other drugs is shown in Table 3.
Table 3. Change in Pharmacokinetics of Co-administered Drugs in the Presence of Avacopan| Co-administered Drug | Regimen of Avacopan | Ratio (90% CI) Ratios for Cmax and AUC comparing co-administration of the medication with avacopan vs. administration of medication alone. |
|---|
| Cmax | AUC |
|---|
| CI: Confidence interval |
| Sensitive CYP3A4 substrate: simvastatin | 60 mg twice daily for 7 days (fed) Avacopan doses were taken with food. Avacopan systemic exposure represents the therapeutic exposure at steady state with 30 mg twice daily under fed conditions. | 3.20
(2.49, 4.10) | 3.53
(3.23, 3.85) |
| Sensitive CYP3A4 substrate: midazolam | 30 mg twice daily for 11 days (fasted) Avacopan doses were taken under fasted conditions. No food was allowed for at least 2 hours post dose for the morning doses. Avacopan systemic exposure was below the therapeutic exposure at steady state with 30 mg twice daily under fed conditions. | 1.55
(1.41, 1.69) | 1.81
(1.65, 1.98) |
| Sensitive CYP2C9 substrate: celecoxib | 30 mg twice daily for 11 days (fasted) | 1.64
(1.34, 2.00) | 1.15
(1.03, 1.28) |
Carcinogenesis
Two-year carcinogenicity studies in Sprague-Dawley rats and Syrian hamsters were conducted to assess the carcinogenic potential of avacopan. Avacopan demonstrated no tumorigenic potential in a study with rats that received oral doses up to 100 mg/kg/day (approximately 3 times the MRHD in adults on an AUC basis) and a study in hamsters that received oral doses up to 100 mg/kg/day (approximately 6 times the MRHD in adults on an AUC basis).
Mutagenesis
Avacopan was not mutagenic or clastogenic in the following assays: in vitro bacterial reverse mutation (Ames) test, in vitro mouse lymphoma assay, and in vivo rat micronucleus test.
Impairment of Fertility
Fertility and reproductive performance were unaffected in male and female hamsters that received avacopan by the oral route at dose levels up to 1000 mg/kg/day (approximately 7 times the MRHD on an AUC basis).
Remission at Week 26 and Sustained Remission at Week 52
Remission was achieved by 72.3% of patients in the TAVNEOS group and 70.1% of patients in the prednisone group at Week 26 (treatment difference: 3.4%, 95% CI [-6.0%, 12.8%]). At Week 52, a significantly higher percentage of patients had sustained remission in TAVNEOS group (65.7%) compared to the prednisone group (54.9%), as presented in Table 4.
Table 4. Sustained Remission at Week 52 in Phase 3 Trial (Intent-to-Treat Population) | Prednisone
(N = 164)
n (%) | TAVNEOS
(N = 166)
n (%) | Estimate of Treatment Difference | p-value 2-sided p-value of Summary Score Test (Agresti 2013). |
|---|
| CI = confidence interval; N = number of patients in the analysis population for the specified treatment group; n = number of patients with disease remission; % = 100*n/N |
| Sustained Remission at Week 52 | 90 (54.9%) | 109 (65.7%) | 12.5% Summary Score estimate of the common difference in remission rates (Agresti 2013) by using inverse-variance stratum weights. | 0.013 |
| 95% CI | (46.9, 62.6) Clopper and Pearson exact CI. | (57.9, 72.8) | (2.6, 22.3) Miettinen-Nurminen (Score) confidence limits for the common difference in remission rates. |
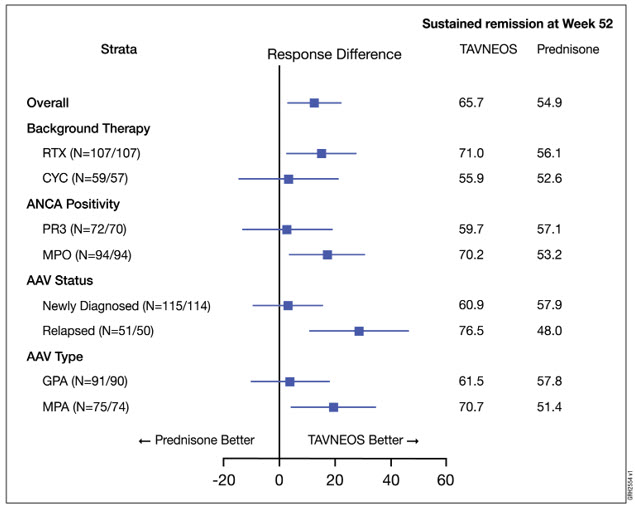
In pre-specified subgroup efficacy analyses, sustained remission at 52 weeks in patients was examined based on stratification factors and GPA/MPA disease. The results are displayed in Figure 1 below.
Figure 1. Forest Plot of Sustained Remission at Week 52 Based on Disease Related Variables
AAV = ANCA-associated vasculitis, CYC = cyclophosphamide, GPA = granulomatosis with polyangiitis, MPA = microscopic polyangiitis, MPO = myeloperoxidase positive, PR3 = anti-proteinase 3 positive, and RTX = rituximab. The treatment difference between TAVNEOS and prednisone groups is presented with point estimate and 95% confidence interval using normal approximation. The notation N = XXX/YYY indicates the number of patients randomized who received at least one dose of drug in TAVNEOS arm and prednisone arm, respectively. Subgroup findings should be interpreted with caution due to small sample sizes and overlapping subgroups.
TAVNEOS® (avacopan)
Manufactured for:
ChemoCentryx, Inc.
One Amgen Center Drive
Thousand Oaks, CA 91320-1799
Patent: https://pat.amgen.com/tavneos
© 2021, 2024, 2026 ChemoCentryx, Inc. All rights reserved.
1xxxxxx – v4