Adults
EXPLORER-HCM
The efficacy of CAMZYOS was evaluated in EXPLORER-HCM (NCT-03470545) a phase 3, double-blind, randomized, placebo-controlled, multicenter, international, parallel-group trial in 251 adults with symptomatic NYHA class II and III obstructive HCM, LVEF ≥55%, and LVOT peak gradient ≥50 mmHg at rest or with provocation.
Patients on dual therapy with beta blocker and calcium channel blocker treatment or monotherapy with disopyramide or ranolazine were excluded. Patients with a known infiltrative or storage disorder causing cardiac hypertrophy that mimicked obstructive HCM, such as Fabry disease, amyloidosis, or Noonan syndrome with left ventricular hypertrophy, were also excluded.
Patients were randomized in a 1:1 ratio to receive either a starting dose of 5 mg of CAMZYOS or placebo once daily for 30 weeks. Treatment assignment was stratified by baseline NYHA functional class, baseline use of beta blockers, and type of ergometer (treadmill or exercise bicycle).
Groups were well matched with respect to age (mean 59 years), BMI (mean 30 kg/m2), heart rate (mean 62 bpm), blood pressure (mean 128/76 mmHg), and race (90% Caucasian). Males comprised 54% of the CAMZYOS group and 65% of the placebo group.
At baseline, approximately 73% of the randomized patients were NYHA class II and 27% were NYHA class III. The mean LVEF was 74%, and the mean Valsalva LVOT gradient was 73 mmHg. About 10% had prior septal reduction therapy, 75% were on beta blockers, 17% were on calcium channel blockers, and 14% had a history of atrial fibrillation.
All patients were initiated on CAMZYOS 5 mg (or matching placebo) once daily, and the dose was periodically adjusted to optimize patient response (decrease in LVOT gradient with Valsalva maneuver) and maintain LVEF ≥50%. The dose was also informed by plasma concentrations of CAMZYOS.
In the CAMZYOS group, at the end of treatment, 49% of patients were receiving the 5-mg dose, 33% were receiving the 10-mg dose, and 11% were receiving the 15-mg dose. Three patients temporarily interrupted their dose due to LVEF <50%, of whom two resumed treatment at the same dose and one had the dose reduced from 10 mg to 5 mg.
Primary endpoint
The primary composite functional endpoint, assessed at 30 weeks, was defined as the proportion of patients who achieved either improvement of peak oxygen consumption (pVO2) by ≥1.5 mL/kg/min plus improvement in NYHA class by at least 1 or improvement of pVO2 by ≥3.0 mL/kg/min plus no worsening in NYHA class.
A greater proportion of patients met the primary endpoint at Week 30 in the CAMZYOS group compared to the placebo group (37% vs. 17%, respectively, p=0.0005; see Table 2).
Table 2: Primary Endpoint at 30 Weeks | CAMZYOS n (%) N = 123 | Placebo n (%) N = 128 | Difference (95% CI) | p-value |
Total responders | 45 (37%) | 22 (17%) | 19% (9, 30) | 0.0005 |
Change from baseline pVO2 ≥1.5 mL/kg/min and decreased NYHA | 41 (33%) | 18 (14%) | 19% (9, 30) | |
Change from baseline pVO2 ≥3 mL/kg/min and NYHA not increased | 29 (23%) | 14 (11%) | 13% (3, 22) | |
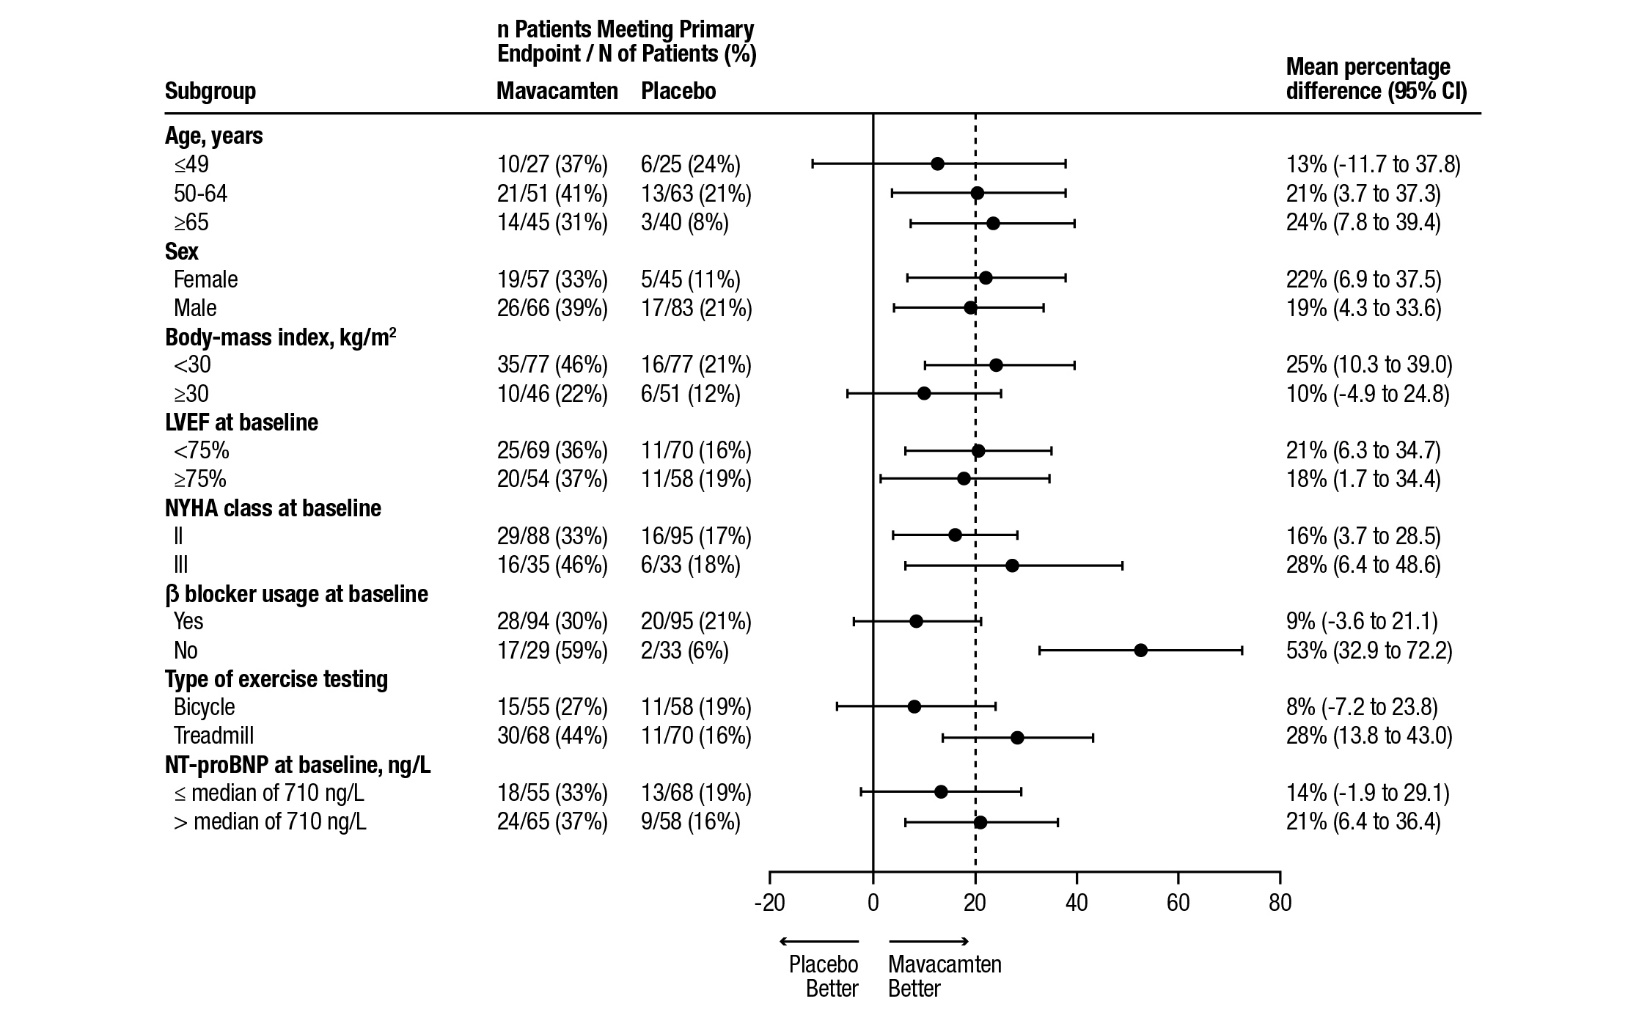
A range of demographic characteristics, baseline disease characteristics, and baseline concomitant medications were examined for their influence on outcomes. Results of the primary analysis consistently favored CAMZYOS across all subgroups analyzed (Figure 5).
Figure 5: Subgroup Analysis of the Primary Composite Functional Endpoint

Figure 4 Subgroup Analysis Of The Primary Composite Functional Endpoint (Fig Subgroupanalysisoftheprimarycompositefunctionalendpoint)
The dashed vertical line represents the overall treatment effect and the solid vertical line (no effect) indicates no difference between treatment groups.
Note: The figure above presents effects in various subgroups, all of which are baseline characteristics. The 95% confidence limits that are shown do not take into account the number of comparisons made and may not reflect the effect of a particular factor after adjustment for all other factors. Apparent homogeneity or heterogeneity among groups should not be over-interpreted.
Although the benefit of mavacamten was smaller in patients on background beta blocker therapy compared to those who were not (attenuated improvement in pVO2), analyses of other secondary endpoints (symptoms, LVOT gradient) suggest that patients might benefit from mavacamten treatment regardless of beta blocker use.
Secondary endpoints
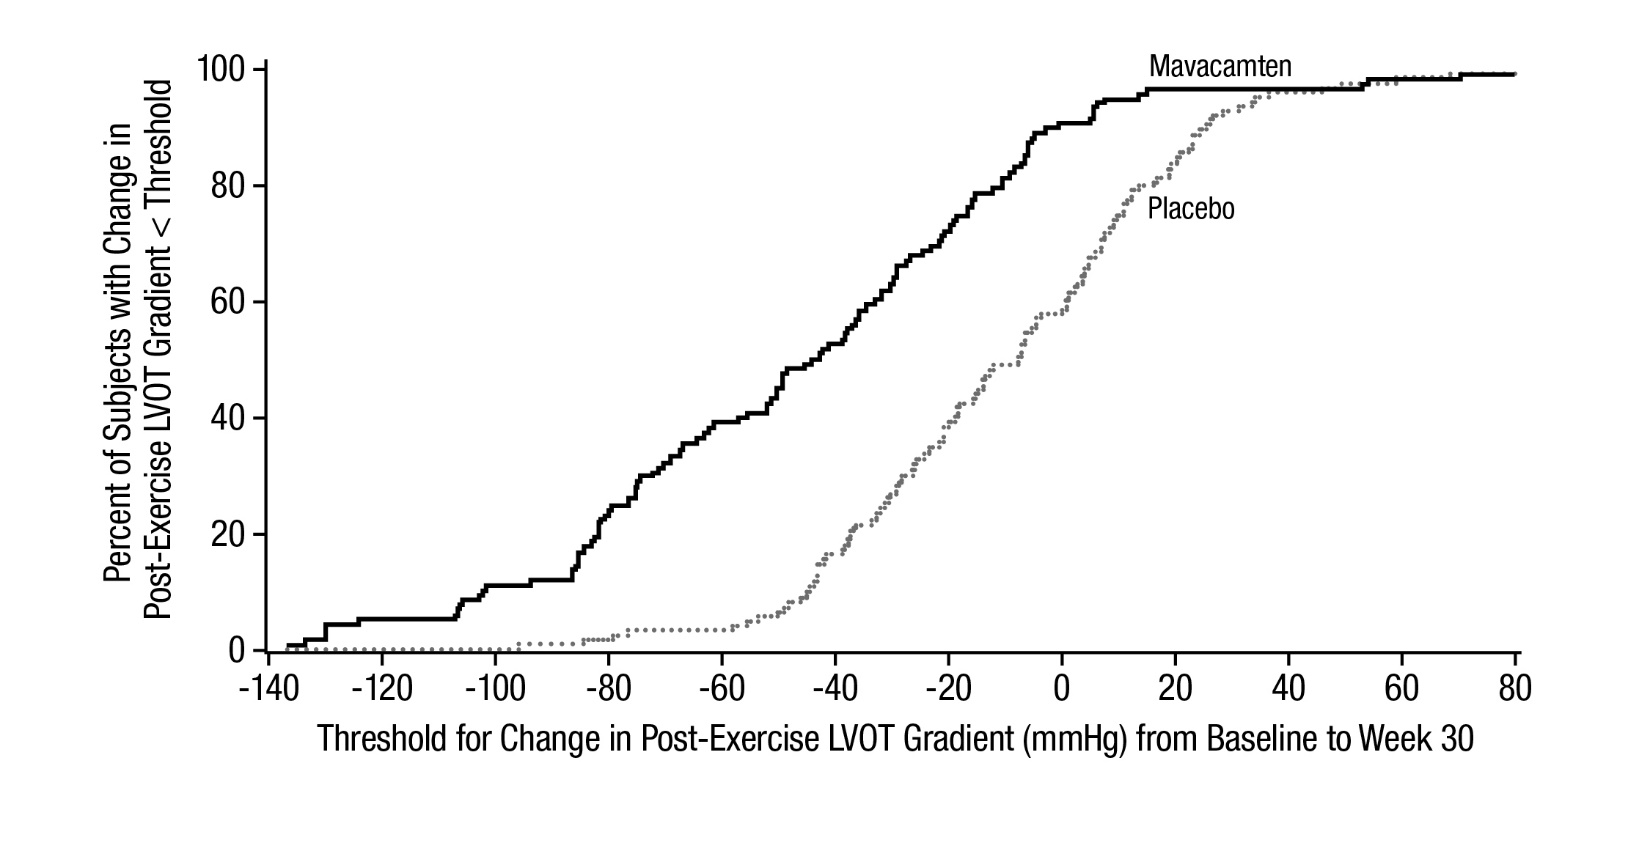
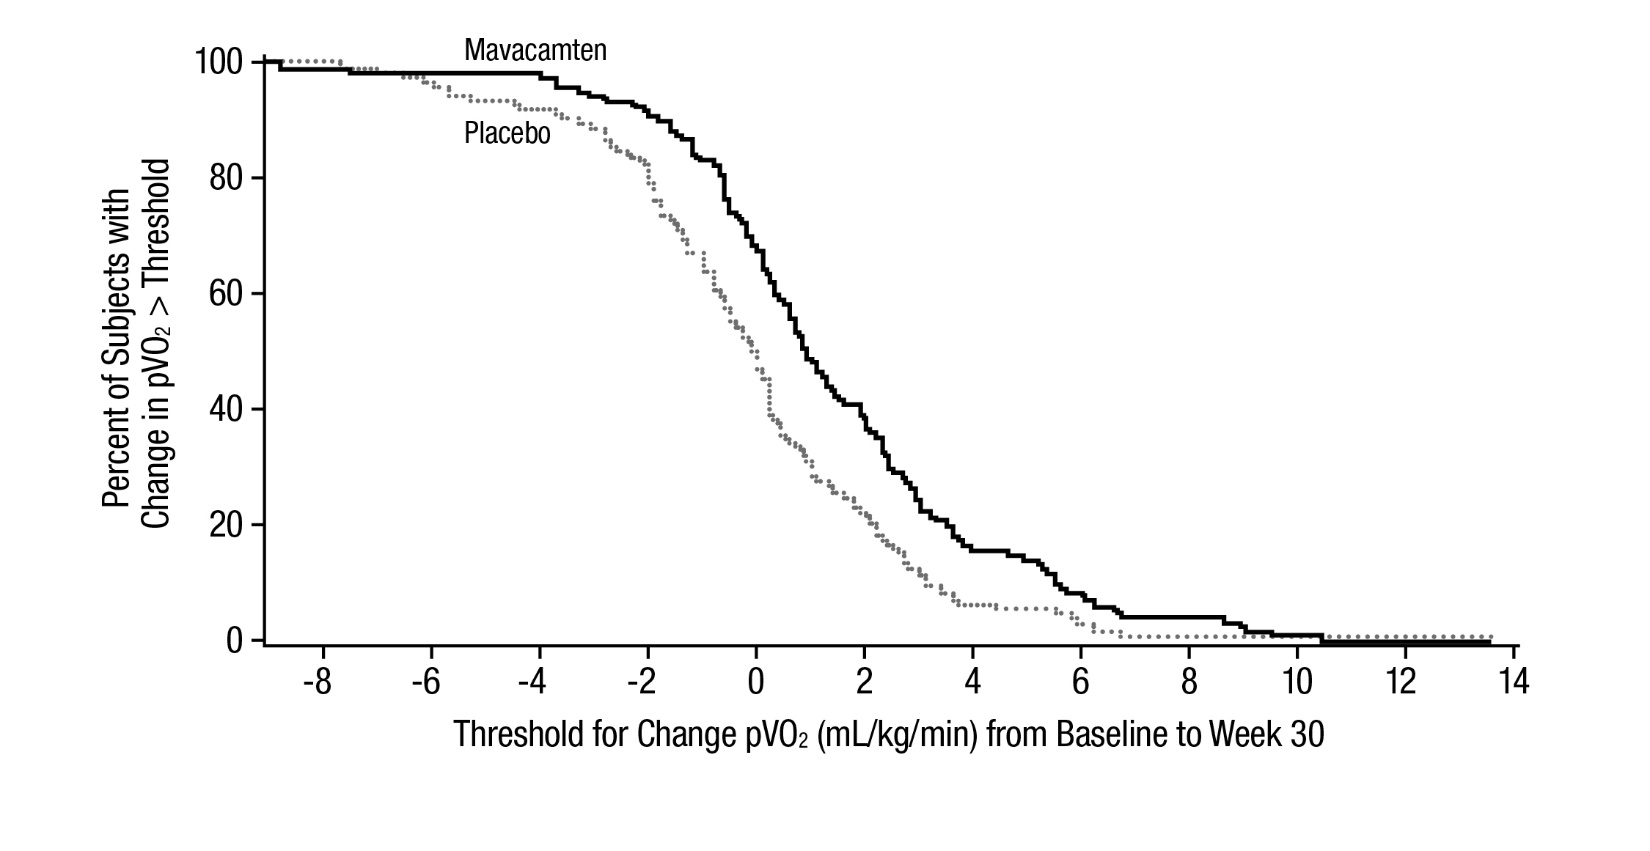
The treatment effects of CAMZYOS on LVOT obstruction, functional capacity, and health status were assessed by change from baseline through Week 30 in post-exercise LVOT peak gradient, change in pVO2, proportion of patients with improvement in NYHA class, Kansas City Cardiomyopathy Questionnaire-23 (KCCQ-23) Clinical Summary Score (CSS), and Hypertrophic Cardiomyopathy Symptom Questionnaire (HCMSQ) Shortness of Breath (SoB) domain score. At Week 30, patients receiving CAMZYOS had greater improvement compared to the placebo group across all secondary endpoints (Table 3, Figure 6, Figure 7, Table 4, and Figures 8-11).
Table 3: Change from Baseline to Week 30 in Post-Exercise LVOT Gradient, pVO2, and NYHA Class | CAMZYOS N=123 | Placebo N=128 | Difference (95% CI) | p-value |
Post-Exercise LVOT gradient (mmHg), mean (SD) | -47 (40) | -10 (30) | -35 (-43, -28) | <0.0001 |
pVO2 (mL/kg/min), mean (SD) | 1.4 (3.1) | -0.1 (3.0) | 1.4 (0.6, 2.1) | <0.0006 |
Number (%) with NYHA Class improved ≥1 | 80 (65%) | 40 (31%) | 34% (22%, 45%) | <0.0001 |
Figure 6: Cumulative Distribution of Change from Baseline to Week 30 in LVOT Peak Gradient

Fig_cumulativedistributionofchangefrombaselinetoweek30inlvotpeakgradient (Fig Cumulativedistributionofchangefrombaselinetoweek30inlvotpeakgradient)
Figure 7: Cumulative Distribution of Change from Baseline to Week 30 in pVO2

Fig_cumulativedistributionofchangefrombaselinetoweek30inpvo2 (Fig Cumulativedistributionofchangefrombaselinetoweek30inpvo2)
Table 4: Change from Baseline to Week 30 in KCCQ-23 CSS and HCMSQ SoB Domain†The KCCQ‑23 CSS is derived from the Total Symptom Score (TSS) and the Physical Limitations (PL) score of the KCCQ‑23. The CSS ranges from 0 to 100 with higher scores representing less severe symptoms and/or physical limitations.
‡The HCMSQ SoB domain score measures the frequency and severity of shortness of breath. The HCMSQ SoB domain score ranges from 0 to 18 with lower scores representing less shortness of breath.
Missing data were not imputed to summarize the baseline and change from baseline to Week 30 values. Difference in mean change from baseline between treatment groups was estimated using a mixed model for repeated measures. |
| Baseline, Mean (SD) | Change from Baseline to Week 30, Mean (SD) | Difference, LS Mean (95%CI) and p-value |
| CAMZYOS | Placebo | CAMZYOS | Placebo |
KCCQ‑23 CSS† | n=99 71 (16) | n=97 71 (19) | 14 (14) | 4 (14) | 9 (5, 13) p<0.0001 |
KCCQ-23 TSS | 71 (17) | 69 (22) | 12 (15) | 5 (16) | |
KCCQ-23 PL | 70 (18) | 72 (19) | 15 (17) | 4 (15) | |
HCMSQ SoB‡ | n=108 5 (3) | n=109 5 (3) | -3 (3) | -1 (2) | -2 (-2, -1) p<0.0001 |
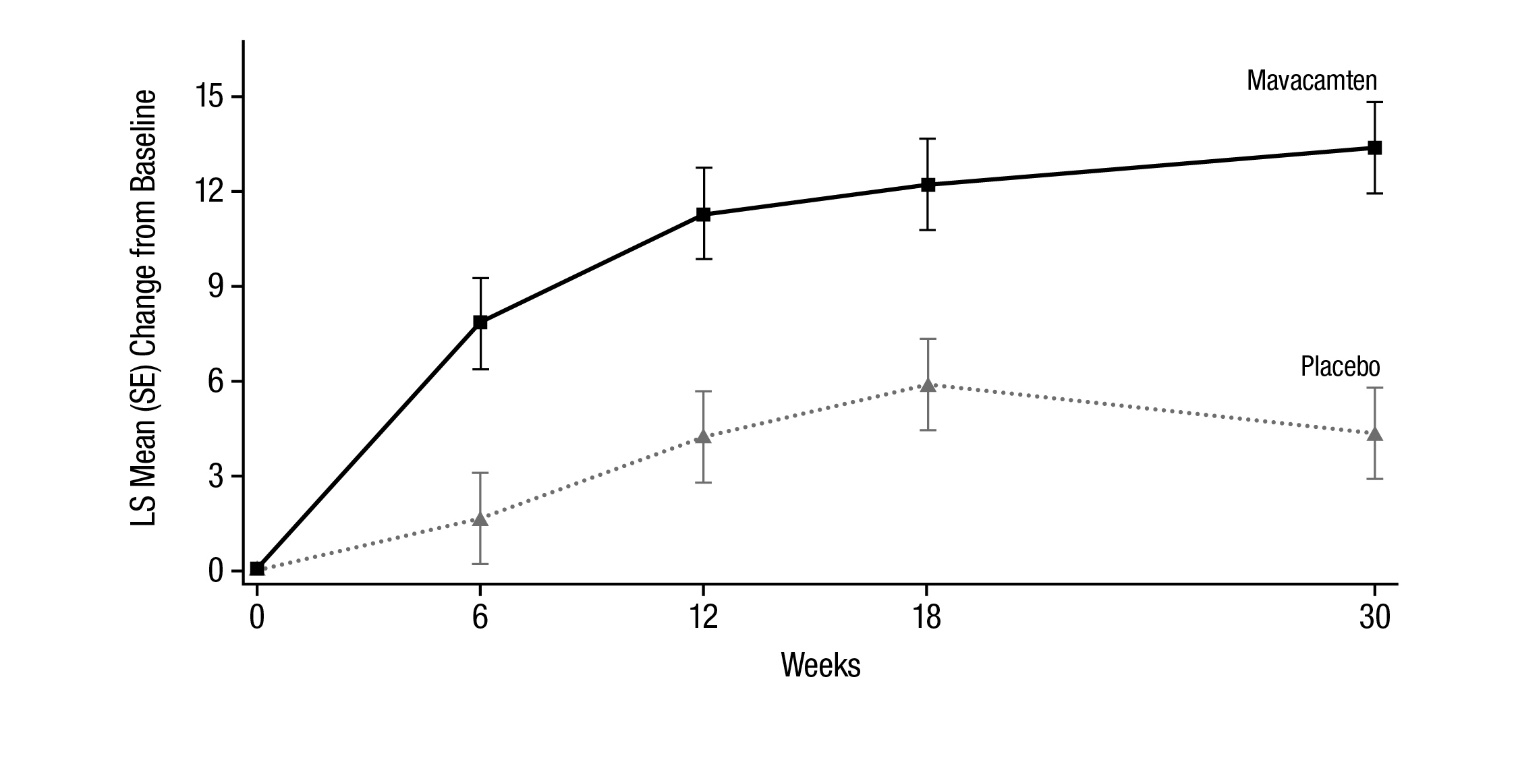
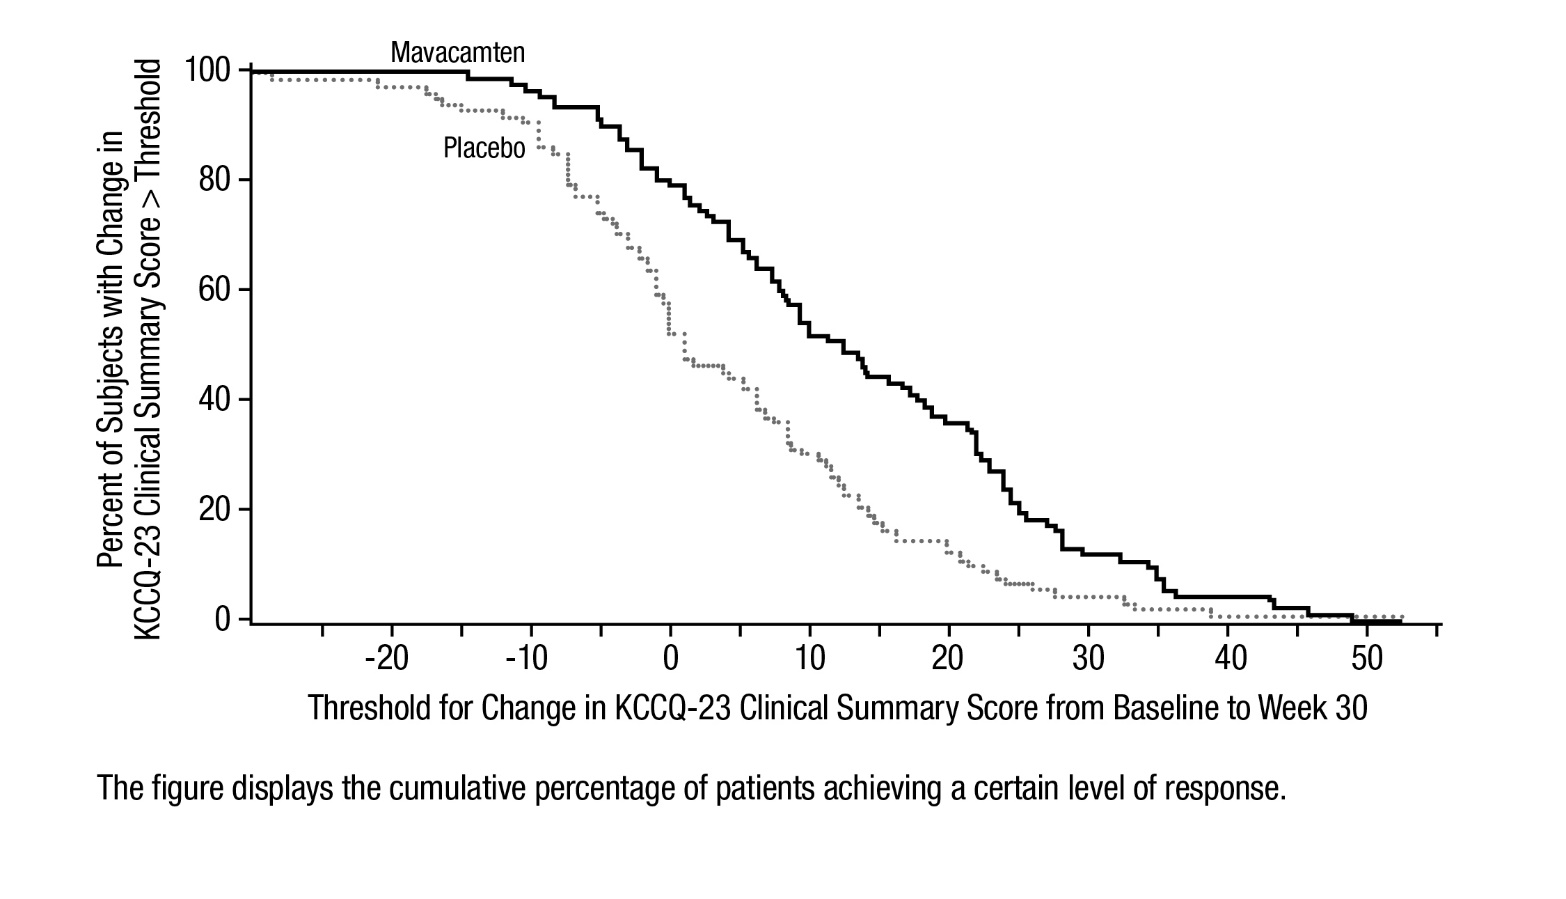
Figure 8 shows the time course for changes in KCCQ-23 CSS. Figure 9 shows the distribution of changes from baseline to Week 30 for KCCQ-23 CSS.
Figure 8: KCCQ-23 Clinical Summary Score: Mean Change from Baseline Over Time

Fig_kccq-23clinicalsummaryscoremeanchangefrombaselineovertime (Fig Kccq 23clinicalsummaryscoremeanchangefrombaselineovertime)
Figure 9: KCCQ-23 Clinical Summary Score: Cumulative Distribution of Change from Baseline to Week 30

Fig_kccq-23clinicalsummaryscorecumalativedistributionofchangefrombaselinetoweek30 (Fig Kccq 23clinicalsummaryscorecumalativedistributionofchangefrombaselinetoweek30)
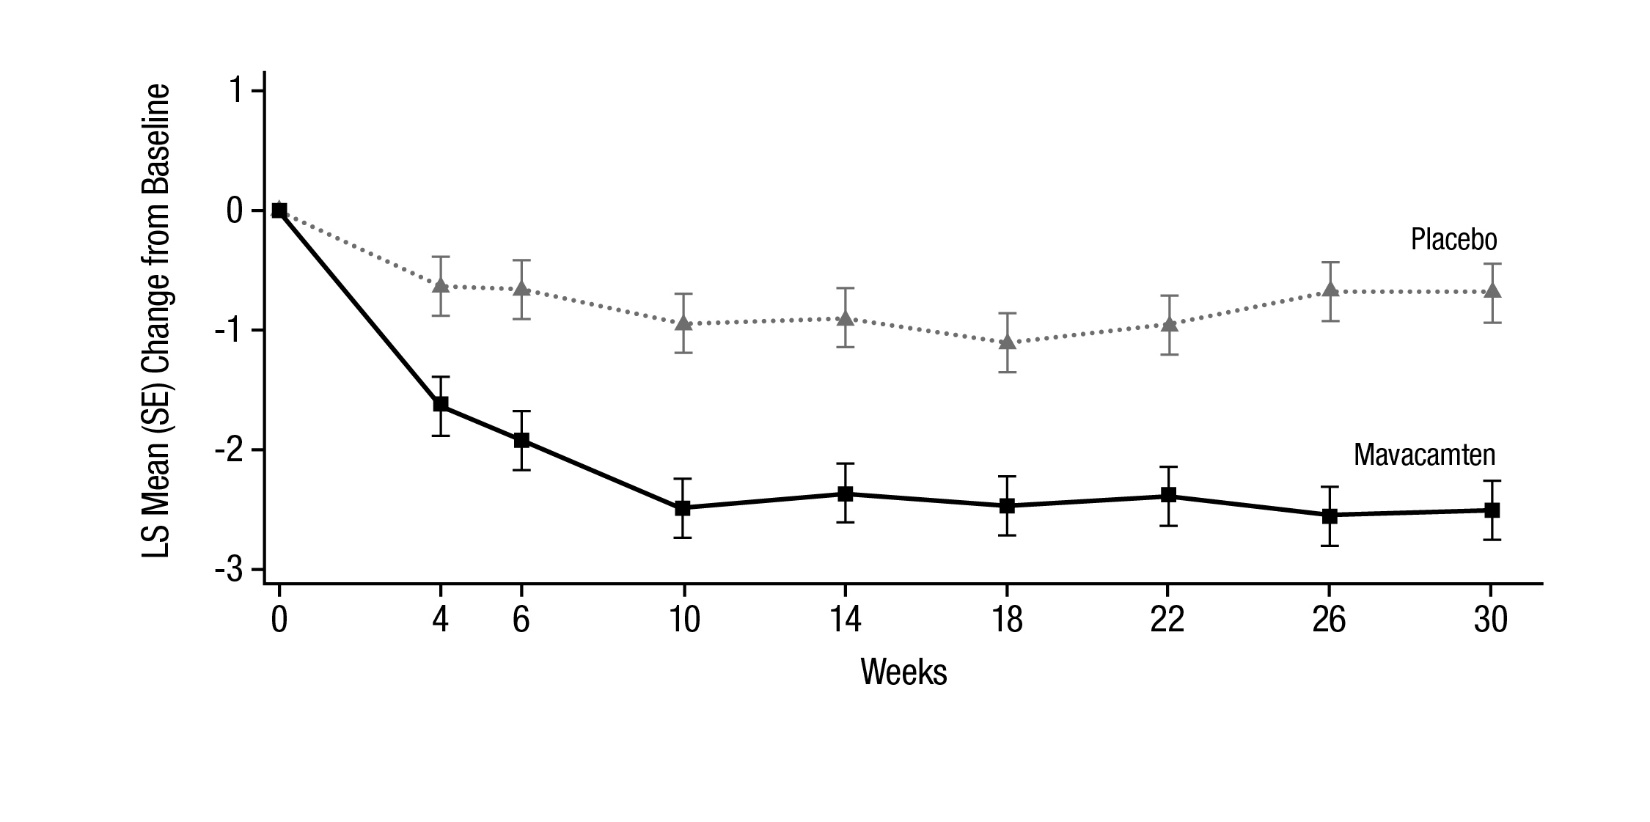
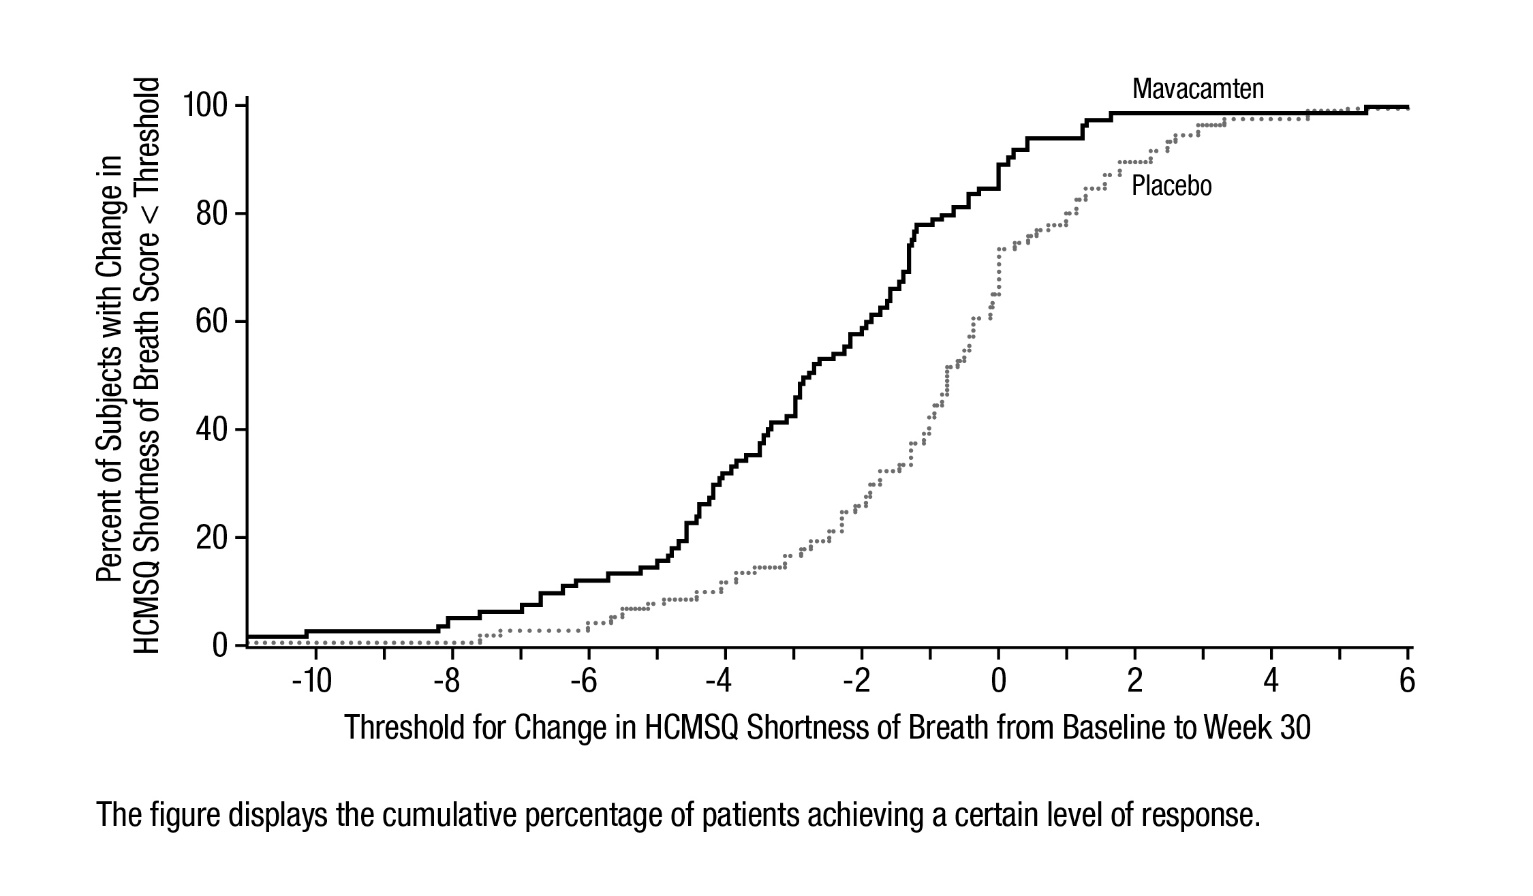
Figure 10 shows the time course for changes in HCMSQ SoB. Figure 11 shows the distribution of changes from baseline to Week 30 for HCMSQ SoB.
Figure 10: HCMSQ Shortness of Breath Domain: Mean Change from Baseline Over Time

Fig_hcmsqshortnessofbreathdomainmeanchangefrombaselineovertime (Fig Hcmsqshortnessofbreathdomainmeanchangefrombaselineovertime)
Figure 11: HCMSQ Shortness of Breath Domain: Cumulative Distribution of Change from Baseline to Week 30

Fig_hcmsqshortnessofbreathdomaincummlativedistributionofchangefrombaselinetoweek30 (Fig Hcmsqshortnessofbreathdomaincummlativedistributionofchangefrombaselinetoweek30)
VALOR-HCM
The efficacy of CAMZYOS was evaluated in VALOR-HCM (NCT-04349072), a phase 3, double-blind, randomized, 16-week, placebo-controlled trial in 112 patients (mean age of 60 years; 51% men; 93% ≥NYHA class III) randomized 1:1 to receive treatment with CAMZYOS or placebo. At baseline, all patients had symptomatic obstructive HCM and were SRT eligible.
Patients with severely symptomatic drug-refractory obstructive HCM (including 33% on any combination of beta-blocker, calcium channel blocker and/or disopyramide; 20% were on disopyramide alone or in combination with other treatment), and NYHA class III/IV or class II with exertional syncope or near syncope, were included in the study. Patients were required to have LVOT peak gradient ≥50 mmHg at rest or with provocation, and LVEF ≥60%. Patients must have been referred or under active consideration within the past 12 months for SRT and actively considering scheduling the procedure.
Patients received CAMZYOS (2.5 mg, 5 mg, 10 mg, or 15 mg) or a placebo capsule once daily for 16 weeks. Dose adjustment was based on clinical echocardiogram parameters.
Primary endpoint
CAMZYOS was shown to be superior to placebo in reducing the proportion of patients who met the primary endpoint (the composite of patient decision to proceed with SRT prior to or at Week 16 or met SRT eligibility (LVOT gradient of ≥50 mmHg and NYHA class III-IV, or class II with exertional syncope or near syncope) at Week 16 (18% vs. 77%, respectively, p<0.0001; see Table 5).
Table 5: Primary Endpoint at 16 Weeks| *NYHA Class III or IV, or Class II with exertion induced syncope or near syncope and dynamic LVOT gradient at rest or with provocation (i.e., Valsalva or exercise) ≥50 mmHg. |
| CAMZYOS n (%) n=56 | Placebo n (%) n=56 | Treatment difference (95% CI) | p-value |
Primary efficacy composite endpoint | 10 (18) | 43 (77) | 59%
(44%, 74%) | <0.0001 |
Patient decision to proceed with SRT | 2 (3.6) | 2 (3.6) | | |
SRT-eligible based on guideline
criteria* | 8 (14) | 39 (70) | | |
SRT status not evaluable (imputed as
meeting guideline criteria) | 0 | 2 (3.6) | | |
Secondary endpoints
The treatment effects of CAMZYOS on LVOT obstruction, functional capacity, and health status were assessed by change from baseline through Week 16 in post-exercise LVOT gradient, proportion of patients with improvement in NYHA class, and KCCQ-23 CSS.
Table 6: Change from Baseline to Week 16 in Secondary Endpoints| †The KCCQ-23 CSS is derived from the Total Symptom Score (TSS) and the Physical Limitations (PL) score of the KCCQ-23. The CSS ranges from 0 to 100 with higher scores representing less severe symptoms and/or physical limitations. |
| CAMZYOS n=56 | Placebo n=56 | Difference (95% CI) | p-value |
Post-Exercise LVOT gradient (mmHg), mean (SD) | -39 (37) | -2 (29) | -38 (-49, -28) | <0.0001 |
Number (%) with NYHA Class improved ≥1 | 35 (63%) | 12 (21%) | 41% (25%, 58%) | <0.0001 |
KCCQ-23 CSS†, mean (SD) | 10 (16) | 2 (12) | 9 (5, 14) | <0.0001 |
| 10 (16) | 2 (14) | 10 (5, 15) | |
| 10 (19) | 2 (17) | 10 (5, 16) | |
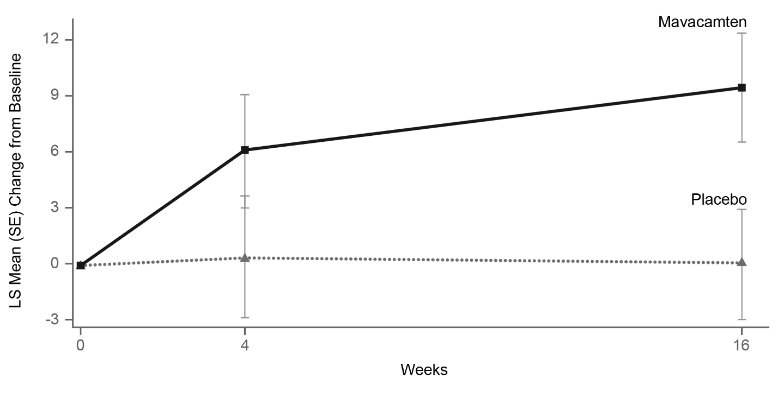
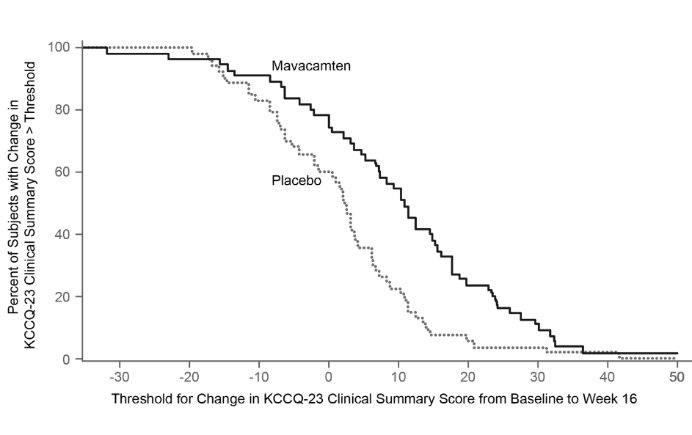
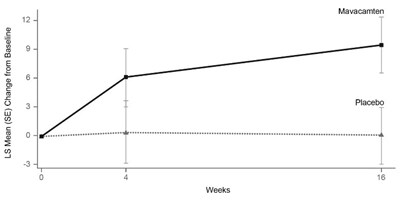
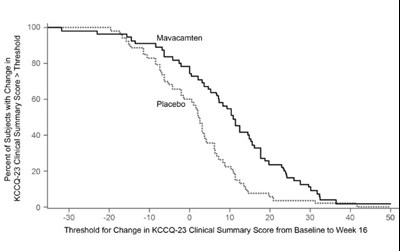
Figure 12 shows the time course for changes in KCCQ-23 CSS. Figure 13 shows the distribution of changes from baseline to Week 16 for KCCQ-23 CSS.
Figure 12: KCCQ-23 Clinical Summary Score: Mean Change from Baseline Over Time
Fig_valor-mean-change (Fig Valor Mean Change)
Figure 13: KCCQ-23 Clinical Summary Score: Cumulative Distribution of Change from Baseline to Week 16
Fig_valor-cumm-dist (Fig Valor Cumm Dist)
The figure displays the cumulative percentage of patients achieving a certain level of response.
Pediatric Patients
SCOUT-HCM
The efficacy of CAMZYOS was evaluated in SCOUT-HCM (NCT-06253221), a phase 3, double-blind, randomized, placebo-controlled, multicenter, international trial in 44 pediatric patients (23 mavacamten, 21 placebo), aged 12 years to <18 years who weighed ≥ 35 kg with symptomatic obstructive HCM, NYHA class II and III, LVEF ≥60%, and LVOT peak gradient ≥50 mmHg at rest or with provocation.
Background therapy (e.g., beta-blocker, calcium channel blocker, disopyramide, or combinations thereof) was allowed. Key exclusion criteria included phenocopy disease or multiple organ system malformation syndrome resulting in myocardial hypertrophy not related to sarcomere dysfunction and hypercontractility (e.g., Noonan syndrome, Pompe disease, Fabry disease, Friedreich ataxia, or Danon disease).
Patients were randomized 1:1 to receive either CAMZYOS (starting dose of 2.5 mg for body weight 35 to <45 kg, 5 mg for body weight ≥45 kg) or placebo once daily for 28 weeks. Randomization was stratified by age (12 ≤ to < 15 years, 15 ≤ to < 18 years) and beta-blocker use at baseline (yes/no).
Doses were individually titrated based on clinical echocardiogram parameters obtained at scheduled visits within protocol-defined windows in single dose increments (1 mg, 2.5 mg, 5 mg, 10 mg, or 15 mg) up to a maximum dose of 15 mg once daily. Down-titration occurred based on echocardiogram at approximately Weeks 4 and 8 if Valsalva LVOT gradient was <20 mmHg and LVEF was ≥50%. Up-titration occurred based on echocardiogram at approximately Weeks 11 and 23 if Valsalva LVOT gradient was ≥30 mmHg and LVEF was ≥55%. At Week 28, in the CAMZYOS group, 39% of patients were on the 15 mg dose, 30% were on the 10 mg dose, 17% were on the 5 mg dose, 9% were on the 2.5 mg dose, and 4% were on the 1 mg dose.
At baseline, mean age of the patients was 15 years with 50% aged 12 to < 15 years, 30% were females, 68% White, 7% Black, 5% Asian, and 20% unknown or not reported, 84% were NYHA class II, 16% were NYHA class III, 84% were on a beta-blocker, 11% were on a calcium channel blocker, 20% were on disopyramide, and 25% were on at least 2 HCM treatments. Baseline demographic characteristics were largely balanced between CAMZYOS and placebo arms.
Primary endpoint
The primary efficacy endpoint was change from baseline in Valsalva LVOT gradient at Week 28. A mean (SD) change in the Valsalva LVOT gradient at Week 28 of -49.4 (42.6) mmHg and -1.8 (37.8) mmHg was observed in the CAMZYOS versus placebo group, respectively, with a statistically significant least squares mean difference of -48.0 mmHg; 95% CI: -67.7, -28.3; p<0.0001 favoring CAMZYOS. The primary endpoint results favored CAMZYOS across all prespecified subgroup analyses including age, sex, and race.
CAMZYOS reduced resting and Valsalva LVOT gradient and improved functional capacity and symptoms in adult patients. Similarly, CAMZYOS reduced resting and Valsalva LVOT gradient in pediatric patients ≥ 35 kg. The pharmacokinetics of mavacamten in pediatric patients ≥ 30 kg are comparable to those in adult patients [see Clinical Pharmacology (12.3)]. Based on these data, CAMZYOS is expected to improve functional capacity and symptoms in pediatric patients with symptomatic obstructive HCM weighing ≥ 30 kg.