Other

Nalox-img-01.jpg (Nalox Img 01)
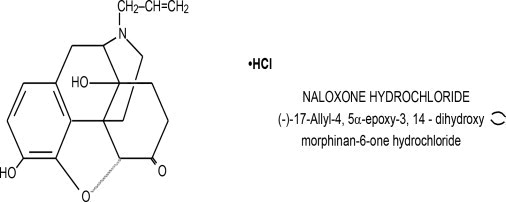
Naloxone Hydrochloride Injection, USP
Opioid Antagonist
Rx only
Opioid Overdose–Known or Suspected:
An initial dose of 0.4 mg to 2 mg of Naloxone may be administered intravenously. If the desired degree of counteraction and improvement in respiratory functions are not obtained, it may be repeated at two- to three-minute intervals. If no response is observed after 10 mg of Naloxone have been administered, the diagnosis of opioid-induced or partial opioid-induced toxicity should be questioned. Intramuscular or subcutaneous administration may be necessary if the intravenous route is not available.
Postoperative Opioid Depression:
For the partial reversal of opioid depression following the use of opioids during surgery, smaller doses of Naloxone are usually sufficient. The dose of Naloxone should be titrated according to the patient's response. For the initial reversal of respiratory depression, Naloxone should be injected in increments of 0.1 to 0.2 mg intravenously at two- to three-minute intervals to the desired degree of reversal, i.e., adequate ventilation and alertness without significant pain or discomfort. Larger than necessary dosage of Naloxone may result in significant reversal of analgesia and increase in blood pressure. Similarly, too rapid reversal may induce nausea, vomiting, sweating or circulatory stress.
Repeat doses of Naloxone may be required within one- to two-hour intervals depending upon the amount, type (i.e., short or long acting) and time interval since last administration of an opioid. Supplemental intramuscular doses have been shown to produce a longer lasting effect.
Septic Shock:
The optimal dosage of Naloxone or duration of therapy for the treatment of hypotension in septic shock patients has not been established (see CLINICAL PHARMACOLOGY).