Table 16 summarizes the laboratory abnormalities in patients who received Kyprolis with subcutaneous daratumumab and dexamethasone in PLEIADES.
The safety of Kyprolis in combination with isatuximab and dexamethasone was evaluated in IKEMA, a randomized, open-label clinical trial in patients with previously treated multiple myeloma [see Clinical Studies (14.4)]. Patients received Kyprolis 20/56 mg/m2 twice weekly in combination with isatuximab and dexamethasone (Isa-Kd) (n=177) or Kyprolis and dexamethasone (Kd) (n=122). Among patients receiving Isa-Kd, the median exposure to Kyprolis was 65 weeks.
Serious adverse reactions occurred in 59% of patients receiving Isa-Kd. The most frequent serious adverse reactions in >5% of patients who received Isa-Kd were pneumonia (25%) and upper respiratory tract infections (9%). Adverse reactions with a fatal outcome during treatment were reported in 3.4% of patients in the Isa-Kd group (those occurring in more than 1% of patients were pneumonia occurring in 1.7% and cardiac failure in 1.1% of patients).
Permanent treatment discontinuation due to an adverse reaction (grades 1-4) occurred in 8% of patients who received Isa-Kd. The most frequent adverse reactions requiring permanent discontinuation in patients who received Isa-Kd were infections (2.8%).
Dosage interruptions due to an adverse reaction occurred in 4% of patients who received Kyprolis in the Isa-Kd group. The most frequent adverse reactions requiring dosage interruption in patients who received Kyprolis in the Isa-Kd group were administration site extravasation (1.1%) and infusion site extravasation (1.1%).
Dose reductions or omissions of Kyprolis due to an adverse reaction in the Isa-Kd group occurred in 67% of patients. Adverse reactions which required dose reductions or omissions in >10% of patients who received Kyprolis in the Isa-Kd group were upper respiratory tract infection (12.4%) and hypertension (11.9%).
The most common adverse reactions (≥20%) were upper respiratory tract infection, infusion-related reactions, fatigue, hypertension, diarrhea, pneumonia, dyspnea, insomnia, bronchitis, cough and back pain.
Table 17 summarizes the adverse reactions in IKEMA.
Table 18 summarizes the laboratory abnormalities in patients who received Kyprolis with isatuximab and dexamethasone versus Kyprolis with dexamethasone in IKEMA.
Deaths due to adverse reactions within 30 days of the last dose of Kyprolis occurred in 30/598 (5%) patients receiving Kyprolis monotherapy. These adverse reactions were related to cardiac disorders in 10 (2%) patients, infections in 8 (1%) patients, renal disorders in 4 (< 1%) patients, and other adverse reactions in 8 (1%) patients.
Serious adverse reactions were reported in 50% of patients in the pooled Kyprolis monotherapy studies (N = 598). The most frequent serious adverse reactions were: pneumonia (8%), acute renal failure (5%), disease progression (4%), pyrexia (3%), hypercalcemia (3%), congestive heart failure (3%), multiple myeloma (3%), anemia (2%), and dyspnea (2%).
Adverse reactions occurring with Kyprolis monotherapy are presented in Table 19.
- Blood and lymphatic system disorders: febrile neutropenia, leukopenia, neutropenia
- Cardiac disorders: cardiac arrest, cardiac failure, cardiac failure congestive, myocardial infarction, myocardial ischemia
- Ear and labyrinth disorders: tinnitus
- Eye disorders: cataract, blurred vision
- Gastrointestinal disorders: abdominal pain, abdominal pain upper, constipation, dyspepsia, gastrointestinal hemorrhage, toothache
- General disorders and administration site conditions: asthenia, infusion site reaction, multi-organ failure, pain
- Hepatobiliary disorders: hepatic failure
- Infections: bronchitis, bronchopneumonia, influenza, lung infection, pneumonia, nasopharyngitis, respiratory tract infection, rhinitis, sepsis, urinary tract infection
- Metabolism and nutrition disorders: hypercalcemia, hyperglycemia, hyperkalemia, hyperuricemia, hypoalbuminemia, hypocalcemia, hypokalemia, hypomagnesemia, hyponatremia, hypophosphatemia, tumor lysis syndrome
- Musculoskeletal and connective tissue disorders: arthralgia, musculoskeletal pain, musculoskeletal chest pain, myalgia, pain in extremity
- Nervous system disorders: hypoesthesia, intracranial hemorrhage, paresthesia, peripheral motor neuropathy, peripheral neuropathy, peripheral sensory neuropathy
- Psychiatric disorders: anxiety
- Renal and urinary disorders: acute renal failure, renal failure, renal impairment
- Respiratory, thoracic and mediastinal disorders: dysphonia, epistaxis, oropharyngeal pain, pulmonary edema, pulmonary hemorrhage
- Skin and subcutaneous tissue disorders: erythema, hyperhidrosis, pruritus, rash
- Vascular disorders: embolic and thrombotic events, venous (including deep vein thrombosis and pulmonary embolism), hemorrhage, hypotension
Grade 3 and higher adverse reactions occurring at an incidence of > 1% include febrile neutropenia, cardiac arrest, cardiac failure congestive, pain, sepsis, urinary tract infection, hyperglycemia, hyperkalemia, hyperuricemia, hypoalbuminemia, hypocalcemia, hyponatremia, hypophosphatemia, renal failure, renal failure acute, renal impairment, pulmonary edema, and hypotension.
Table 20 describes Grade 3–4 laboratory abnormalities reported at a rate of > 10% for patients who received Kyprolis monotherapy.
Table 20: Grade 3–4 Laboratory Abnormalities (> 10%) with Kyprolis Monotherapy| Laboratory Abnormality | Kyprolis
20/56 mg/m2
(N = 24) | Kyprolis
20/27 mg/m2
(N = 598) |
|---|
| Decreased lymphocytes | 15 (63) | 151 (25) |
| Decreased platelets | 11 (46) | 184 (31) |
| Decreased hemoglobin | 7 (29) | 132 (22) |
| Decreased total white blood cell count | 3 (13) | 71 (12) |
| Decreased sodium | 2 (8) | 69 (12) |
| Decreased absolute neutrophil count | 2 (8) | 67 (11) |
Risk Summary
Kyprolis can cause fetal harm based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1)]. There are no available data on Kyprolis use in pregnant women to evaluate for drug-associated risks. Kyprolis caused embryo-fetal lethality in rabbits at doses lower than the clinical dose (see Data). Advise pregnant women of the potential risk to the fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%–4% and 15%–20%, respectively.
Data
Animal Data
Carfilzomib administered intravenously to pregnant rats and rabbits during the period of organogenesis was not teratogenic at doses up to 2 mg/kg/day in rats and 0.8 mg/kg/day in rabbits. In rabbits, there was an increase in pre-implantation loss at ≥ 0.4 mg/kg/day and an increase in early resorptions and post-implantation loss and a decrease in fetal weight at the maternally toxic dose of 0.8 mg/kg/day. The doses of 0.4 and 0.8 mg/kg/day in rabbits are approximately 20% and 40%, respectively, of the recommended dose in humans of 27 mg/m2 based on BSA.
Risk Summary
There are no data on the presence of Kyprolis in human milk, the effects on the breastfed child, or the effects of the drug on milk production. Because of the potential for serious adverse reactions in the breastfed child, advise women not to breastfeed during treatment with Kyprolis and for 2 weeks after treatment.
Pregnancy Testing
Conduct pregnancy testing on females of reproductive potential prior to initiating Kyprolis treatment.
Contraception
Females
Advise females of reproductive potential to use effective contraception during treatment with Kyprolis and for 6 months following the last dose.
Males
Advise males with female sexual partners of reproductive potential to use effective contraception during treatment with Kyprolis and for 3 months following the last dose.
Infertility
Based on the mechanism of action, Kyprolis may have an effect on either male or female fertility [see Clinical Pharmacology (12.1), Nonclinical Toxicology (13.1)]. There are no data on the effect of Kyprolis on human fertility.
Distribution
The mean steady-state volume of distribution of a 20 mg/m2 dose of carfilzomib was 28 L. Carfilzomib is 97% bound to human plasma proteins over the concentration range of 0.4 to 4 micromolar in vitro.
Elimination
Carfilzomib has a half-life of ≤ 1 hour on Day 1 of Cycle 1 following intravenous doses ≥ 15 mg/m2. The half-life was similar when administered either as a 30-minute infusion or a 2- to 10-minute infusion. The systemic clearance ranged from 151 to 263 L/hour.
Metabolism
Carfilzomib is rapidly metabolized. Peptidase cleavage and epoxide hydrolysis were the principal pathways of metabolism. Cytochrome P450 (CYP)-mediated mechanisms contribute a minor role in overall carfilzomib metabolism.
Excretion
Approximately 25% of the administered dose of carfilzomib was excreted in urine as metabolites in 24 hours. Urinary and fecal excretion of the parent compound was negligible (0.3% of total dose).
Specific Populations
Age (35-89 years), sex, race or ethnicity (80% White, 11% Black, 6% Asians, 3% Hispanics), and mild to severe renal impairment (creatinine clearance 15-89 mL/min) did not have clinically meaningful effects on the pharmacokinetics of carfilzomib.
Patients with Hepatic Impairment
Compared to patients with normal hepatic function, patients with mild (total bilirubin 1 to 1.5 × ULN and any AST or total bilirubin ≤ ULN and AST > ULN) and moderate (total bilirubin > 1.5 to 3 × ULN and any AST) hepatic impairment had approximately 50% higher carfilzomib AUC. The pharmacokinetics of carfilzomib has not been evaluated in patients with severe hepatic impairment (total bilirubin > 3 × ULN and any AST).
Patients with Renal Impairment
Relative to patients with normal renal function, ESRD patients on hemodialysis showed 33% higher carfilzomib AUC. Since hemodialysis clearance of Kyprolis concentrations has not been studied, the drug should be administered after the hemodialysis procedure.
Drug Interaction Studies
Clinical Studies
Effect of Carfilzomib on Sensitive CYP3A Substrate: Midazolam (a sensitive CYP3A substrate) pharmacokinetics was not affected by concomitant administration of carfilzomib.
In Vitro Studies
Effect of Carfilzomib on Cytochrome P450 (CYP) Enzymes: Carfilzomib showed direct and time-dependent inhibition of CYP3A but did not induce CYP1A2 and CYP3A4 in vitro.
Effect of Transporters on Carfilzomib: Carfilzomib is a P-glycoprotein (P-gp) substrate in vitro.
Effect of Carfilzomib on Transporters: Carfilzomib inhibits P-gp in vitro. However, given that Kyprolis is administered intravenously and is extensively metabolized, the pharmacokinetics of Kyprolis is unlikely to be affected by P-gp inhibitors or inducers.
Cardiovascular Toxicity
Monkeys administered a single bolus intravenous dose of carfilzomib at 3 mg/kg (approximately 1.3 times recommended dose in humans of 27 mg/m2 based on BSA) experienced hypotension, increased heart rate, and increased serum levels of troponin-T.
Chronic Administration
Repeated bolus intravenous administration of carfilzomib at ≥ 2 mg/kg/dose in rats and 2 mg/kg/dose in monkeys using dosing schedules similar to those used clinically resulted in mortalities that were due to toxicities occurring in the cardiovascular (cardiac failure, cardiac fibrosis, pericardial fluid accumulation, cardiac hemorrhage/degeneration), gastrointestinal (necrosis/hemorrhage), renal (glomerulonephropathy, tubular necrosis, dysfunction), and pulmonary (hemorrhage/inflammation) systems. The dose of 2 mg/kg/dose in rats is approximately half the recommended dose in humans of 27 mg/m2 based on BSA. The dose of 2 mg/kg/dose in monkeys is approximately equivalent to the recommended dose in humans based on BSA.
ASPIRE (NCT01080391)
ASPIRE was a randomized, open-label, multicenter trial which evaluated the combination of Kyprolis with lenalidomide and dexamethasone (KRd) versus lenalidomide and dexamethasone alone (Rd) in patients with relapsed or refractory multiple myeloma who had received 1 to 3 lines of therapy (A line of therapy is a planned course of treatment [including sequential induction, transplantation, consolidation, and/or maintenance] without an interruption for lack of efficacy, such as for relapse or progressive disease). Patients who had the following were excluded from the trial: refractory to bortezomib in the most recent regimen, refractory to lenalidomide and dexamethasone in the most recent regimen, not responding to any prior regimen, creatinine clearance < 50 mL/min, ALT/AST > 3.5 × ULN and bilirubin > 2 × ULN, New York Heart Association Class III to IV congestive heart failure, or myocardial infarction within the last 4 months.
In the KRd arm, Kyprolis was evaluated at a starting dose of 20 mg/m2, which was increased to 27 mg/m2 on Cycle 1, Day 8 onward. Kyprolis was administered as a 10-minute infusion on Days 1, 2, 8, 9, 15, and 16 of each 28-day cycle for Cycle 1 through 12. Kyprolis was dosed on Days 1, 2, 15, and 16 of each 28-day cycle from Cycle 13 through 18. Dexamethasone 40 mg was administered orally or intravenously on Days 1, 8, 15 and 22 of each cycle. Lenalidomide was given 25 mg orally on Days 1 to 21 of each 28-day cycle. The Rd treatment arm had the same regimen for lenalidomide and dexamethasone as the KRd treatment arm. Kyprolis was administered for a maximum of 18 cycles unless discontinued early for disease progression or unacceptable toxicity. Lenalidomide and dexamethasone administration could continue until progression or unacceptable toxicity. Concurrent use of thromboprophylaxis and a proton pump inhibitor were required for both arms and antiviral prophylaxis was required for the KRd arm.
The 792 patients in ASPIRE were randomized 1:1 to the KRd or Rd arm. The demographics and baseline characteristics were well-balanced between the two arms (see Table 22). Only 53% of the patients had testing for genetic mutations; a high-risk genetic mutation was identified for 12% of patients in the KRd arm and in 13% in the Rd arm.
Table 22: Demographics and Baseline Characteristics in ASPIRE| Characteristics | KRd
(N = 396) | Rd
(N = 396) |
|---|
| ECOG = Eastern Cooperative Oncology Group; IgG = immunoglobulin G; ISS = International Staging System; KRd = Kyprolis, lenalidomide, and dexamethasone; Rd = lenalidomide and dexamethasone |
| Age, Median, Years (min, max) | 64 (38, 87) | 65 (31, 91) |
| Age ≥ 75 Years, n (%) | 43 (11) | 53 (13) |
| Males, n (%) | 215 (54) | 232 (59) |
| Race, n (%) |
| White | 377 (95) | 377 (95) |
| Black | 12 (3) | 11 (3) |
| Other or Not Reported | 7 (2) | 8 (2) |
| Number of Prior Regimens, n (%) |
| 1 | 184 (46) | 157 (40) |
| 2 | 120 (30) | 139 (35) |
| 3 Including 2 patients with 4 prior regimens. | 92 (23) | 100 (25) |
| Prior Transplantation, n (%) | 217 (55) | 229 (58) |
| ECOG Performance Status, n (%) |
| 0 | 165 (42) | 175 (44) |
| 1 | 191 (48) | 186 (47) |
| 2 | 40 (10) | 35 (9) |
| ISS Stage at Study Baseline, n (%) |
| I | 167 (42) | 154 (39) |
| II | 148 (37) | 153 (39) |
| III | 73 (18) | 82 (21) |
| Unknown | 8 (2) | 7 (2) |
| Creatinine Clearance mL/min, Median (min, max) | 79 (39, 212) | 79 (30, 208) |
| 30 to < 50, n (%) | 19 (5) | 32 (8) |
| 50 to < 80, n (%) | 185 (47) | 170 (43) |
| Refractory to Last Therapy, n (%) | 110 (28) | 119 (30) |
| Refractory at Any Time to, n (%): |
| Bortezomib | 60 (15) | 58 (15) |
| Lenalidomide | 29 (7) | 28 (7) |
| Bortezomib + immunomodulatory agent | 24 (6) | 27 (7) |
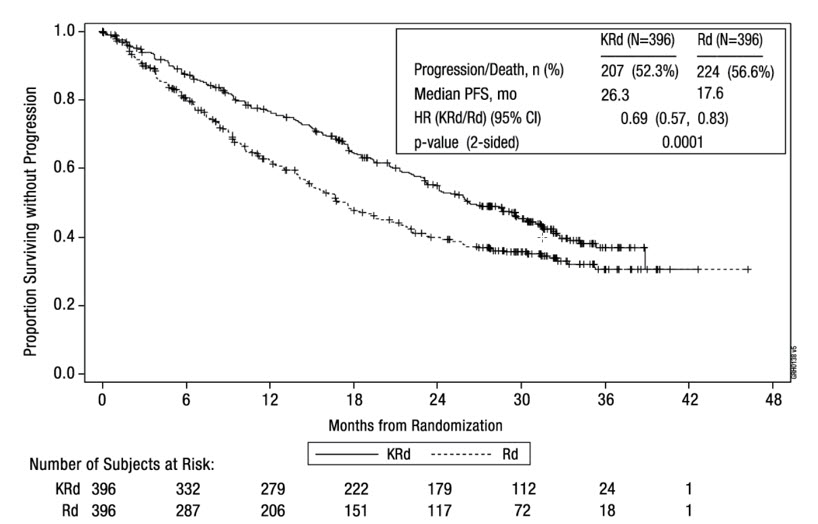
Patients in the KRd arm demonstrated improved PFS compared with those in the Rd arm (HR = 0.69, with 2-sided P-value = 0.0001) as determined using standard International Myeloma Working Group (IMWG)/European Blood and Marrow Transplantation (EBMT) response criteria by an Independent Review Committee (IRC). The median PFS was 26.3 months in the KRd arm versus 17.6 months in the Rd arm (see Table 23 and Figure 1).
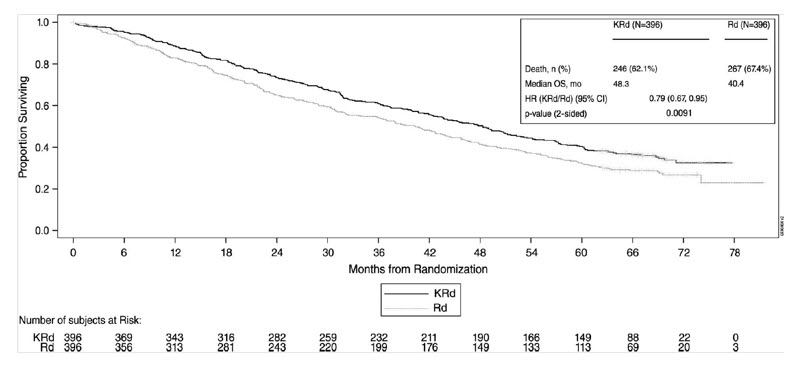
A pre-planned overall survival (OS) analysis was performed after 246 deaths in the KRd arm and 267 deaths in the Rd arm. The median follow-up was approximately 67 months. A statistically significant advantage in OS was observed in patients in the KRd arm compared to patients in the Rd arm (see Table 23 and Figure 2).
Table 23: Efficacy Outcomes in ASPIREEligible patients had 1-3 prior lines of therapy.
| Combination Therapy |
|---|
KRd
(N = 396) | Rd
(N = 396) |
|---|
| CI = confidence interval; CR = complete response; HR = hazard ratio; KRd = Kyprolis, lenalidomide, and dexamethasone; ORR = overall response rate; PFS = progression-free survival; PR = partial response; Rd = lenalidomide and dexamethasone; sCR = stringent CR; VGPR = very good partial response |
| PFS As determined by an Independent Review Committee. |
| Median Based on Kaplan-Meier estimates. , Months (95% CI) | 26.3 (23.3, 30.5) | 17.6 (15.0, 20.6) |
| HR (95% CI) Based on stratified Cox's model. | 0.69 (0.57, 0.83) |
| P-value (2-sided) The P-value was derived using stratified log-rank test. | 0.0001 |
| Overall Survival |
| Median, Months (95% CI) | 48.3 (42.4, 52.8) | 40.4 (33.6, 44.4) |
| HR (95% CI) | 0.79 (0.67, 0.95) |
| P-value (2-sided) | 0.0091 |
| Overall Response |
| N with response | 345 | 264 |
| ORR (%) (95% CI) Exact confidence interval. | 87 (83, 90) | 67 (62, 71) |
| P-value (2-sided) The P-value was derived using Cochran Mantel Haenszel test. | < 0.0001 |
| Response Category, n (%) |
| sCR | 56 (14) | 17 (4) |
| CR | 70 (18) | 20 (5) |
| VGPR | 151 (38) | 123 (31) |
| PR | 68 (17) | 104 (26) |
The median duration of response (DOR) was 28.6 months (95% CI: 24.9, 31.3) for the 345 patients achieving a response in the KRd arm and 21.2 months (95% CI: 16.7, 25.8) for the 264 patients achieving a response in the Rd arm. The median time to response was 1 month (range 1 to 14 months) in the KRd arm and 1 month (range 1 to 16 months) in the Rd arm.
CI = confidence interval; EBMT = European Blood and Marrow Transplantation; HR = hazard ratio; IMWG = International Myeloma Working Group; KRd = Kyprolis, lenalidomide, and dexamethasone; mo = months; PFS = progression-free survival; Rd = lenalidomide and dexamethasone arm
Note: The response and PD outcomes were determined using standard objective IMWG/EBMT response criteria. |
Figure 1: Kaplan-Meier Curve of Progression-Free Survival in ASPIRE |
|
| CI = confidence interval; HR = hazard ratio; KRd = Kyprolis, lenalidomide, and dexamethasone; mo = months; OS = overall survival; Rd = lenalidomide and dexamethasone arm |
Figure 2: Kaplan-Meier Curve of Overall Survival in ASPIRE |
|
ENDEAVOR (NCT01568866)
ENDEAVOR was a randomized, open-label, multicenter trial of Kyprolis and dexamethasone (Kd) versus bortezomib and dexamethasone (Vd) in patients with relapsed or refractory multiple myeloma who had received 1 to 3 lines of therapy. A total of 929 patients were enrolled and randomized (464 in the Kd arm; 465 in the Vd arm). Randomization was stratified by prior proteasome inhibitor therapy (yes versus no), prior lines of therapy (1 versus 2 or 3), current International Staging System stage (1 versus 2 or 3), and planned route of bortezomib administration. Patients were excluded if they had less than PR to all prior regimens; creatinine clearance < 15 mL/min; hepatic transaminases ≥ 3 × ULN; or left-ventricular ejection fraction < 40% or other significant cardiac conditions.
This trial evaluated Kyprolis at a starting dose of 20 mg/m2, which was increased to 56 mg/m2 on Cycle 1, Day 8 onward. Kyprolis was administered twice weekly as a 30-minute infusion on Days 1, 2, 8, 9, 15, and 16 of each 28-day cycle. Dexamethasone 20 mg was administered orally or intravenously on Days 1, 2, 8, 9, 15, 16, 22, and 23 of each cycle. In the Vd arm, bortezomib was dosed at 1.3 mg/m2 intravenously or subcutaneously on Days 1, 4, 8, and 11 of a 21-day cycle, and dexamethasone 20 mg was administered orally or intravenously on Days 1, 2, 4, 5, 8, 9, 11, and 12 of each cycle. Concurrent use of thromboprophylaxis was optional, and prophylaxis with an antiviral agent and proton pump inhibitor was required. Of the 465 patients in the Vd arm, 381 received bortezomib subcutaneously. Treatment continued until disease progression or unacceptable toxicity.
The demographics and baseline characteristics are summarized in Table 24.
Table 24: Demographics and Baseline Characteristics in ENDEAVOR| Characteristics | Kd
(N = 464) | Vd
(N = 465) |
|---|
| ECOG = Eastern Cooperative Oncology Group; FISH = Fluorescence in situ hybridization; ISS = International Staging System; Kd = Kyprolis and dexamethasone; Vd = bortezomib and dexamethasone |
| Age, Years |
| Median (min, max) | 65 (35, 89) | 65 (30, 88) |
| < 65, n (%) | 223 (48) | 210 (45) |
| 65 – 74, n (%) | 164 (35) | 189 (41) |
| ≥ 75, n (%) | 77 (17) | 66 (14) |
| Sex, n (%) |
| Female | 224 (48) | 236 (51) |
| Male | 240 (52) | 229 (49) |
| Race, n (%) |
| White | 353 (76) | 361 (78) |
| Black | 7 (2) | 9 (2) |
| Asian | 56 (12) | 57 (12) |
| Other or Not Reported | 48 (10) | 38 (8) |
| ECOG Performance Status, n (%) |
| 0 | 221 (48) | 232 (50) |
| 1 | 210 (45) | 203 (44) |
| 2 | 33 (7) | 30 (6) |
| Creatinine Clearance (mL/min) |
| Median (min, max) | 73 (14, 185) | 72 (12, 208) |
| < 30, n (%) | 28 (6) | 28 (6) |
| 30 – < 50, n (%) | 57 (12) | 71 (15) |
| 50 – < 80, n (%) | 186 (40) | 177 (38) |
| ≥ 80, n (%) | 193 (42) | 189 (41) |
| FISH, n (%) |
| High-risk | 97 (21) | 113 (24) |
| Standard-risk | 284 (61) | 291 (63) |
| Unknown-risk | 83 (18) | 61 (13) |
| ISS Stage at Study Baseline, n (%) |
| ISS I | 219 (47) | 212 (46) |
| ISS II | 138 (30) | 153 (33) |
| ISS III | 107 (23) | 100 (22) |
| Number of Prior Regimens, n (%) |
| 1 | 232 (50) | 231 (50) |
| 2 | 158 (34) | 144 (31) |
| 3 | 74 (16) | 88 (19) |
| 4 | 0 (0) | 2 (0.4) |
| Prior Therapies, n (%) | 464 (100) | 465 (100) |
| Bortezomib | 250 (54) | 252 (54) |
| Transplant for Multiple Myeloma | 266 (57) | 272 (59) |
| Thalidomide | 212 (46) | 249 (54) |
| Lenalidomide | 177 (38) | 178 (38) |
| Bortezomib + immunomodulatory agent | 159 (34) | 168 (36) |
| Refractory to last prior therapy, n (%) Refractory = disease not achieving a minimal response or better, progressing during therapy, or progressing within 60 days after completion of therapy. | 184 (40) | 189 (41) |
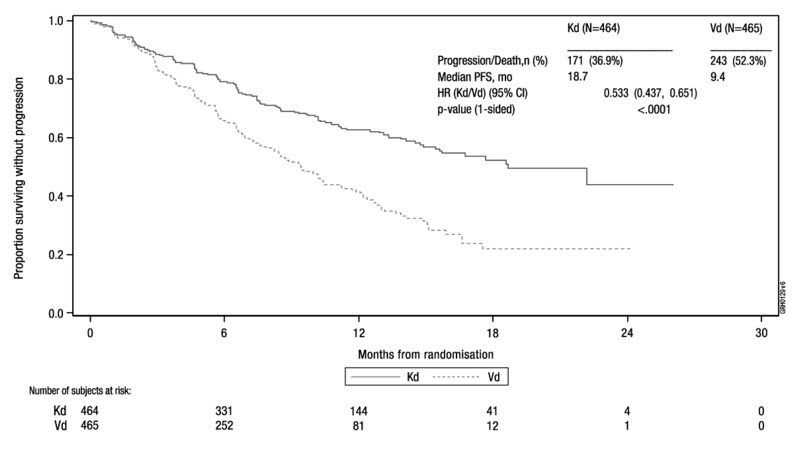
The efficacy of Kyprolis was evaluated by PFS as determined by an IRC using IMWG response criteria. The trial showed a median PFS of 18.7 months in the Kd arm versus 9.4 months in the Vd arm (see Table 25 and Figure 3).
Figure 3: Kaplan-Meier Plot of Progression-Free Survival in ENDEAVOR
| CI = confidence interval; HR = hazard ratio; Kd = Kyprolis and dexamethasone; mo = months; PFS = progression-free survival; Vd = bortezomib and dexamethasone |
|
Other endpoints included OS and overall response rate (ORR).
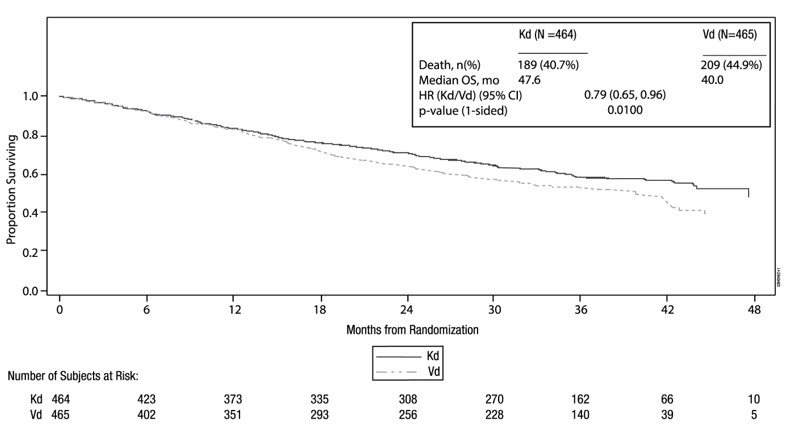
A pre-planned OS analysis was performed after 189 deaths in the Kd arm and 209 deaths in the Vd arm. The median follow-up was approximately 37 months. A significantly longer OS was observed in patients in the Kd arm compared to patients in the Vd arm (HR = 0.79; 95% CI: 0.65, 0.96; P-value = 0.01). Results are provided in Table 25 and Figure 4.
Table 25: Summary of Key Results in ENDEAVOR (Intent-to-Treat Population)Eligible patients had 1-3 prior lines of therapy.
| Kd
(N = 464) | Vd
(N = 465) |
|---|
| CI = confidence interval; CR = complete response; HR= hazard ratio; Kd = Kyprolis and dexamethasone; ORR = overall response rate; PFS = progression-free survival; PR = partial response; sCR = stringent CR; Vd = bortezomib and dexamethasone; VGPR = very good partial response; NE = non-estimable |
| PFS PFS and ORR were determined by an Independent Review Committee. |
| Number of events (%) | 171 (37) | 243 (52) |
| Median Based on Kaplan-Meier estimates. , Months (95% CI) | 18.7 (15.6, NE) | 9.4 (8.4, 10.4) |
| HR (Kd/Vd) (95% CI) Based on a stratified Cox's model. | 0.53 (0.44, 0.65) |
| P-value (1-sided) P-value was derived using a stratified log-rank test. | < 0.0001 |
| Overall Survival |
| Number of deaths (%) | 189 (41) | 209 (45) |
| Median, Months (95% CI) | 47.6 (42.5, NE) | 40.0 (32.6, 42.3) |
| HR (Kd/Vd) (95% CI) | 0.79 (0.65, 0.96) |
| P-value (1-sided) | 0.01 |
| Overall Response |
| N with Response | 357 | 291 |
| ORR (%) (95% CI) Exact confidence interval. | 77 (73, 81) | 63 (58, 67) |
| P-value (1-sided) The P-value was derived using Cochran Mantel Haenszel test. | < 0.0001 |
| Response Category, n (%) |
| sCR | 8 (2) | 9 (2) |
| CR | 50 (11) | 20 (4) |
| VGPR | 194 (42) | 104 (22) |
| PR Includes one patient in each arm with a confirmed PR which may not have been the best response. | 105 (23) | 158 (34) |
| CI = confidence interval; HR = hazard ratio; Kd = Kyprolis and dexamethasone; mo = month; OS = overall survival; Vd = bortezomib and dexamethasone |
Figure 4: Kaplan-Meier Plot of Overall Survival in ENDEAVOR |
|
The median DOR in subjects achieving PR or better was 21.3 months (95% CI: 21.3, not estimable) in the Kd arm and 10.4 months (95% CI: 9.3, 13.8) in the Vd arm. The median time to response was 1 month (range < 1 to 8 months) in both arms.
A.R.R.O.W. (NCT02412878)
A.R.R.O.W. was a randomized, open-label, multicenter superiority trial of Kyprolis and dexamethasone (Kd) once weekly (20/70 mg/m2) versus Kd twice weekly (20/27 mg/m2) in patients with relapsed and refractory multiple myeloma who had received 2 to 3 prior lines of therapy. Patients were excluded if they had less than PR to at least one prior line; creatinine clearance < 30 mL/min; hepatic transaminases ≥ 3 × ULN; or left-ventricular ejection fraction < 40% or other significant cardiac conditions. A total of 478 patients were enrolled and randomized (240 in 20/70 mg/m2 arm; 238 in 20/27 mg/m2 arm). Randomization was stratified by current International Staging System stage (stage 1 versus stages 2 or 3), refractory to bortezomib treatment (yes versus no), and age (< 65 versus ≥ 65 years).
Arm 1 of this trial evaluated Kyprolis at a starting dose of 20 mg/m2, which was increased to 70 mg/m2 on Cycle 1, Day 8 onward. Arm 1 Kyprolis was administered once weekly as a 30-minute infusion on Days 1, 8 and 15, of each 28-day cycle. Arm 2 of this trial evaluated Kyprolis at a starting dose of 20 mg/m2, which was increased to 27 mg/m2 on Cycle 1, Day 8 onward. Arm 2 Kyprolis was administered twice weekly as a 10-minute infusion on Days 1, 2, 8, 9, 15, and 16 of each 28-day cycle. In both regimens, dexamethasone 40 mg was administered orally or intravenously on Days 1, 8, 15 for all cycles and on Day 22 for cycles 1 to 9 only. Concurrent use of thromboprophylaxis was optional, prophylaxis with an antiviral agent was recommended, and prophylaxis with a proton pump inhibitor was required. Treatment continued until disease progression or unacceptable toxicity.
The demographics and baseline characteristics are summarized in Table 26.
Table 26: Demographics and Baseline Characteristics in A.R.R.O.W.| Characteristics | Once weekly Kd
20/70 mg/m2
(N = 240) | Twice weekly Kd
20/27 mg/m2
(N = 238) |
|---|
| ECOG = Eastern Cooperative Oncology Group; FISH = Fluorescence in situ hybridization; ISS = International Staging System; Kd = Kyprolis and dexamethasone |
| Age, Years |
| Median (min, max) | 66 (39, 85) | 66 (35, 83) |
| < 65, n (%) | 104 (43) | 104 (44) |
| 65 – 74, n (%) | 90 (38) | 102 (43) |
| ≥ 75, n (%) | 46 (19) | 32 (13) |
| Sex, n (%) |
| Female | 108 (45) | 110 (46) |
| Male | 132 (55) | 128 (54) |
| Race, n (%) |
| White | 200 (83) | 202 (85) |
| Black | 3 (1) | 2 (1) |
| Asian | 30 (13) | 15 (6) |
| Other or Not Reported | 7 (3) | 19 (8) |
| ECOG Performance Status, n (%) |
| 0 | 118 (49) | 118 (50) |
| 1 | 121 (50) | 120 (50) |
| 2 | 1 (0.4) | 0 (0) |
| Creatinine Clearance (mL/min) |
| Median (min, max) | 70.80 (28, 212) | 73.20 (29, 181) |
| < 30, n (%) | 2 (1) | 1 (0.4) |
| 30 – < 50, n (%) | 48 (20) | 34 (14) |
| 50 – < 80, n (%) | 91 (38) | 111 (47) |
| ≥ 80, n (%) | 99 (41) | 91 (38) |
| FISH, n (%) |
| High-risk | 34 (14) | 47 (20) |
| Standard-risk | 47 (20) | 53 (22) |
| Unknown-risk | 159 (66) | 138 (58) |
| ISS Stage at Study Baseline, n (%) |
| ISS I | 94 (39) | 99 (42) |
| ISS II | 80 (33) | 81 (34) |
| ISS III | 63 (26) | 54 (23) |
| Number of Prior Regimens, n (%) |
| 2 | 116 (48) | 125 (53) |
| 3 | 124 (52) | 112 (47) |
| >3 | 0 (0) | 1 (0.4) |
| Prior Therapies, n (%) |
| Bortezomib | 236 (98) | 237 (100) |
| Transplantation | 146 (61) | 157 (66) |
| Thalidomide | 119 (50) | 119 (50) |
| Lenalidomide | 207 (86) | 194 (82) |
The efficacy of Kyprolis was evaluated by PFS using IMWG response criteria. Efficacy results are provided in Table 27 and Figure 5.
| CI = confidence interval; HR = hazard ratio; Kd = Kyprolis and dexamethasone; PFS = progression-free survival |
Figure 5: Kaplan-Meier Plot of Progression-Free Survival in A.R.R.O.W. |
|
Table 27: Summary of Key Results in A.R.R.O.W. (Intent-to-Treat Population) | Once weekly Kd
20/70 mg/m2
(N = 240) | Twice weekly Kd
20/27 mg/m2
(N = 238) |
|---|
| CI = confidence interval; CR = complete response; HR = hazard ratio; Kd = Kyprolis and dexamethasone; ORR = overall response rate; PFS = progression-free survival; PR = partial response; sCR = stringent complete response; VGPR = very good partial response |
| PFS |
| Number of events, n (%) | 126 (52.5) | 148 (62.2) |
| Median, Months (95% CI) | 11.2 (8.6, 13.0) | 7.6 (5.8, 9.2) |
| HR (95% CI) | 0.69 (0.54, 0.88) |
| P-value (1-sided) | 0.0014 |
| Overall Response Overall response is defined as achieving a best overall response of PR, VGPR, CR or sCR. |
| N with Response | 151 | 97 |
| ORR (%) (95% CI) | 62.9 (56.5, 69.0) | 40.8 (34.5, 47.3) |
| P-value (1-sided) | < 0.0001 |
| Response Category, n (%) |
| sCR | 4 (1.7) | 0 (0.0) |
| CR | 13 (5.4) | 4 (1.7) |
| VGPR | 65 (27.1) | 28 (11.8) |
| PR | 69 (28.8) | 65 (27.3) |
The median DOR in subjects achieving PR or better was 15 months (95% CI: 12.2, not estimable) in the Kd 20/70 mg/m2 arm and 13.8 months (95% CI: 9.5, not estimable) in the Kd 20/27 mg/m2 arm. The median time to response was 1.1 months in the Kd 20/70 mg/m2 arm and 1.9 months in the Kd 20/27 mg/m2 arm.
Kyprolis is not approved for twice weekly 20/27 mg/m2 administration in combination with dexamethasone alone.
CANDOR (NCT03158688)
CANDOR was a randomized, open-label, multicenter trial which evaluated the combination of Kyprolis 20/56 mg/m2 twice weekly with intravenous daratumumab and dexamethasone (DKd) versus Kyprolis 20/56 mg/m2 twice weekly and dexamethasone (Kd) in patients with relapsed or refractory multiple myeloma who had received 1 to 3 prior lines of therapy. Patients who had the following were excluded from the trial: known moderate or severe persistent asthma within the past 2 years, known chronic obstructive pulmonary disease (COPD) with a FEV1 < 50% of predicted normal, and active congestive heart failure. Randomization was stratified by the ISS (stage 1 or 2 vs stage 3) at screening, prior proteasome inhibitor exposure (yes vs no), number of prior lines of therapy (1 vs ≥ 2), or prior cluster differentiation antigen 38 (CD38) antibody therapy (yes vs no).
Kyprolis was administered intravenously over 30 minutes at a dose of 20 mg/m2 in Cycle 1 on Days 1 and 2; at a dose of 56 mg/m2 in Cycle 1 on Days 8, 9, 15 and 16; and on Days 1, 2, 8, 9, 15 and 16 of each 28-day cycle thereafter. Dexamethasone 20 mg was administered orally or intravenously on Days 1, 2, 8, 9, 15 and 16 and then 40 mg orally or intravenously on Day 22 of each 28-day cycle. In the DKd arm, daratumumab was administered intravenously at a dose of 8 mg/kg in Cycle 1 on Days 1 and 2. Thereafter, daratumumab was administered intravenously at a dose of 16 mg/kg on Days 8, 15 and 22 of Cycle 1; Days 1, 8 and 15 and 22 of Cycle 2; Days 1 and 15 of Cycles 3 to 6; and Day 1 for the remaining cycles or until disease progression. For patients >75 years on a reduced dexamethasone dose of 20 mg, the entire 20 mg dose was given as a daratumumab pre-infusion medication on days when daratumumab was administered. Dosing of dexamethasone was otherwise split across days when Kyprolis was administered in both study arms. Treatment was continued in both arms until disease progression or unacceptable toxicity.
A total of 466 patients were randomized; 312 to the DKd arm and 154 to the Kd arm. The demographics and baseline characteristics are summarized in Table 28.
Table 28: Demographics and Baseline Characteristics in CANDOR| Characteristics | DKd
(N = 312) | Kd
(N = 154) |
|---|
| DKd = Kyprolis, daratumumab, and dexamethasone; ECOG = Eastern Cooperative Oncology Group; FISH = Fluorescence in situ hybridization; ISS = International Staging System; Kd = Kyprolis and dexamethasone |
| Age at randomization (years) |
| Median (min, max) | 64 (29, 84) | 65 (35, 83) |
| Age group – n (%) |
| 18 – 64 years | 163 (52) | 77 (50) |
| 65 – 74 years | 121 (39) | 55 (36) |
| 75 years and older | 28 (9) | 22 (14) |
| Sex – n (%) |
| Male | 177 (57) | 91 (59) |
| Female | 135 (43) | 63 (41) |
| Race – n (%) |
| Asian | 46 (15) | 20 (13) |
| Black or African American | 7 (2.2) | 2 (1.3) |
| White | 243 (78) | 123 (80) |
| Other | 16 (5) | 9 (6) |
| Geographic region – n (%) |
| North America | 21 (7) | 12 (8) |
| Europe | 207 (66) | 103 (67) |
| Asia Pacific | 84 (27) | 39 (25) |
| ECOG performance status – n (%) |
| 0 or 1 | 295 (95) | 147 (95) |
| 2 | 15 (4.8) | 7 (4.5) |
| Missing | 2 (0.6) | 0 (0.0) |
| Risk group as determined by FISH – n (%) |
| High risk | 48 (15) | 26 (17) |
| Standard risk | 104 (33) | 52 (34) |
| Unknown | 160 (51) | 76 (49) |
| ISS stage per I × RS at screening – n (%) |
| I or II | 252 (81) | 127 (82) |
| III | 60 (19) | 27 (17) |
| Number of prior regimens – n (%) Subjects with number of prior regimens > 3 was 0 in the DKd arm and 1 in Kd arm. |
| 1 | 144 (46) | 70 (45) |
| 2 | 99 (32) | 46 (30) |
| 3 | 69 (22) | 37 (24) |
| Prior Therapies |
| Lenalidomide | 123 (39) | 74 (48) |
| Refractory to lenalidomide | 99 (32) | 55 (36) |
| Bortezomib | 287 (92) | 134 (87) |
| Prior CD38 antibody therapy – n (%) | 1 (0.3) | 0 (0.0) |
| Prior stem cell transplant (ASCT) – n (%) | 195 (62) | 75 (49) |
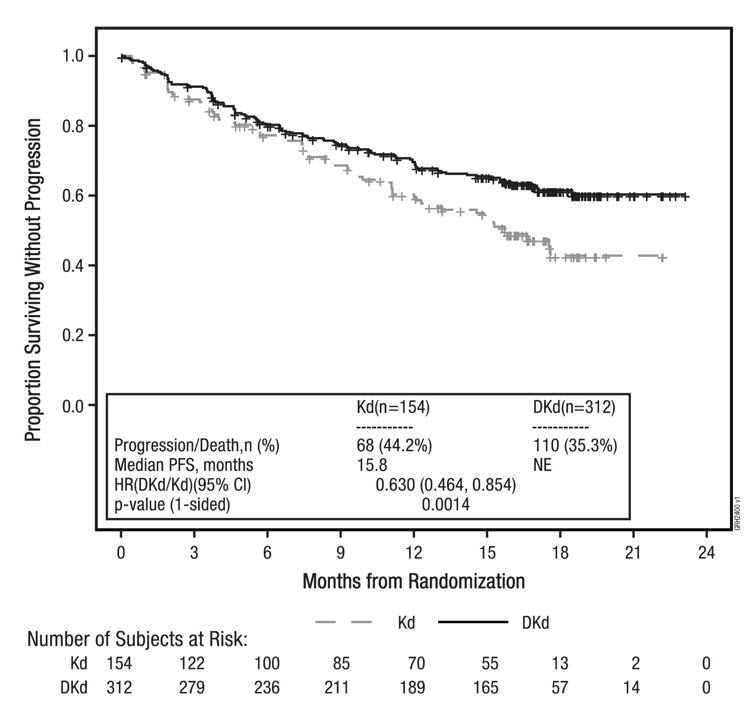
Efficacy was assessed by an IRC evaluation of PFS using the IMWG response criteria. Efficacy results are provided in Table 29 and Figure 6. The median duration of response has not been reached for the DKd arm and was 16.6 months (13.9, NE) for the Kd arm. The median (min, max) time to response was 1.0 (1, 14) months for the DKd arm and 1.0 (1, 10) months for the Kd arm.
| CI = confidence interval; DKd = Kyprolis, daratumumab and dexamethasone; HR = hazard ratio; Kd= Kyprolis and dexamethasone |
Figure 6: Kaplan-Meier Plot of Progression-Free Survival in CANDOR |
|
Table 29: Summary of Key Results in CANDOR (IntenttoTreat Population) | DKd
(N = 312) | Kd
(N = 154) |
|---|
| CI = confidence interval; CR = complete response; HR = hazard ratio; DKd = Kyprolis, daratumumab, and dexamethasone; Kd = Kyprolis and dexamethasone; ORR = overall response rate; PFS = progression-free survival; PR = partial response; MRD [-] CR = minimal residual disease negative-complete response; NE = non-estimable; VGPR = very good partial response |
| PFS |
| Number of events (%) | 110 (35%) | 68 (44%) |
| Median, Months (95% CI) | NE (NE, NE) | 15.8 (12.1, NE) |
| HR (95% CI) | 0.63 (0.46, 0.85) |
| P-value (1-sided) The P-value was derived using stratified log-rank test | 0.0014 |
| Overall Response |
| N with Response | 263 | 115 |
ORR (%)
(95% CI) | 84%
(80%, 88%) | 75%
(67%, 81%) |
| P-value (1-sided) The P-value was derived using stratified Cochran Mantel-Haenszel Chi-Squared test | 0.0040 |
| CR | 89 (28%) | 16 (10%) |
| VGPR | 127 (41%) | 59 (38%) |
| PR | 47 (15%) | 40 (26%) |
| MRD [-] CR rate at 12 months n (%) MRD [-] CR (at a 10-5 level) is defined as achievement of CR per IMWG-URC and MRD[-] status as assessed by the next-generation sequencing assay (ClonoSEQ) at the 12 months landmark (from 8 months to 13 months window) | 39 (12%) | 2 (1.3%) |
| (95% CI) | (9%, 17%) | (0.2%, 4.6%) |
| P-value (1-sided) | < 0.0001 |
| MRD [-] CR MRD[-]CR (at a 10-5 level) is defined as achievement of CR per IMWG-URC and MRD[-] status as assessed by the next-generation sequencing assay (ClonoSEQ) at any timepoint during the trial | 43 (14%) | 5 (3.2%) |
EQUULEUS (NCT01998971)
EQUULEUS was an open-label, multi-cohort trial which evaluated the combination of Kyprolis with intravenous daratumumab and dexamethasone in patients with relapsed or refractory multiple myeloma who had received 1 to 3 prior lines of therapy. Patients who had the following were excluded from the trial: known moderate or severe persistent asthma within the past 2 years, known chronic obstructive pulmonary disease (COPD) with a FEV1 < 50% of predicted normal, or active congestive heart failure (defined as New York Heart Association Class III-IV).
Kyprolis was administered intravenously over 30 minutes once weekly at a dose of 20 mg/m2 on Cycle 1 Day 1 and escalated to a dose of 70 mg/m2 on Cycle 1, Days 8 and 15; and on Days 1, 8, and 15 of each 28-day cycle. Ten patients were administered daratumumab at a dose of 16 mg/kg intravenously on Cycle 1, Day 1 and the remaining patients were administered daratumumab at a dose of 8 mg/kg intravenously on Cycle 1, Days 1 and 2. Thereafter, daratumumab was administered intravenously at a dose of 16 mg/kg on Days 8, 15 and 22 of Cycle 1; Days 1, 8, 15 and 22 of Cycle 2; Days 1 and 15 of Cycles 3 to 6; and then Day 1 for the remaining cycles of each 28-day cycle. In Cycles 1 and 2, dexamethasone 20 mg was administered orally or intravenously on Days 1, 2, 8, 9, 15, 16, 22 and 23; in cycles 3 to 6, dexamethasone 20 mg was administered orally or intravenously on Days 1, 2, 15 and 16 and at a dose of 40 mg on Day 8 and 22; and in cycles 7 and thereafter, dexamethasone 20 mg was administered orally or intravenously on Days 1 and 2 and at a dose of 40 mg on Days 8, 15, and 22. For patients > 75 years of age, dexamethasone 20 mg was administered orally or intravenously weekly after the first week. Treatment continued until disease progression or unacceptable toxicity.
The EQUULEUS trial enrolled 85 patients. The demographics and baseline characteristics are summarized in Table 30.
Table 30: Demographics and Baseline Characteristics in DKd 20/70 mg/m2 Regimen of EQUULEUS (Combination Therapy for Relapsed or Refractory Multiple Myeloma)| Characteristics | Number of Patients (%) |
|---|
| ECOG = Eastern Cooperative Oncology Group; FISH = Fluorescence in situ hybridization; PI = proteasome inhibitor; IMiD = immunomodulatory agent. |
| Age (years) |
| Median (min, max) | 66 (38, 85) |
| Age group – n (%) |
| < 65 years | 36 (42) |
| 65 - < 75 years | 41 (48) |
| ≥ 75 years | 8 (9) |
| Sex – n (%) |
| Male | 46 (54) |
| Female | 39 (46) |
| Race – n (%) |
| Asian | 3 (3.5) |
| Black or African American | 3 (3.5) |
| White | 68 (80) |
| ECOG Score, n (%) |
| 0 | 32 (38) |
| 1 | 46 (54) |
| 2 | 7 (8) |
| FISH, n (%) |
| N | 67 |
| Standard Risk | 54 (81) |
| High Risk | 13 (19) |
| Number of Prior regimens |
| 1 | 20 (23) |
| 2 | 40 (47) |
| 3 | 23 (27) |
| > 3 | 2 (2.4) |
| Prior Therapies |
| Bortezomib | 85 (100) |
| Lenalidomide | 81 (95) |
| Prior stem cell transplant (ASCT) | 62 (73) |
| Refractory to lenalidomide | 51 (60) |
| Refractory to both a PI and IMiD | 25 (29) |
Efficacy results were based on overall response rate using IMWG criteria. Efficacy results are provided in Table 31. The median time to response was 0.95 months (range: 0.9, 14.3). The median duration of response was 28 months (95% CI: 20.5, not estimable).
Table 31: Summary of Key Results in EQUULEUS (IntenttoTreat Population) | Study Patients
n (%) |
|---|
| CI = confidence interval; sCR = stringent complete response; CR = complete response; ORR = overall response rate; PR = partial response; VGPR = very good partial response |
| Overall Response |
| N with Response | 69 |
| ORR (%) (95% CI) | 81% (71, 89) |
| Response category, n (%) |
| sCR | 18 (21%) |
| CR | 12 (14%) |
| VGPR | 28 (33%) |
| PR | 11 (13%) |
PLEIADES (NCT03412565)
The efficacy of Kyprolis with daratumumab and hyaluronidase-fihj plus dexamethasone (DKd) was evaluated in a single-arm cohort of PLEIADES, a multi-cohort, open-label trial. This cohort enrolled patients with relapsed or refractory multiple myeloma excluding patients with left ventricular ejection fraction (LVEF) less than 40%, myocardial infarction within 6 months, uncontrolled cardiac arrhythmia, or uncontrolled hypertension (systolic blood pressure >159 mmHg or diastolic >99 mmHg despite optimal treatment). Patients received Kyprolis administered by IV infusion at a dose of 20 mg/m2 on Cycle 1 Day 1 and if a dose of 20 mg/m2 was tolerated Kyprolis was administered at a dose of 70 mg/m2 as a 30-minute IV infusion on Cycle 1 Day 8 and Day 15, and then Day 1, 8 and 15 of each cycle; daratumumab and hyaluronidase-fihj1,800 mg/30,000 units administered subcutaneously once weekly from Weeks 1 to 8, once every 2 weeks from Weeks 9 to 24 and once every 4 weeks starting with Week 25 until disease progression or unacceptable toxicity; and dexamethasone 40 mg per week (or a reduced dose of 20 mg per week for patients ≥75 years or BMI <18.5). The major efficacy outcome measure was ORR.
A total of 66 patients received the DKd regimen. The median age was 61 years (range: 42, 84); 52% were male; 73% were White and 3% Black or African American; and 68% had ISS Stage I, 18% had ISS Stage II, and 14% had ISS Stage III disease. A total of 79% of patients had a prior ASCT; 91% of patients received a prior PI. All patients received 1 prior line of therapy with exposure to lenalidomide and 62% of patients were refractory to lenalidomide.
Efficacy results are summarized in Table 32. At a median follow-up of 9.2 months, the median duration of response had not been reached and an estimated 85.2% (95% CI: 72.5, 92.3) maintained response for at least 6 months and 82.5% (95% CI: 68.9, 90.6) maintained response for at least 9 months.
Table 32: Efficacy Results from PLEIADES in Patients Who Received DKd | DKd
(N=66) |
|---|
| CI = confidence interval |
| Overall response rate (sCR+CR+VGPR+PR), n (%) Based on treated patients | 56 (84.8%) |
| 95% CI (%) | (73.9%, 92.5%) |
| Stringent complete response (sCR) | 11 (16.7%) |
| Complete response (CR) | 14 (21.2%) |
| Very good partial response (VGPR) | 26 (39.4%) |
| Partial response (PR) | 5 (7.6%) |
IKEMA (NCT03275285)
The efficacy and safety of Kyprolis in combination with isatuximab and dexamethasone were evaluated in IKEMA, a multicenter, multinational, randomized, open-label, 2-arm, phase 3 study in patients with relapsed and/or refractory multiple myeloma. Patients had received one to three prior lines of therapy. Patients were eligible for inclusion if they had an ECOG status of 0-2, platelets ≥50,000 cells/mm3, absolute neutrophil count ≥1 × 10⁹/L, creatinine clearance ≥15 mL/min/1.73 m2 (MDRD formula), AST ≤3 × ULN, and ALT ≤3 × ULN.
A total of 302 patients were randomized in a 3:2 ratio to receive either Kyprolis in combination with isatuximab and dexamethasone (Isa-Kd, 179 patients) or Kyprolis and dexamethasone (Kd, 123 patients). Treatment was administered in both groups in 28-day cycles until disease progression or unacceptable toxicity. Isatuximab 10 mg/kg was administered as an intravenous infusion weekly in the first cycle and every two weeks thereafter. Kyprolis was administered as an intravenous infusion at the dose of 20 mg/m2 on days 1 and 2; 56 mg/m2 on days 8, 9, 15, and 16 of cycle 1; and at the dose of 56 mg/m2 on days 1, 2, 8, 9, 15, and 16 for subsequent cycles of each 28-day cycle. Dexamethasone (intravenously on the days of isatuximab and/or Kyprolis infusions, and orally on the other days) 20 mg was given on days 1, 2, 8, 9, 15, 16, 22, and 23 for each 28-day cycle. On the days where both Kyprolis and isatuximab were administered, dexamethasone was administered first, followed by isatuximab infusion, then followed by Kyprolis infusion.
Overall, demographic and disease characteristics at baseline were similar between the two treatment groups. The median patient age was 64 years (range 33-90), 9% of patients were ≥ 75 years, 71% were White, 17% Asian, and 3% Black or African American. The proportion of patients with renal impairment (eGFR < 60 mL/min/1.73 m2) was 24% in the Isa-Kd group versus 15% in the Kd group. The International Staging System (ISS) stage at study entry was I in 53%, II in 31%, and III in 15% of patients. Overall, 24% of patients had high-risk chromosomal abnormalities at study entry; del(17p), t(4;14), t(14;16) were present in 11%, 14%, and 2% of patients, respectively. In addition, gain(1q21) was present in 42% of patients.
The median number of prior lines of therapy was 2 (range 1-4) with 44% of patients who received 1 prior line of therapy. Overall, 90% of patients received prior proteasome inhibitors, 78% received prior immunomodulators (including 43% who received prior lenalidomide), and 61% received prior stem cell transplantation. Overall, 33% of patients were refractory to prior proteasome inhibitors, 45% were refractory to prior immunomodulators (including 33% refractory to lenalidomide), and 21% were refractory to both a proteasome inhibitor and an immunomodulator.
The median duration of treatment was 80 weeks for the Isa-Kd group compared to 61 weeks for the Kd group.
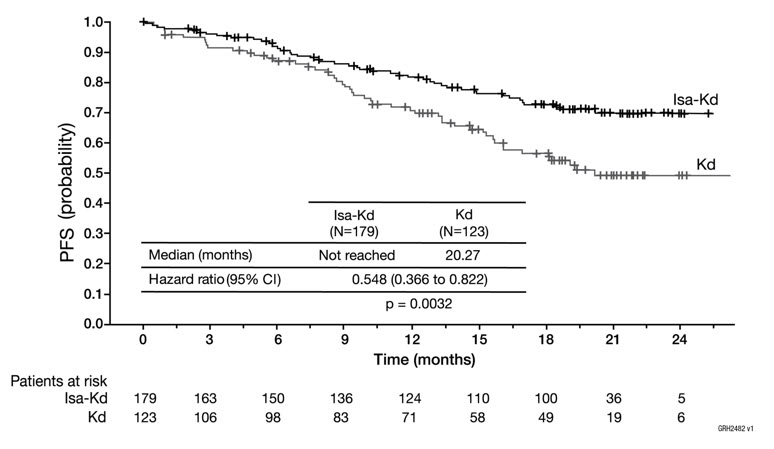
Efficacy was based upon PFS. PFS results were assessed by an Independent Response Committee based on central laboratory data for M-protein and central radiologic imaging review using the IMWG criteria. The improvement in PFS represented a 45% reduction in the risk of disease progression or death in patients treated with Isa-Kd compared to patients treated with Kd.
Efficacy results are presented in Table 33.
Table 33Results are based on a prespecified interim analysis.
Median follow-up time 20.7 months.
: Efficacy of Kyprolis in Combination with Isatuximab and Dexamethasone versus Kyprolis and Dexamethasone in the Treatment of Multiple Myeloma (IKEMA)| Endpoint | Isa-Kd
N=179 | Kd
N=123 |
|---|
| NR: not reached. |
| Progression-Free Survival PFS results were assessed by the IRC based on central laboratory data for M-protein and central radiologic imaging review using the IMWG criteria. A comparison is considered statistically significant if the p-value is <0.008 (efficacy boundary). |
Median (months)
[95% CI] | NR
[NR- NR] | 20.27
[15.77- NR] |
| Hazard ratio Stratified on number of previous lines of therapy (1 versus >1) and R-ISS (I or II versus III versus not classified) according to IRT. [95% CI] | 0.548 [0.366-0.822] |
| p-value (stratified log-rank test) | 0.0032 |
| Overall Response Rate sCR, CR, VGPR, and PR were evaluated by the IRC using the IMWG response criteria.
Responders (sCR+CR+VGPR+PR) n (%)
[95% CI]Estimated using Clopper-Pearson method. | 155 (86.6)
[80.7-91.2] | 102 (82.9)
[75.1-89.1] |
| p-value (stratified Cochran-Mantel-Haenszel) | 0.3859 |
| Complete Response (CR) n (%) | 71 (39.7) | 34 (27.6) |
| Very Good Partial Response (VGPR) n (%) | 59 (33) | 35 (28.5) |
| Partial Response (PR) n (%) | 25 (14) | 33 (26.8) |
Figure 7: Kaplan-Meier Plot of Progression-Free Survival in IKEMA |
|
Study PX-171-007 (NCT00531284)
Study PX-171-007 was a multicenter, open-label, dose escalation, single-arm trial that evaluated the safety of Kyprolis monotherapy as a 30-minute infusion in patients with relapsed or refractory multiple myeloma after 2 or more lines of therapy. Patients were excluded if they had a creatinine clearance < 20 mL/min; ALT ≥ 3 × upper limit of normal (ULN), bilirubin ≥ 1.5 × ULN; New York Heart Association Class III or IV congestive heart failure; or other significant cardiac conditions. A total of 24 subjects with multiple myeloma were enrolled at the maximum tolerated dose level of 20/56 mg/m2. Kyprolis was administered twice weekly for 3 consecutive weeks (Days 1, 2, 8, 9, 15, and 16) of a 28-day cycle. In Cycle 13 onward, the Day 8 and 9 Kyprolis doses could be omitted. Patients received Kyprolis at a starting dose of 20 mg/m2 on Days 1 and 2 of Cycle 1, which was increased to 56 mg/m2 for all subsequent doses. Dexamethasone 8 mg orally or intravenously was required prior to each Kyprolis dose in Cycle 1 and was optional in subsequent cycles. Treatment was continued until disease progression or unacceptable toxicity.
Efficacy was evaluated by ORR and DOR. ORR by investigator assessment was 50% (95% CI: 29, 71) per IMWG criteria (see Table 34). The median DOR in subjects who achieved a PR or better was 8.0 months (Range: 1.4, 32.5).
Table 34: Response Categories in Study PX-171-007 (20/56 mg/m2 Monotherapy Regimen)| Characteristics | Study Patients Eligible patients had 2 or more prior lines of therapy.
n (%) |
|---|
| CI = confidence interval; CR = complete response; PR = partial response; sCR = stringent complete response; VGPR = very good partial response |
| Number of Patients (%) | 24 (100) |
| Overall Response Per investigator assessment. | 12 (50) |
| 95% CI Exact confidence interval. | (29, 71) |
| Response Category |
| sCR | 1 (4) |
| CR | 0 (0) |
| VGPR | 4 (17) |
| PR | 7 (29) |
Study PX-171-003 A1 (NCT00511238)
Study PX-171-003 A1 was a single-arm, multicenter clinical trial of Kyprolis monotherapy by up to 10-minute infusion. Eligible patients were those with relapsed and refractory multiple myeloma who had received at least two prior therapies (including bortezomib and thalidomide and/or lenalidomide) and had ≤ 25% response to the most recent therapy or had disease progression during or within 60 days of the most recent therapy. Patients were excluded from the trial if they were refractory to all prior therapies or had a total bilirubin ≥ 2 × ULN; creatinine clearance < 30 mL/min; New York Heart Association Class III to IV congestive heart failure; symptomatic cardiac ischemia; myocardial infarction within the last 6 months; peripheral neuropathy Grade 3 or 4, or peripheral neuropathy Grade 2 with pain; active infections requiring treatment; or pleural effusion.
Kyprolis was administered intravenously up to 10 minutes on two consecutive days each week for three weeks, followed by a 12-day rest period (28-day treatment cycle), until disease progression, unacceptable toxicity, or for a maximum of 12 cycles. Patients received 20 mg/m2 at each dose in Cycle 1, and 27 mg/m2 in subsequent cycles. Dexamethasone 4 mg orally or intravenously was administered prior to Kyprolis doses in the first and second cycles.
A total of 266 patients were enrolled. Baseline patient and disease characteristics are summarized in Table 35.
Table 35: Demographics and Baseline Characteristics in Study PX-171-003 A1 (20/27 mg/m2 Monotherapy Regimen)| Characteristics | Number of Patients (%) |
|---|
| FISH = Fluorescence in situ hybridization; ISS = International Staging System |
| Patient Characteristics |
| Enrolled patients | 266 (100) |
| Median age, years (range) | 63 (37, 87) |
| Age group, < 65 / ≥ 65 (years) | 146 (55) / 120 (45) |
| Sex (male / female) | 155 (58) / 111 (42) |
| Race (White / Black / Asian / Other) | 190 (71) / 53 (20) / 6 (2) / 17 (6) |
| Disease Characteristics |
| Number of Prior Regimens (median) | 5 Range: 1, 20. |
| Prior Transplantation | 198 (74) |
| Refractory Status to Most Recent Therapy Categories for refractory status are derived by programmatic assessment using available laboratory data. |
| Refractory: Progression during most recent therapy | 198 (74) |
| Refractory: Progression within 60 days after completion of most recent therapy | 38 (14) |
| Refractory: ≤ 25% response to treatment | 16 (6) |
| Relapsed: Progression after 60 days post treatment | 14 (5) |
| Years since diagnosis, median (range) | 5.4 (0.5, 22.3) |
| Plasma cell involvement (< 50% / ≥ 50% / unknown) | 143 (54) / 106 (40) / 17 (6) |
| ISS Stage at Study Baseline |
| I | 76 (29) |
| II | 102 (38) |
| III | 81 (31) |
| Unknown | 7 (3) |
| Cytogenetics or FISH analyses |
| Normal/Favorable | 159 (60) |
| Poor Prognosis | 75 (28) |
| Unknown | 32 (12) |
| Creatinine clearance < 30 mL/min | 6 (2) |
Efficacy was evaluated by ORR as determined by IRC assessment using IMWG criteria. Efficacy results are provided in Table 36. The median DOR was 7.8 months (95% CI: 5.6, 9.2).
Table 36: Response Categories in Study PX-171-003 A1 (20/27 mg/m2 Monotherapy Regimen)| Characteristics | Study Patients Eligible patients had 2 or more prior lines of therapy and were refractory to the last regimen.
n (%) |
|---|
| CI = confidence interval; CR = complete response; PR = partial response; VGPR = very good partial response |
| Number of Patients (%) | 266 (100) |
| Overall Response As assessed by the Independent Review Committee. | 61 (23) |
| 95% CI Exact confidence interval. | (18, 28) |
| Response Category |
| CR | 1 (< 1) |
| VGPR | 13 (5) |
| PR | 47 (18) |
Study PX-171-004 Part 2 (NCT00530816)
Study PX-171-004 Part 2 was a single-arm, multicenter clinical trial of Kyprolis monotherapy by up to 10-minute infusion. Eligible patients were those with relapsed or refractory multiple myeloma who were bortezomib-naïve, had received one to three prior lines of therapy and had ≤ 25% response or progression during therapy or within 60 days after completion of therapy. Patients were excluded from the trial if they were refractory to standard first-line therapy or had a total bilirubin ≥ 2 × ULN; creatinine clearance < 30 mL/min; New York Heart Association Class III to IV congestive heart failure; symptomatic cardiac ischemia; myocardial infarction within the last 6 months; active infections requiring treatment; or pleural effusion.
Kyprolis was administered intravenously up to 10 minutes on two consecutive days each week for three weeks, followed by a 12-day rest period (28-day treatment cycle), until disease progression, unacceptable toxicity, or for a maximum of 12 cycles. Patients received 20 mg/m2 at each dose in Cycle 1, and 27 mg/m2 in subsequent cycles. Dexamethasone 4 mg orally or intravenously was administered prior to Kyprolis doses in the first and second cycles.
A total of 70 patients were treated with this 20/27 mg/m2 regimen. Baseline patient and disease characteristics are summarized in Table 37.
Table 37: Demographics and Baseline Characteristics in Study PX-171-004 Part 2 (20/27 mg/m2 Monotherapy Regimen)| Characteristics | Number of Patients (%) |
|---|
| FISH = Fluorescence in situ hybridization; ISS = International Staging System |
| Patient Characteristics |
| Enrolled patients | 70 (100) |
| Median age, years (range) | 66 (45, 85) |
| Age group, < 65 / ≥ 65 (years) | 31 (44) / 39 (56) |
| Sex (male / female) | 44 (63) / 26 (37) |
| Race (White / Black / Asian / Hispanic / Other) | 52 (74) / 12 (17) / 3 (4) / 2 (3) / 1 (1) |
| Disease Characteristics |
| Number of Prior Regimens (median) | 2 Range: 1, 4. |
| Prior Transplantation | 47 (67) |
| Refractory Status to Most Recent Therapy Categories for refractory status are derived by programmatic assessment using available laboratory data. |
| Refractory: Progression during most recent therapy | 28 (40) |
| Refractory: Progression within 60 days after completion of most recent therapy | 7 (10) |
| Refractory: ≤ 25% response to treatment | 10 (14) |
| Relapsed: Progression after 60 days post treatment | 23 (33) |
| No Signs of Progression | 2 (3) |
| Years since diagnosis, median (range) | 3.6 (0.7, 12.2) |
| Plasma cell involvement (< 50% / ≥ 50% / unknown) | 54 (77) / 14 (20) / 1 (1) |
| ISS Stage at Study Baseline, n (%) | |
| I | 28 (40) |
| II | 25 (36) |
| III | 16 (23) |
| Unknown | 1 (1) |
| Cytogenetics or FISH analyses | |
| Normal/Favorable | 57 (81) |
| Poor Prognosis | 10 (14) |
| Unknown | 3 (4) |
| Creatinine clearance < 30 mL/min | 1 (1) |
Efficacy was evaluated by ORR as determined by IRC assessment using IMWG criteria. Efficacy results are provided in Table 38. The median DOR was not reached.
Table 38: Response Categories in Study PX-171-004 Part 2 (20/27 mg/m2 Monotherapy Regimen)| Characteristics | Study Patients Eligible patients had 1-3 prior lines of therapy and were refractory to the last regimen.
n (%) |
|---|
| CI = confidence interval; CR = complete response; PR = partial response; VGPR = very good partial response |
| Number of Patients (%) | 70 (100) |
| Overall Response As assessed by an Independent Review Committee. | 35 (50) |
| 95% CI Exact confidence interval. | (38, 62) |
| Response Category |
| CR | 1 (1) |
| VGPR | 18 (26) |
| PR | 16 (23) |
How Supplied
Kyprolis (carfilzomib) for Injection is supplied as:
- An individually packaged single-dose vial containing 10 mg of carfilzomib as a white to off-white lyophilized cake or powder: NDC 76075-103-01, NDC 76075-103-21.
- An individually packaged single-dose vial containing 30 mg of carfilzomib as a white to off-white lyophilized cake or powder: NDC 76075-102-01, NDC 76075-102-21.
- An individually packaged single-dose vial containing 60 mg of carfilzomib as a white to off-white lyophilized cake or powder: NDC 76075-101-01, NDC 76075-101-21.
Cardiac Toxicities: Advise patients of the risks and symptoms of cardiac failure and ischemia [see Warnings and Precautions (5.1)].
Dehydration: Counsel patients to avoid dehydration, since patients receiving Kyprolis therapy may experience vomiting and/or diarrhea. Instruct patients to seek medical advice if they experience symptoms of dehydration [see Warnings and Precautions (5.3)].
Respiratory: Advise patients that they may experience cough or shortness of breath (dyspnea) during treatment with Kyprolis. This most commonly occurs within a day of dosing. Advise patients to contact their healthcare provider if they experience shortness of breath [see Warnings and Precautions (5.6)].
Venous Thrombosis: Inform patients of the risk of venous thromboembolism and discuss the options for prophylaxis. Advise patients to seek immediate medical attention for symptoms of venous thrombosis or embolism [see Warnings and Precautions (5.8)].
Infusion-Related Reactions: Advise patients of the risk of infusion-related reactions and discuss the common signs and symptoms of infusion-related reactions with the patients [see Warnings and Precautions (5.9)].
Bleeding: Inform patients that they may bruise or bleed more easily or that it may take longer to stop bleeding and to report to their healthcare provider any prolonged, unusual or excessive bleeding. Instruct patients on the signs of occult bleeding [see Warnings and Precautions (5.10)].
Hepatic: Inform patients of the risk of developing hepatic failure. Advise patients to contact their healthcare provider for symptoms of hepatitis including worsening fatigue or yellow discoloration of skin or eyes [see Warnings and Precautions (5.12)].
Other: Inform patients to contact their healthcare provider if they experience neurologic symptoms such as headaches, confusion, dizziness or loss of balance, difficulty talking or walking, decreased strength or weakness on one side of the body, seizures, or visual loss [see Warnings and Precautions (5) and Adverse Reactions (6)].
Driving/Operating Machines: Advise patients that Kyprolis may cause fatigue, dizziness, fainting, and/or drop in blood pressure. Advise patients not to drive or operate machinery if they experience any of these symptoms [see Adverse Reactions (6.1)].
Embryo-Fetal Toxicity: Advise females of the potential risk to the fetus. Advise females of reproductive potential to inform their healthcare provider immediately of a known or suspected pregnancy. Advise female patients to use effective contraceptive during treatment with Kyprolis and for 6 months following the last dose. Advise male patients with female sexual partners of reproductive potential to use effective contraception during treatment with Kyprolis and for 3 months following the last dose [see Warnings and Precautions (5.17), Use in Specific Populations (8.1, 8.3)].
Lactation: Advise patients to avoid breastfeeding while receiving Kyprolis and for 2 weeks after the last dose [see Use in Specific Populations (8.2)].
Concomitant Medications: Advise patients to discuss with their healthcare provider any medication they are currently taking prior to starting treatment with Kyprolis, or prior to starting any new medication(s) during treatment with Kyprolis.
AMGEN®
Kyprolis® (carfilzomib)
Manufactured for:
Onyx Pharmaceuticals, Inc.
One Amgen Center Drive
Thousand Oaks, CA 91320-1799 U.S.A.
Patent: http://pat.amgen.com/kyprolis
©2012-2025 Amgen Inc. All rights reserved.
1XXXXXX V29