Limitations of Use
Safety and efficacy of KYZATREX® in males less than 18 years old have not been established
[see
Use in Specific Populations (8.4)]
.
Safety and efficacy of KYZATREX® in men with “age-related hypogonadism” (also referred to as “late-onset hypogonadism”) have not been established.
Dosage Adjustment
Check serum testosterone concentrations 7 days after starting treatment or after dosage adjustment, 3 to 5 hours after the morning dose. Adjust the KYZATREX® dose as necessary as shown in Table 1. Thereafter, periodically monitor serum testosterone concentrations.
The minimum recommended dose is 100 mg once daily in the morning. The maximum recommended dose is 400 mg twice daily. For total daily doses greater than 100 mg, administer the same dose in the morning and evening.
Table 1: KYZATREX® Dosage Adjustment Scheme| Serum Testosterone Concentration | Current KYZATREX® Dosage | New KYZATREX® Dosage |
|---|
| Less than 460 ng/dL | 100 mg with breakfast only | 100 mg twice daily with meals |
| 100 mg twice daily with meals | 200 mg twice daily with meals |
| 200 mg twice daily with meals | 300 mg twice daily with meals |
| 300 mg twice daily with meals | 400 mg twice daily with meals |
| 460 to 971 ng/dL | No Dosage Change |
| More than 971 ng/dL | 400 mg twice daily with meals | 300 mg twice daily with meals |
| 300 mg twice daily with meals | 200 mg twice daily with meals |
| 200 mg twice daily with meals | 100 mg twice daily with meals |
| 100 mg twice daily with meals | 100 mg with breakfast only |
| 100 mg with breakfast only | Discontinue treatment |
Blood Pressure Increases
In Study MRS-TU-2019EXT, 24-hour ambulatory blood pressure monitoring (ABPM) was conducted in 155 male patients, 135 of whom completed the study. ABPM was conducted at 3 distinct 24-hour time periods: at baseline and following approximately 4 months and 6 months of treatment with KYZATREX®. A total of 151 patients had acceptable 24-hour ABPM recordings at both time periods. In that group, the mean change in systolic BP from Baseline to 4 months and 6 months was + 1.7 mm Hg (95% CI 0.3, 3.1) and 1.8 mm Hg (95% CI 0.3, 3.2), respectively. In that group, the mean change in diastolic BP from Baseline to 4 months and 6 months was 0.6 mm Hg (95% CI -0.3, 1.6) and 0.6 mm Hg (95% CI -0.4, 1.6), respectively. In patients with a history of hypertension on antihypertensive therapy at baseline, the mean ABPM systolic blood pressure increased from Baseline to 4 months and 6 months by 3.4 mm Hg (95% CI 1.0, 5.9) and 3.1 mm Hg (95% CI 0.6, 5.6), respectively (n=49).
In patients with no history of hypertension at baseline, the mean systolic blood pressure from Baseline increased by 0.7 mm Hg (95% CI -1.0, 2.4) at 4 months and 1.0 mm Hg (95% CI -0.7, 2.8), at six months respectively (n =90). Ambulatory (24-hour) blood pressure Changes from Baseline for study MRS- TU-2019EXT are presented in
Table 3 with 95% confidence intervals. No significant difference was observed between the 4-month and 6-month Changes from Baseline
Table 3: Blood Pressure Increases| Blood Pressure | Change from Baseline (95% CI) mm Hg |
|---|
| Systolic | Diastolic |
|---|
| 24-Hour Ambulatory |
| 4 Month | 1.7 (0.3 to 3.1) | 0.6 (-0.3 to 1.6) |
| 6 Month | 1.8 (0.3 to 3.2) | 0.6 (-0.4 to 1.6) |
|
A history of antihypertensive treatment and diabetes mellitus at baseline were significant factors related to ambulatory SBP increases.
Table 4 presents the Least Squares Mean estimates of Change from Baseline, with 95% CI’s, for sub-populations of subjects at study start either with or without hypertensive treatment or with or without diabetes mellitus.
A total of 5 of 155 patients (3.2%) on KYZATREX® in Study MRS-TU-2019EXT began taking new antihypertensive medications after study start. No patient had a dose increase in their antihypertensive medication by the end of treatment.
Of the 155 patients in Study MRS-TU-2019EXT who used KYZATREX®, 4 patients (2.6%) were reported to have an adverse reaction of hypertension.
Cardiovascular Outcomes
TRAVERSE was a randomized, double-blind, cardiovascular outcomes study to assess the cardiovascular (CV) safety of topical testosterone gel compared to placebo in 5198 hypogonadal men aged 45 to 80 years with a history of CV disease or with multiple CV risk factors. The primary outcome was the incidence of the composite endpoint of major adverse cardiovascular events (MACE), consisting of CV death, non-fatal myocardial infarction (MI), and non-fatal stroke.
The mean duration of therapy was approximately 22 months. The mean duration of follow-up was 33 months. Approximately 61% of all patients discontinued topical testosterone gel or placebo therapy.
The mean patient age (±SD) was 63.3 (7.9) years, with 2452 patients ages 65 years or more (47%); 2847 (about 55%) patients had pre-existing cardiovascular disease, whereas 2357 patients (about 45%) had an elevated cardiovascular risk at baseline, and mean BMI was 35kg/m
2. Approximately 80% of patients were White, 17% were Black, and 3% were of other races or ethnic groups. Approximately 69%, 84%, and 93% had diabetes mellitus, hyperlipidemia, and hypertension, respectively.
The mean serum testosterone concentration at baseline in patients receiving topical testosterone gel was 220.4 ng/dL (n=2596). The mean serum testosterone concentrations at 12 months, 24 months, 36 months, and 48 months in patients receiving topical testosterone gel were 440.5 ng/dL (n=1683), 420.9 ng/dl (n=1125), 428.7 ng/dL (n=731), and 365.2 ng/dL (n=220), respectively.
For patients treated with topical testosterone gel, the incidence of MACE was 7.0% (n=182 events) and for those receiving placebo, the incidence of MACE was 7.3% (n=190 events). The study demonstrated non-inferiority of topical testosterone gel versus placebo because the upper bound of 95% CI was less than the pre-specified risk margin, of 1.5 for MACE (Hazard Ratio 0.96 [95% CI: 0.78, 1.17]).
Additional Adverse Reproted in TRAVERSE
Additional adverse reactions reported in TRAVERSE at an incidence rate >2% in either treatment group and greater in topical testosterone gel versus placebo included: nonfatal arrythmias warranting intervention (5.2% vs 3.3%), atrial fibrillation (3.5% vs 2.4%), acute kidney injury (2.3% vs 1.5%) and bone fracture (3.5% vs 2.5%). For the adverse reaction of bone fracture, each event was adjudicated by clinical review
Heart Rate Increases
KYZATREX® increased mean (95%CI) 24-hour ambulatory heart rate by an average of 0.7 (-0.5 to 1.9) beats per minute (bpm) at 4 months and 1.9 (0.6 to 3.1) bpm at 6 months in Study MRS-TU-2019EXT. Changes in heart rate were similar between patients with or without hypertension or diabetes. Changes in heart rate with treatment were most prominent in the evening, 12 to 17 hours after the morning dose.
Increases in Hemoglobin
Increases in hemoglobin were reported in 7 out of 155 patients (4.5%) in Study MRS-TU2019EXT. None of these increases led to premature discontinuation of KYZATREX®.
Hematocrit was not assessed in this study.
Headaches
Headaches were reported in 3 of 155 patients (1.9%) receiving KYZATREX® in Study MRSTU-2019EXT.
Increases in Serum PSA
Four out of 155 patients (2.6%) receiving KYZATREX® in Study MRS-TU-2019EXT had an increase in PSA from baseline greater than 1.4 ng/mL and two out of 155 patients (1.3%) had a PSA of at least 4.0 ng/mL during Study MRS-TU-2019EXT. The mean (SE) increase in PSA from baseline was 0.15 (±0.04) ng/mL at 6 months (n=135).
Risk Summary
KYZATREX® is contraindicated in pregnant women and not indicated for use in females
[see
Contraindications (4)].
Testosterone is teratogenic and may cause fetal harm when administered to a pregnant woman based on data from animal studies (see
Data) and its mechanism of action
[see
Clinical Pharmacology (12.1)]. Exposure of a female fetus to androgens may result in varying degrees of virilization. In animal developmental studies, exposure to testosterone in utero resulted in hormonal and behavioral changes in offspring and structural impairments of reproductive tissues in female and male offspring. These studies do not meet current standards for nonclinical development toxicity studies.
Data
Animal Data
In developmental studies conducted in rats, rabbits, pigs, sheep, and rhesus monkeys, pregnant animals received intramuscular injections of testosterone during the period of organogenesis. Testosterone treatment at doses that were comparable to those used for testosterone replacement therapy resulted in structural impairments in both female and male offspring. Structural impairments observed in females included increased anogenital distance, phallus development, empty scrotum, no external vagina, intrauterine growth retardation, reduced ovarian reserve, and increased ovarian follicular recruitment. Structural impairments seen in male offspring included increased testicular weight, larger seminal tubular lumen diameter, and higher frequency of occluded tubule lumen. Increased pituitary weight was seen in both sexes.
Testosterone exposure in utero also resulted in hormonal and behavioral changes in offspring. Hypertension was observed in pregnant female rats and their offspring exposed to doses approximately twice those used for testosterone replacement therapy.
Risk Summary
KYZATREX® is not indicated for use in females.
Infertility
Males
During treatment with large doses of exogenous androgens, including KYZATREX®, spermatogenesis may be suppressed through feedback inhibition of the hypothalamicpituitary-testicular axis
[see[See Warnings and Precautions (5.7) and
Impairment of Fertility (13.1)]
, possibly leading to adverse effects on semen parameters including sperm count. Reduced fertility has been observed in some men taking testosterone replacement therapy. Testicular atrophy, subfertility, and infertility have also been reported in men who abuse anabolic androgenic steroids
[see
Drug Abuse and Dependence (9.2)].
With either type of use, the impact on fertility may be irreversible.
Abuse-Related Adverse Reactions
Serious adverse reactions have been reported in individuals who abuse anabolic androgenic steroids and include cardiac arrest, myocardial infarction, hypertrophic cardiomyopathy, congestive heart failure, cerebrovascular accident, hepatotoxicity, and serious psychiatric manifestations, including major depression, mania, paranoia, psychosis, delusions, hallucinations, hostility, and aggression.
The following adverse reactions have also been reported in men: transient ischemic attacks, convulsions, hypomania, irritability, dyslipidemias, testicular atrophy, subfertility, and infertility.
The following additional adverse reactions have been reported in women: hirsutism, virilization, deepening of voice, clitoral enlargement, breast atrophy, male-pattern baldness, and menstrual irregularities. The following adverse reactions have been reported in male and female adolescents: premature closure of bony epiphyses with termination of growth, and precocious puberty.
Because these reactions are reported voluntarily from a population of uncertain size and may include abuse of other agents, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Behaviors Associated with Addiction
Continued abuse of testosterone and other anabolic steroids leading to addiction is characterized by the following behaviors:
- Taking greater dosages than prescribed
- Continued drug use despite medical and social problems due to drug use
- Spending significant time to obtain the drug when supplies of the drug are interrupted
- Giving a higher priority to drug use than other obligations
- Having difficulty in discontinuing the drug despite desires and attempts to do so
- Experiencing withdrawal symptoms upon abrupt discontinuation of use
Physical dependence is characterized by withdrawal symptoms after abrupt drug discontinuation or a significant dose reduction of a drug. Individuals taking supratherapeutic doses of testosterone may experience withdrawal symptoms lasting for weeks or months, which may include depressed mood, major depression, fatigue, craving, restlessness, irritability, anorexia, insomnia, decreased libido, and hypogonadotropic hypogonadism.
Drug dependence in individuals using approved doses of testosterone for approved indications has not been documented.
Absorption
KYZATREX® was taken orally at a starting dose of 200 mg twice per day with meals in a multicenter, open-label trial in hypogonadal males. The dose was adjusted, as needed, on Days 28 and 56 from a minimum dose of 100 mg (morning-only) to a maximum dose of 400 mg twice per day based on the plasma testosterone concentration obtained by a single blood draw collected 3 to 5 hours after the morning dose. The average daily NaF/EDTA plasma testosterone concentration was 393.3 (±113.6) ng/dL after 90 days of treatment (normal eugonadal range in NaF/EDTA plasma: 222-800 ng/dL. Note that the titration scheme for use in clinical practice is based on serum total testosterone
[see
Dosage and Administration (2.2)]
.
KYZATREX® is expected to produce testosterone concentrations that approximate normal concentrations seen in healthy men.
Table 5 summarizes the pharmacokinetic (PK) parameters for plasma total testosterone in patients completing at least 90 days of KYZATREX® treatment administered daily.
Table 5: NaF-EDTA Plasma Testosterone C
avg and C
max at Day 90 Visit
| PK Parameter | Plasma (N=130) |
|---|
| PK = pharmacokinetic; C
avg = 24-hour average concentration; C
max = maximum concentration
|
| C
avg (ng/dL)
| n | 127 |
| Mean | 393.3 |
| SD | 113.6 |
| C
max (ng/dL)
| n | 130 |
| Mean | 852.4 |
| SD | 311.3 |
Figure 2 summarizes the mean plasma total testosterone profile at the final PK visit.
Figure 2: Mean (±SEM) Concentration-Time Profile for NaF-EDTA Plasma Total Testosterone in KYZATREX®-Treated Patients at Day 90 Visit
|
SEM = standard error of the mean
Testosterone normal ranges: plasma = 222-800 ng/dL
|
When KYZATREX® was given with breakfast containing 16%, 33%, and 45% fat, the exposure (AUC
0-24 hr) of testosterone was increased by 37%, 87%, and 94%, respectively, compared to when given under fasted conditions. The primary efficacy and safety study was conducted under fed conditions regardless of the type of meals and the primary efficacy endpoint of achieving testosterone C
avg in normal testosterone range was met.
There was no effect on testosterone PK when KYZATREX® was administered with 20% alcohol along with a high-fat meal versus a high-fat meal alone.
Distribution
Circulating testosterone is primarily bound in serum to sex hormone-binding globulin (SHBG) and albumin. Approximately 40% of testosterone in plasma is bound to SHBG, 2% remains unbound (free), and the rest is loosely bound to albumin and other proteins.
Metabolism
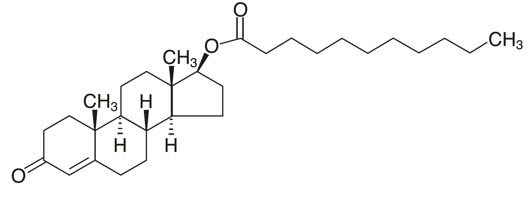
The androgenic activity of testosterone undecanoate occurs after the ester bond linking the testosterone to the undecanoic acid is cleaved by endogenous non-specific esterases.
Undecanoic acid is metabolized like all fatty acids via the beta-oxidation pathway.
Testosterone is metabolized to various 17-keto steroids through two different pathways. The major active metabolites of testosterone are dihydrotestosterone (DHT) and estradiol.
Excretion
About 90% of a dose of testosterone given intramuscularly is excreted in the urine as glucuronic and sulfuric acid conjugates of testosterone and its metabolites. About 6% of a dose is excreted in the feces, mostly in the unconjugated form. Inactivation of testosterone occurs primarily in the liver.
Carcinogenesis
Testosterone has been tested by subcutaneous injection and implantation in mice and rats. In mice, the implant induced cervical-uterine tumors, which metastasized in some cases. There is suggestive evidence that injection of testosterone into some strains of female mice increases their susceptibility to hepatoma. Testosterone is also known to increase the number of tumors and decrease the degree of differentiation of chemically induced carcinomas of the liver in rats.
Mutagenesis
Testosterone was negative in the in vitro Ames and in the in vivo mouse micronucleus assays.
Impairment of Fertility
The administration of exogenous testosterone suppressed spermatogenesis and impaired fertility in the rat, dog, and non-human primate, which was reversible on cessation of treatment.
A reproductive toxicology study was conducted in rats to evaluate functional effects of KYZATREX® on male fertility. In untreated female rats mated with males receiving 2 times the maximum recommended human daily dose (MRHDD) of KYZATREX® (based on mean AUC exposure to testosterone), the number of impregnated females was reduced, fertility was significantly lower, and pre-implantation loss was significantly higher compared to the control group. There was no impairment of fertility in males receiving an equivalent dose of KYZATREX® to the MRHDD.
Polycythemia
Advise patients that KYZATREX® can cause an increase in hemoglobin/hematocrit levels that may increase the risk of thromboembolic events. Advise patients about the importance of completing laboratory testing as instructed by their health care provider while on KYZATREX®
[see Warnings and Precautions (5.1)].
Venous Thromboebolisn
Advise patients that KYZATREX® can cause venous thromboembolism. Advise patients of the signs and symptoms of venous thromboembolism, which may include the following: lower limb pain, edema, or erythema; and dyspnea or chest pain. Advise patients to promptly report the signs and symptoms of venous thromboembolism, discontinue use of KYZATREX® and seek urgent medical care.
Worsening of Benign Prostatic Hyperplasia (BPH)
Advise patients that KYZATREX® can cause increased symptoms of BPH. Advise patients to contact their health care provider if they have any prostate-related symptoms
[see Warnings and Precautions (5.3)].
Blood Pressure Increases
Inform patients that KYZATREX® can increase blood pressure (BP) which can increase cardiovascular risk over time Instruct patients about the importance of monitoring BP periodically while on KYZATREX®. If BP increases while on KYZATREX®, antihypertensive medications may need to be started, added, or adjusted to control BP, or KYZATREX® may need to be discontinued
[see Warnings and Precautions (5.4)]
Edema
Advise patients that KYZATREX® can cause edema in patients with preexisting cardiac, renal, or hepatic disease. Advise patients to notify their health care provider if edema develops or worsens
[see Warnings and Precautions (5.9)].
Sleep Apnea
Advise patients that KYZATREX® can worsen sleep apnea especially in patients with risk factors such as obesity or chronic lung diseases ™
[see Warnings and Precautions (5.10)].
Gynecomastia
Advise patients that KYZATREX® can cause gynecomastia
[see Warnings and Precautions (5.11)].
Administration Instructions
Advise patients to take KYZATREX® with food
[see
Dosage and Administration (2.3)].
Marketed by:
Marius Pharmaceuticals
2301 Suger Bush Road, Suite 510
Raleigh, NC 27612
Issued 08/2026