Cisatracurium Besylate Injection is not recommended for rapid sequence endotracheal intubation due to the time required for its onset of action.
Accidental administration of neuromuscular blocking agents may be fatal. Store Cisatracurium Besylate Injection with the cap and ferrule intact and in a manner that minimizes the possibility of selecting the wrong product [see Warnings and Precautions (5.5)].
- Cisatracurium Besylate Injection is for intravenous use only.
- Administer Cisatracurium Besylate Injection in carefully adjusted dosage by or under the supervision of experienced clinicians who are familiar with the drug's actions and the possible complications.
- Use Cisatracurium Besylate Injection only if the following are immediately available: personnel and facilities for resuscitation and life support (tracheal intubation, artificial ventilation, oxygen therapy); and an antagonist of Cisatracurium Besylate Injection [see Overdosage (10)].
- The dosage information which follows is intended to serve as an initial guide for individual patients; base subsequent Cisatracurium Besylate Injection dosage on the patients' responses to the initial doses.
- Use a peripheral nerve stimulator to:
- Determine the adequacy of neuromuscular blockade (e.g., need for additional Cisatracurium Besylate Injection doses, reduction of the infusion rate).
- Minimize risk of overdosage or underdosage.
- Assess the extent of recovery from neuromuscular blockade (e.g., spontaneous recovery or recovery after administration of a reversal agent, e.g., neostigmine).
- Appropriately titrate doses to potentially limit exposure to toxic metabolites.
- Facilitate more rapid reversal of the Cisatracurium Besylate Injection-induced paralysis.
Tracheal Intubation in Adults
Prior to selecting the initial Cisatracurium Besylate Injection bolus dose, consider the desired time to tracheal intubation and the anticipated length of surgery, factors affecting time to onset of complete neuromuscular block such as age and renal function, and factors that may influence intubation conditions such as the presence of co-induction agents (e.g., fentanyl and midazolam) and the depth of anesthesia.
In conjunction with a propofol/nitrous oxide/oxygen induction-intubation technique or a thiopental/nitrous oxide/oxygen induction-intubation technique, the recommended starting weight-based dose of Cisatracurium Besylate Injection is between 0.15 mg/kg and 0.2 mg/kg administered by bolus intravenous injection. Doses up to 0.4 mg/kg have been safely administered by bolus intravenous injection to healthy patients and patients with serious cardiovascular disease [see Clinical Pharmacology (12.2)].
Patients with Neuromuscular Disease
The maximum recommended initial bolus dose of Cisatracurium Besylate Injection is 0.02 mg/kg in patients with neuromuscular diseases (e.g., myasthenia gravis and myasthenic syndrome and carcinomatosis) [see Warnings and Precautions (5.1)].
Geriatric Patients and Patients with End-Stage Renal Disease
Because the time to maximum neuromuscular blockade is approximately 1 minute slower in geriatric patients compared to younger patients (and in patients with end-stage renal disease than in patients with normal renal function), consider extending the interval between administering Cisatracurium Besylate Injection and attempting intubation by at least 1 minute to achieve adequate intubation conditions in geriatric patients and patients with end-stage renal disease. A peripheral nerve stimulator should be used to determine the adequacy of muscle relaxation for the purposes of intubation and the timing and amounts of subsequent doses [see Use in Specific Populations (8.5, 8.6) and Clinical Pharmacology (12.3)].
Tracheal Intubation in Pediatric Patients
Infants 1 to 23 Months of Age
The recommended dose of Cisatracurium Besylate Injection for intubation of pediatric patients ages 1 month to 23 months is 0.15 mg/kg administered over 5 to 10 seconds. When administered during stable opioid/nitrous oxide/oxygen anesthesia, 0.15 mg/kg of Cisatracurium Besylate Injection produced maximum neuromuscular blockade in about 2 minutes (range: 1.3 to 4.3 minutes) with a clinically effective block (time to 25% recovery) for about 43 minutes (range: 34 to 58 minutes) [see Clinical Studies (14.2)].
Pediatric Patients 2 to 12 Years of Age
The recommended weight-based bolus dose of Cisatracurium Besylate Injection for pediatric patients 2 to 12 years of age is 0.1 to 0.15 mg/kg administered over 5 to 10 seconds. When administered during stable opioid/nitrous oxide/oxygen anesthesia, 0.1 mg/kg Cisatracurium Besylate Injection produced maximum neuromuscular blockade in an average of 2.8 minutes (range: 1.8 to 6.7 minutes) with a clinically effective block (time to 25% recovery) for 28 minutes (range: 21 to 38 minutes). When administered during stable opioid/nitrous oxide/oxygen anesthesia, 0.15 mg/kg Cisatracurium Besylate Injection produced maximum neuromuscular blockade in an average of about 3 minutes (range: 1.5 to 8 minutes) with a clinically effective block for 36 minutes (range: 29 to 46 minutes) [see Clinical Studies (14.2)].
Continuous Infusion for Surgical Procedures in Adults and Pediatric Patients
During extended surgical procedures, Cisatracurium Besylate Injection may be administered by continuous infusion to adults and pediatric patients aged 2 or more years if patients have spontaneous recovery after the initial Cisatracurium Besylate Injection bolus dose. Following recovery from neuromuscular blockade, it may be necessary to re-administer a bolus dose to quickly re-establish neuromuscular blockade prior to starting the continuous infusion.
If patients have had recovery of neuromuscular function, the recommended initial Cisatracurium Besylate Injection infusion rate is 3 mcg/kg/minute [see Dosage and Administration (2.6)]. Subsequently reduce the rate to 1 to 2 mcg/kg/minute to maintain continuous neuromuscular blockade. Use peripheral nerve stimulation to assess the level of neuromuscular blockade and to appropriately titrate the Cisatracurium Besylate Injection infusion rate. If no response is elicited to peripheral nerve stimulation, discontinue the infusion until a response returns.
Consider reducing the infusion rate by up to 30% to 40% when Cisatracurium Besylate Injection is administered during stable isoflurane anesthesia for at least 30 minutes (administered with nitrous oxide/oxygen at the 1.25 MAC level) [see Clinical Pharmacology (12.2)]. Greater reductions in the Cisatracurium Besylate Injection infusion rate may be required with longer durations of administration of isoflurane or with the administration of other inhalational anesthetics.
Patients Undergoing Coronary Artery Bypass Graft (CABG) Surgery
Consider reducing the infusion rate in patients undergoing CABG with induced hypothermia to half the rate required during normothermia [see Clinical Pharmacology (12.2)]. Spontaneous recovery from neuromuscular block following discontinuation of Cisatracurium Besylate Injection infusion is expected to proceed at a rate comparable to that following administration of a single bolus dose.
Continuous Infusion for Mechanical Ventilation in the Intensive Care Unit in Adults
During extended need for mechanical ventilation and skeletal muscle relaxation in the intensive care unit (ICU), Cisatracurium Besylate Injection may be administered by continuous infusion to adults if a patient has spontaneous recovery of neuromuscular function after the initial Cisatracurium Besylate Injection bolus dose. Following recovery from neuromuscular blockade, it may be necessary to re-administer a bolus dose to quickly re-establish neuromuscular blockade prior to starting the continuous infusion.
The recommended Cisatracurium Besylate Injection infusion rate in adult patients in the ICU is 3 mcg/kg/minute (range: 0.5 to 10.2 mcg/kg/minute) [see Dosage and Administration (2.6)]. Use peripheral nerve stimulation to assess the level of neuromuscular blockade and to appropriately titrate the Cisatracurium Besylate Injection infusion rate.
Adverse Reactions in Clinical Trials of Cisatracurium Besylate Injection in Surgical Patients
The data presented below are based on studies involving 945 surgical patients who received Cisatracurium Besylate Injection in conjunction with other drugs in US and European clinical studies in a variety of procedures [see Clinical Studies (14.1)].
Table 3 displays adverse reactions that occurred at a rate of less than 1%.
Table 3: Adverse Reactions in Clinical Trials of Cisatracurium Besylate Injection in Surgical Patients
| Adverse Reaction | Incidence |
| Bradycardia
| 0.4%
|
| Hypotension
| 0.2%
|
| Flushing
| 0.2%
|
| Bronchospasm
| 0.2%
|
| Rash
| 0.1%
|
Adverse Reactions in Clinical Trials of Cisatracurium Besylate Injection in Intensive Care Unit Patients
The adverse reactions presented below were from studies involving 68 adult ICU patients who received Cisatracurium Besylate Injection in conjunction with other drugs in US and European clinical studies [see Clinical Studies (14.3)]. One patient experienced bronchospasm. In one of the two ICU studies, a randomized and double-blind study of ICU patients using TOF neuromuscular monitoring, there were two reports of prolonged recovery (range: 167 and 270 minutes) among 28 patients administered Cisatracurium Besylate Injection and 13 reports of prolonged recovery (range: 90 minutes to 33 hours) among 30 patients administered vecuronium.
Risk Summary
The 10 mL Cisatracurium Besylate Injection multiple-dose vials contain the preservative benzyl alcohol. Therefore, if Cisatracurium Besylate Injection is needed during pregnancy, consider using a benzyl alcohol-free formulation (i.e., 5 mL and 20 mL Cisatracurium Besylate Injection single-dose vials). Because benzyl alcohol is rapidly metabolized by a pregnant woman, benzyl alcohol exposure in the fetus is unlikely. However, adverse reactions have occurred in premature neonates and low birth weight infants who received intravenously administered benzyl alcohol-containing drugs [see Contraindications (4) and Use in Specific Populations (8.4)].
There are no available clinical trial data on cisatracurium use in pregnancy to evaluate a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Animal studies conducted in rats administered cisatracurium besylate during organogenesis (Gestational Day 6 to 15) found no evidence of fetal harm at 0.8 times (ventilated rats) the exposure from a human starting IV bolus dose of 0.2 mg/kg (see Data).
The estimated background risk for major birth defects and miscarriage in the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations
Labor or Delivery
The action of neuromuscular blocking agents may be enhanced by magnesium salts administered for the management of preeclampsia or eclampsia of pregnancy.
Data
Animal Data
Two embryofetal developmental reproductive toxicity studies were conducted in rats. In a non-ventilated rat study, pregnant animals were treated with cisatracurium besylate subcutaneously twice per day from Gestational Day 6 to 15 using subparalyzing doses (2 and 4 mg/kg daily; equivalent to 6- and 12-times, respectively, the AUC exposure in humans following a bolus dose of 0.2 mg/kg IV). In the ventilated rat study, pregnant animals were treated with cisatracurium besylate intravenously once a day between Gestational Day 6 to 15 using paralyzing doses (0.5 and 1 mg/kg; equivalent to 0.4- and 0.8-times, respectively, the exposure in humans following a bolus dose of 0.2 mg/kg IV based on mg/m2 comparison). Neither of these studies revealed maternal or fetal toxicity or malformations.
Risk Summary
The 10 mL Cisatracurium Besylate Injection multiple-dose vials contain the preservative benzyl alcohol. Therefore, if Cisatracurium Besylate Injection is needed during lactation, consider using a benzyl alcohol-free formulation (i.e., 5 mL and 20 mL Cisatracurium Besylate Injection single-dose vials). Because benzyl alcohol is rapidly metabolized by a lactating woman, benzyl alcohol exposure in the breastfed infant is unlikely. However, adverse reactions have occurred in premature neonates and low birth weight infants who received intravenously administered benzyl alcohol-containing drugs [see Contraindications (4) and Use in Specific Populations (8.4)].
There are no data on the presence of cisatracurium besylate in human milk, the effects on the breastfed child, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for Cisatracurium Besylate Injection and any potential adverse effects on the breastfed child from Cisatracurium Besylate Injection or from the underlying maternal condition.
Tracheal Intubation
A study of 0.15 mg/kg Cisatracurium Besylate Injection evaluated 230 pediatric patients (ages 1 month to 12 years). Excellent or good intubating conditions were produced 120 seconds following 0.15 mg/kg of Cisatracurium Besylate Injection in 88 of 90 of patients induced with halothane and in 85 of 90 of patients induced with thiopentone and fentanyl. The study also evaluated 50 pediatric patients during opioid anesthesia, with maximum neuromuscular blockade achieved in an average of about 3 minutes and a clinically effective block for 36 minutes in patients ages 2 to 12 years, and maximum neuromuscular block in about 2 minutes and a clinically effective block for about 43 minutes in infants 1 to 23 months [see Clinical Studies (14.2)].
In a study of 0.1 mg/kg Cisatracurium Besylate Injection administered in 16 pediatric patients (ages 2 to 12 years) during opioid/nitrous oxide/oxygen anesthesia, maximum neuromuscular blockade was achieved in an average of 2.8 minutes with a clinically effective block for 28 minutes [see Clinical Studies (14.2)].
Skeletal Muscle Relaxation During Surgery
In a study of Cisatracurium Besylate Injection administered during halothane/nitrous oxide/oxygen anesthesia, 18 pediatric patients (ages 2 to 12 years) were scheduled for surgical procedures that required neuromuscular block for 60 minutes or longer. The average duration of continuous infusion was 62.8 minutes (range: 17 to 145 minutes). The overall mean infusion rate for 9 patients whose infusion was 45 minutes or longer was 1.7 mcg/kg/minute (range: 1.19 to 2.14 mcg/kg/minute).
Hemodynamics Profile
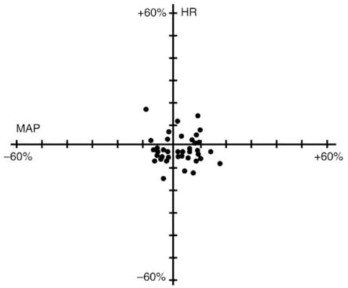
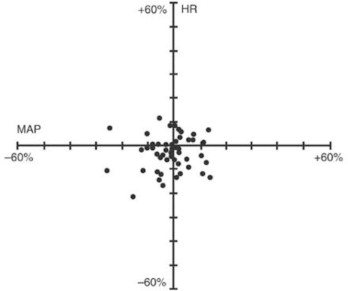
Cisatracurium Besylate Injection had no dose-related effects on mean arterial blood pressure (MAP) or heart rate (HR) following doses ranging from 0.1 mg/kg to 0.4 mg/kg, administered over 5 to 10 seconds, in healthy adult patients (see Figure 1) or in patients with serious cardiovascular disease (see Figure 2).
A total of 141 patients undergoing coronary artery bypass graft (CABG) surgery were administered Cisatracurium Besylate Injection in three active-controlled clinical trials and received doses ranging from 0.1 mg/kg to 0.4 mg/kg. While the hemodynamic profile was comparable in both the Cisatracurium Besylate Injection and active control groups, data for doses above 0.3 mg/kg in this population are limited.
Figure 1: Maximum Percent Change from Preinjection in HR and MAP During First 5 Minutes after Initial 4 × ED95
to 8 × ED95 Cisatracurium Besylate Injection Doses in Healthy Adults Who Received Opioid/Nitrous Oxide/Oxygen Anesthesia (n = 44)
Figure 2: Percent Change from Preinjection in HR and MAP 10 Minutes After an Initial 4 × ED95 to 8 × ED95 Cisatracurium Besylate Injection Dose in Patients Undergoing CABG Surgery Receiving Oxygen/Fentanyl/Midazolam/Anesthesia (n = 54)
No clinically significant changes in MAP or HR were observed following administration of doses up to 0.1 mg/kg Cisatracurium Besylate Injection over 5 to 10 seconds in 2- to 12-year-old pediatric patients who received either halothane/nitrous oxide/oxygen or opioid/nitrous oxide/oxygen anesthesia. Doses of 0.15 mg/kg Cisatracurium Besylate Injection administered over 5 seconds were not consistently associated with changes in HR and MAP in pediatric patients aged 1 month to 12 years who received opioid/nitrous oxide/oxygen or halothane/nitrous oxide/oxygen anesthesia.
Distribution
The volume of distribution of cisatracurium is limited by its large molecular weight and high polarity. The Vss was equal to 145 mL/kg (Table 6) in healthy 19 to 64 year-old surgical patients receiving opioid anesthesia. The Vss was 21% larger in similar patients receiving inhalation anesthesia.
The binding of cisatracurium to plasma proteins has not been successfully studied due to its rapid degradation at physiologic pH. Inhibition of degradation requires nonphysiological conditions of temperature and pH which are associated with changes in protein binding.
Elimination
Organ-independent Hofmann elimination (a chemical process dependent on pH and temperature) is the predominant pathway for the elimination of cisatracurium. The liver and kidney play a minor role in the elimination of cisatracurium but are primary pathways for the elimination of metabolites. Therefore, the t½β values of metabolites (including laudanosine) are longer in patients with renal or hepatic impairment and metabolite concentrations may be higher after long-term administration [see Warnings and Precautions (5.3)].
The mean CL values for cisatracurium ranged from 4.5 to 5.7 mL/min/kg in studies of healthy surgical patients. The compartmental PK modeling suggests that approximately 80% of the cisatracurium CL is accounted for by Hofmann elimination and the remaining 20% by renal and hepatic elimination. These findings are consistent with the low magnitude of interpatient variability in CL (16%) estimated as part of the population PK/PD analyses and with the recovery of parent and metabolites in urine.
In studies of healthy surgical patients, mean t½β values of cisatracurium ranged from 22 to 29 minutes and were consistent with the t½β of cisatracurium in vitro (29 minutes). The mean ± SD t½β values of laudanosine were 3.1 ± 0.4 and 3.3 ± 2.1 hours in healthy surgical patients receiving Cisatracurium Besylate Injection (n = 10).
Metabolism
The degradation of cisatracurium was largely independent of liver metabolism. Results from in vitro experiments suggest that cisatracurium undergoes Hofmann elimination (a pH and temperature-dependent chemical process) to form laudanosine [see Warnings and Precautions (5.3)] and the monoquaternary acrylate metabolite, neither of which has any neuromuscular blocking activity. The monoquaternary acrylate undergoes hydrolysis by non-specific plasma esterases to form the monoquaternary alcohol (MQA) metabolite. The MQA metabolite can also undergo Hofmann elimination but at a much slower rate than cisatracurium. Laudanosine is further metabolized to desmethyl metabolites which are conjugated with glucuronic acid and excreted in the urine.
The laudanosine metabolite of cisatracurium has been noted to cause transient hypotension and, in higher doses, cerebral excitatory effects when administered to several animal species. The relationship between CNS excitation and laudanosine concentrations in humans has not been established [see Warnings and Precautions (5.3)].
During IV infusions of Cisatracurium Besylate Injection, peak plasma concentrations (Cmax) of laudanosine and the MQA metabolite were approximately 6% and 11% of the parent compound, respectively. The Cmax values of laudanosine in healthy surgical patients receiving infusions of Cisatracurium Besylate Injection were mean ± SD Cmax: 60 ± 52 ng/mL.
Excretion
Following 14C-cisatracurium administration to 6 healthy male patients, 95% of the dose was recovered in the urine (mostly as conjugated metabolites) and 4% in the feces; less than 10% of the dose was excreted as unchanged parent drug in the urine. In 12 healthy surgical patients receiving non-radiolabeled cisatracurium who had Foley catheters placed for surgical management, approximately 15% of the dose was excreted unchanged in the urine.
Special Populations
Geriatric Patients
The results of conventional PK analysis from a study of 12 healthy elderly patients and 12 healthy young adult patients who received a single IV Cisatracurium Besylate Injection dose of 0.1 mg/kg are summarized in Table 7. Plasma clearances of cisatracurium were not affected by age; however, the volumes of distribution were slightly larger in elderly patients than in young patients resulting in slightly longer t½β values for cisatracurium.
The rate of equilibration between plasma cisatracurium concentrations and neuromuscular blockade was slower in elderly patients than in young patients (mean ± SD keo: 0.071 ± 0.036 and 0.105 ± 0.021 minutes-1, respectively); there was no difference in the patient sensitivity to cisatracurium-induced block, as indicated by EC50 values (mean ± SD EC50: 91 ± 22 and 89 ± 23 ng/mL, respectively). These changes were consistent with the 1-minute slower times to maximum block in elderly patients receiving 0.1 mg/kg Cisatracurium Besylate Injection, when compared to young patients receiving the same dose. The minor differences in PK/PD parameters of cisatracurium between elderly patients and young patients were not associated with clinically significant differences in the recovery profile of Cisatracurium Besylate Injection.
Table 7: Pharmacokinetic Parameters* of Cisatracurium in Healthy Elderly and Young Adult Patients Following 0.1 mg/kg (2 × ED95) of Cisatracurium Besylate Injection (Isoflurane/Nitrous Oxide/Oxygen Anesthesia)
|
|
|
| Parameter | Healthy
Elderly Patients | Healthy
Young Adult Patients |
| Elimination Half-Life (t½β, min)
| 25.8 ± 3.6† | 22.1 ± 2.5
|
| Volume of Distribution at Steady State‡ (mL/kg)
| 156 ± 17† | 133 ± 15
|
| Plasma Clearance (mL/min/kg)
| 5.7 ± 1.0
| 5.3 ± 0.9
|
Patients with Hepatic Impairment
Table 8 summarizes the conventional PK analysis from a study of Cisatracurium Besylate Injection in 13 patients with end-stage liver disease undergoing liver transplantation and 11 healthy adult patients undergoing elective surgery. The slightly larger volumes of distribution in liver transplant patients were associated with slightly higher plasma clearances of cisatracurium. The parallel changes in these parameters resulted in no difference in t½β values. There were no differences in keo or EC50 between patient groups. The times to maximum neuromuscular blockade were approximately one minute faster in liver transplant patients than in healthy adult patients receiving 0.1 mg/kg Cisatracurium Besylate Injection. These minor PK differences were not associated with clinically significant differences in the recovery profile of Cisatracurium Besylate Injection.
The t½β values of metabolites are longer in patients with hepatic disease and concentrations may be higher after long-term administration.
Table 8: Pharmacokinetic Parameters* of Cisatracurium in Healthy Adult Patients and in Patients Undergoing Liver Transplantation Following 0.1 mg/kg (2 × ED95) of Cisatracurium Besylate Injection (Isoflurane/Nitrous Oxide/Oxygen Anesthesia)
|
|
|
| Parameter | Liver Transplant Patients | Healthy Adult Patients |
| Elimination Half-Life (t½β, min)
| 24.4 ± 2.9
| 23.5 ± 3.5
|
| Volume of Distribution at Steady State‡ (mL/kg)
| 195 ± 38† | 161 ± 23
|
| Plasma Clearance (mL/min/kg)
| 6.6 ± 1.1† | 5.7 ± 0.8
|
Patients with Renal Impairment
Results from a conventional PK study of Cisatracurium Besylate Injection in 13 healthy adult patients and 15 patients with end-stage renal disease (ESRD) who had elective surgery are summarized in Table 9. The PK/PD parameters of cisatracurium were similar in healthy adult patients and ESRD patients. The times to 90% neuromuscular blockade were approximately one minute slower in ESRD patients following 0.1 mg/kg Cisatracurium Besylate Injection. There were no differences in the durations or rates of recovery of Cisatracurium Besylate Injection between ESRD and healthy adult patients.
The t½β values of metabolites are longer in patients with ESRD and concentrations may be higher after long-term administration.
Population PK analyses showed that patients with creatinine clearances ≤ 70 mL/min had a slower rate of equilibration between plasma concentrations and neuromuscular block than patients with normal renal function; this change was associated with a slightly slower (~ 40 seconds) predicted time to 90% T1 suppression in patients with renal impairment following 0.1 mg/kg Cisatracurium Besylate Injection. There was no clinically significant alteration in the recovery profile of Cisatracurium Besylate Injection in patients with renal impairment. The recovery profile of Cisatracurium Besylate Injection is unchanged in the presence of renal or hepatic failure, which is consistent with predominantly organ-independent elimination.
Table 9: Pharmacokinetic Parameters* for Cisatracurium in Healthy Adult Patients and in Patients With End-Stage Renal Disease (ESRD) Who Received 0.1 mg/kg (2 × ED95) of Cisatracurium Besylate Injection (Opioid/Nitrous Oxide/Oxygen Anesthesia)
|
|
| Parameter | Healthy Adult Patients | ESRD Patients |
| Elimination Half-Life (t½β, min)
| 29.4 ± 4.1
| 32.3 ± 6.3
|
| Volume of Distribution at Steady State† (mL/kg)
| 149 ± 35
| 160 ± 32
|
| Plasma Clearance (mL/min/kg)
| 4.66 ± 0.86
| 4.26 ± 0.62
|
Intensive Care Unit (ICU) Patients
The PK of cisatracurium and its metabolites were determined in six ICU patients who received Cisatracurium Besylate Injection and are presented in Table 10. The relationships between plasma cisatracurium concentrations and neuromuscular blockade have not been evaluated in ICU patients.
Limited PK data are available for ICU patients with hepatic or renal impairment who received Cisatracurium Besylate Injection. Relative to Cisatracurium Besylate Injection-treated ICU patients with normal renal and hepatic function, metabolite concentrations (plasma and tissues) may be higher in Cisatracurium Besylate Injection-treated ICU patients with renal or hepatic impairment [see Warnings and Precautions (5.3)].
Table 10: Parameter Estimates* for Cisatracurium and Metabolites in ICU Patients After Long-Term (24 to 48 Hour) Administration of Cisatracurium Besylate Injection
|
|
|
| Parameter | Cisatracurium (n = 6) |
| Parent Compound
| CL (mL/min/kg)
| 7.45 ± 1.02
|
| t½ β(min)
| 26.8 ± 11.1
|
| Vβ (mL/kg)† | 280 ± 103
|
| Laudanosine
| Cmax (ng/mL)
| 707 ± 360
|
| t½β (hrs)
| 6.6 ± 4.1
|
| MQA metabolite
| Cmax (ng/mL)
| 152-181‡ |
| t½β (min)
| 26-31‡ |
Pediatric Population
The population PK/PD of cisatracurium were described in 20 healthy pediatric patients ages 2 to 12 years during halothane anesthesia, using the same model developed for healthy adult patients. The CL was higher in healthy pediatric patients (5.89 mL/min/kg) than in healthy adult patients (4.57 mL/min/kg) during opioid anesthesia. The rate of equilibration between plasma concentrations and neuromuscular blockade, as indicated by keo, was faster in healthy pediatric patients receiving halothane anesthesia (0.1330 minutes-1) than in healthy adult patients receiving opioid anesthesia (0.0575 minutes-1). The EC50 in healthy pediatric patients (125 ng/mL) was similar to the value in healthy adult patients (141 ng/mL) during opioid anesthesia. The minor differences in the PK/PD parameters of cisatracurium were associated with a faster time to onset and a shorter duration of cisatracurium-induced neuromuscular blockade in pediatric patients.
Sex and Obesity
Although population PK/PD analyses revealed that sex and obesity were associated with effects on the PK and/or PD of cisatracurium; these PK/PD changes were not associated with clinically significant alterations in the predicted onset or recovery profile of Cisatracurium Besylate Injection.
Use of Inhalation Agents
The use of inhalation agents was associated with a 21% larger Vss, a 78% larger keo, and a 15% lower EC50 for cisatracurium. These changes resulted in a slightly faster (~ 45 seconds) predicted time to 90% T1 suppression in patients who received 0.1 mg/kg cisatracurium during inhalation anesthesia than in patients who received the same dose of cisatracurium during opioid anesthesia; however, there were no clinically significant differences in the predicted recovery profile of Cisatracurium Besylate Injection between patient groups.
Drug Interaction Studies
Carbamazepine and phenytoin
The systemic clearance of cisatracurium was higher in patients who were on prior chronic anticonvulsant therapy of carbamazepine or phenytoin [see Warning and Precautions (5.9) and Drug Interactions (7.1)].
Carcinogenesis
Long-term animal studies to evaluate the carcinogenic potential of cisatracurium besylate have not been performed.
Mutagenesis
Cisatracurium besylate was evaluated in a battery of four genotoxicity assays. Evaluation of cisatracurium besylate in the in vitro mouse lymphoma forward gene mutation assay resulted in mutations in the presence and absence of exogenous metabolic activation. The in vitro bacterial reverse gene mutation (Ames) assay, in vitro human lymphocyte chromosomal aberration assay, and an in vivo rat bone marrow cytogenetic assay did not demonstrate evidence of mutagenicity or clastogenicity.
Impairment of Fertility
Studies to determine if cisatracurium besylate impacts fertility have not been completed.
Hypersensitivity Reactions Including Anaphylaxis
Advise the caregiver and/or family that severe hypersensitivity reactions have occurred with Cisatracurium Besylate Injection [see Warnings and Precautions (5.4)].
AVENACY
Mfd. for Avenacy
Schaumburg, IL 60173 (USA)
Made in China
©2026 Avenacy
April 2026