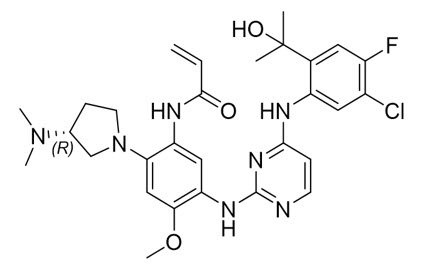
Sunvozertinib pharmacokinetics were observed at steady state at the approved recommended dosage and are presented as geometric mean (CV%) unless otherwise specified.
Sunvozertinib total systemic exposure (AUC) and maximum concentration (Cmax) increase approximately dose-proportionally across the dose range of 50 mg (0.25 times the approved recommended dose) to 400 mg (2 times the approved recommended dose). Steady state is reached within 15 days and the mean accumulation of AUC was approximately 3-fold. The steady-state Cmax and AUC of sunvozertinib were 412 (45%) ng/mL and 8,060 (42%) h*ng/mL, respectively.
Absorption
Sunvozertinib median (minimum, maximum) time to maximum plasma concentration (tmax) is approximately 6 hours (3, 10 hours).
Effect of Food
No clinically significant differences in sunvozertinib AUC and Cmax were observed following administration of sunvozertinib with a high-fat meal (approximately 1,000 calories, approximately 50% fat).
Distribution
The apparent (oral) volume of distribution is 2,116 L (81%). Sunvozertinib plasma protein binding ranges from approximately 89% to 94% in vitro.
Elimination
Sunvozertinib elimination half-life is 50 hours (27%) with an apparent (oral) clearance of 29 L/h (54%).
Metabolism
Sunvozertinib is primarily metabolized by CYP3A and forms the active demethylated metabolite, DZ0753. DZ0753 AUC represents 10% of the parent AUC.
Excretion
Following a single oral dose of radiolabeled sunvozertinib, 79% of the dose was recovered in feces (7.3% unchanged) and 10% in urine (5.6% unchanged).
Specific Populations
No clinically significant differences in the pharmacokinetics of sunvozertinib were observed based on age (19 to 96 years), sex, race (Asian 62%, White 28%, Black or African American 8%), body weight (30 to 118 kg), smoking status, mild to moderate renal impairment (CLcr 30 to 89 mL/min, estimated by Cockcroft-Gault), and mild (bilirubin ≤ ULN and AST > ULN or bilirubin >1 to 1.5 × ULN and any AST) to moderate (bilirubin ≥1.5 to 3 × ULN and any AST) hepatic impairment. The effect of severe hepatic impairment (total bilirubin >3 × ULN and any AST) and severe renal impairment (CLcr 15 to 29 mL/min) on the pharmacokinetics of sunvozertinib has not been studied.
Drug Interaction Studies
Clinical Studies and Model-Informed Approaches
Strong CYP3A Inhibitors: Sunvozertinib AUC increased by 1.5-fold and Cmax by 1.3-fold following concomitant administration of itraconazole (strong CYP3A inhibitor) 200 mg once daily.
Strong and Moderate CYP3A Inducers: Sunvozertinib AUC decreased by 48% and Cmax by 38% following concomitant administration of carbamazepine (strong CYP3A inducer) 300 mg twice daily.
Sunvozertinib AUC is predicted to decrease by 44% following concomitant administration of efavirenz (moderate CYP3A inducer) 600 mg once daily.
CYP3A Substrates: Midazolam (sensitive CYP3A substrate) AUC decreased by 23% and Cmax by 15% following concomitant administration of ZEGFROVY.
P-glycoprotein (P-gp) Substrates: Digoxin (P-gp substrate) AUC increased by 1.4-fold and Cmax by 1.2-fold following concomitant administration of ZEGFROVY.
BCRP Substrates: Rosuvastatin (BCRP substrate) AUC increased by 1.4-fold and Cmax by 1.6-fold following concomitant administration of ZEGFROVY.
Other Drugs:
No clinically significant effect on sunvozertinib pharmacokinetics is predicted following concomitant administration of fluconazole (moderate CYP3A inhibitor) 200 mg once daily.
No clinically significant effect on sunvozertinib pharmacokinetics is predicted following concomitant administration of dexamethasone (weak CYP3A inducer) 8 mg once daily.
No clinically significant effect on the pharmacokinetics of desipramine (CYP2D6 substrate) is predicted when used concomitantly with ZEGFROVY.
No clinically significant effect on sunvozertinib pharmacokinetics was observed when used concomitantly with acid reducing agents (e.g. proton pump inhibitor).
In Vitro Studies
CYP450 Enzymes: Sunvozertinib induces CYP2C8.
Transporter Systems: Sunvozertinib is a substrate of P-gp. Sunvozertinib inhibits OATP1B1.