Hormone Receptor-Positive, HER2-Negative Breast Cancer
The safety of everolimus tablets (10 mg orally once daily) in combination with exemestane (25 mg orally once daily) (n = 485) vs. placebo in combination with exemestane (n = 239) was evaluated in a randomized, controlled trial (BOLERO-2) in patients with advanced or metastatic hormone receptor-positive, HER2-negative breast cancer. The median age of patients was 61 years (28 to 93 years), and 75% were white. The median follow-up was approximately 13 months. The most common adverse reactions (incidence ≥ 30%) were stomatitis, infections, rash, fatigue, diarrhea, and decreased appetite.
The most common Grade 3 to 4 adverse reactions (incidence ≥ 2%) were stomatitis, infections, hyperglycemia, fatigue, dyspnea, pneumonitis, and diarrhea. The most common laboratory abnormalities (incidence ≥ 50%) were hypercholesterolemia, hyperglycemia, increased aspartate transaminase (AST), anemia, leukopenia, thrombocytopenia, lymphopenia, increased alanine transaminase (ALT), and hypertriglyceridemia. The most common Grade 3 to 4 laboratory abnormalities (incidence ≥ 3%) were lymphopenia, hyperglycemia, anemia, hypokalemia, increased AST, increased ALT, and thrombocytopenia.
Fatal adverse reactions occurred in 2% of patients who received everolimus tablets. The rate of adverse reactions resulting in permanent discontinuation was 24% for the everolimus tablets arm. Dose adjustments (interruptions or reductions) occurred in 63% of patients in the everolimus tablets arm.
Adverse reactions reported with an incidence of ≥ 10% for patients receiving everolimus tablets versus placebo are presented in Table 6. Laboratory abnormalities are presented in Table 7. The median duration of treatment with everolimus tablets was 23.9 weeks; 33% were exposed to everolimus tablets for a period of ≥ 32 weeks.
Table 6: Adverse Reactions Reported in ≥ 10% of Patients With Hormone Receptor-Positive Breast Cancer in BOLERO-2 | Everolimus Tablets with Exemestane
N = 482
| Placebo with Exemestane
N = 238
|
|---|
| All Grades
%
| Grade 3 to 4
%
| All Grades
%
| Grade 3 to 4
%
|
|---|
| Grading according to NCI CTCAE Version 3.0. |
| Gastrointestinal | | | | |
| Stomatitis
Includes stomatitis, mouth ulceration, aphthous stomatitis, glossodynia, gingival pain, glossitis, and lip ulceration. | 67 | 8
No Grade 4 adverse reactions were reported. | 11 | 0.8 |
| Diarrhea | 33 | 2 | 18 | 0.8 |
| Nausea | 29 | 0.4 | 28 | 1 |
| Vomiting | 17 | 1 | 12 | 0.8 |
| Constipation | 14 | 0.4
| 13 | 0.4 |
| Dry mouth | 11 | 0 | 7 | 0 |
| General | | | | |
| Fatigue | 36 | 4 | 27 | 1
|
| Edema peripheral | 19 | 1
| 6 | 0.4
|
| Pyrexia | 15 | 0.2
| 7 | 0.4
|
| Asthenia | 13 | 2 | 4 | 0 |
| Infections | | | | |
| Infections
Includes all reported infections including but not limited to, urinary tract infections, respiratory tract (upper and lower) infections, skin infections, and gastrointestinal tract infections. | 50 | 6 | 25 | 2
|
| Investigations | | | | |
| Weight loss | 25 | 1
| 6 | 0 |
| Metabolism and Nutrition | | | | |
| Decreased appetite | 30 | 1
| 12 | 0.4
|
| Hyperglycemia | 14 | 5 | 2 | 0.4
|
| Musculoskeletal and connective tissue | | | | |
| Arthralgia | 20 | 0.8
| 17 | 0 |
| Back pain | 14 | 0.2
| 10 | 0.8
|
| Pain in extremity | 9 | 0.4
| 11 | 2
|
| Nervous system | | | | |
| Dysgeusia | 22 | 0.2
| 6 | 0 |
| Headache | 21 | 0.4
| 14 | 0 |
| Psychiatric | | | | |
| Insomnia | 13 | 0.2
| 8 | 0 |
| Respiratory, thoracic and mediastinal | | | | |
| Cough | 24 | 0.6
| 12 | 0 |
| Dyspnea | 21 | 4 | 11 | 1 |
| Epistaxis | 17 | 0 | 1 | 0 |
| Pneumonitis
Includes pneumonitis, interstitial lung disease, lung infiltration, and pulmonary fibrosis. | 19 | 4 | 0.4 | 0 |
| Skin and subcutaneous tissue | | | | |
| Rash | 39 | 1
| 8 | 0 |
| Pruritus | 13 | 0.2
| 5 | 0 |
| Alopecia | 10 | 0 | 5 | 0 |
| Vascular | | | | |
| Hot Flush | 6 | 0 | 14 | 0 |
Table 7: Selected Laboratory Abnormalities Reported in ≥ 10% of Patients with Hormone Receptor-Positive Breast Cancer in BOLERO-2| Laboratory Parameter | Everolimus Tablets with Exemestane
N = 482
| Placebo with Exemestane
N = 238
|
|---|
| All Grades
%
| Grade 3 to 4
%
| All Grades
%
| Grade 3 to 4
%
|
|---|
| Grading according to NCI CTCAE Version 3.0. |
| Hematology
Reflects corresponding adverse drug reaction reports of anemia, leukopenia, lymphopenia, neutropenia, and thrombocytopenia (collectively as pancytopenia), which occurred at lower frequency. | | | | |
| Anemia | 68 | 6 | 40 | 1 |
| Leukopenia | 58 | 2
No Grade 4 laboratory abnormalities were reported. | 28 | 6 |
| Thrombocytopenia | 54 | 3 | 5 | 0.4 |
| Lymphopenia | 54 | 12 | 37 | 6 |
| Neutropenia | 31 | 2
| 11 | 2 |
| Chemistry | | | | |
| Hypercholesterolemia | 70 | 1 | 38 | 2 |
| Hyperglycemia | 69 | 9 | 44 | 1 |
| Increased aspartate transaminase (AST) | 69 | 4 | 45 | 3 |
| Increased alanine transaminase (ALT) | 51 | 4 | 29 | 5
|
| Hypertriglyceridemia | 50 | 0.8
| 26 | 0 |
| Hypoalbuminemia | 33 | 0.8
| 16 | 0.8
|
| Hypokalemia | 29 | 4 | 7 | 1
|
| Increased creatinine | 24 | 2 | 13 | 0 |
Topical Prophylaxis for Stomatitis
In a single arm study (SWISH; N = 92) in postmenopausal women with hormone receptor-positive, HER2-negative breast cancer beginning everolimus tablets (10 mg orally once daily) in combination with exemestane (25 mg orally once daily), patients started dexamethasone 0.5 mg/5mL alcohol-free mouthwash (10 mL swished for 2 minutes and spat, 4 times daily for 8 weeks) concurrently with everolimus tablets and exemestane. No food or drink was to be consumed for at least 1 hour after swishing and spitting the dexamethasone mouthwash. The primary objective of this study was to assess the incidence of Grade 2 to 4 stomatitis within 8 weeks. The incidence of Grade 2 to 4 stomatitis within 8 weeks was 2%, which was lower than the 33% reported in the BOLERO-2 trial. The incidence of Grade 1 stomatitis was 19%. No cases of Grade 3 or 4 stomatitis were reported. Oral candidiasis was reported in 2% of patients in this study compared to 0.2% in the BOLERO-2 trial.
Coadministration of everolimus and dexamethasone alcohol-free oral solution has not been studied in pediatric patients.
Tuberous Sclerosis Complex (TSC)-Associated Renal Angiomyolipoma
The data described below are based on a randomized (2:1), double-blind, placebo-controlled trial (EXIST-2) of everolimus tablets in 118 patients with renal angiomyolipoma as a feature of TSC (n = 113) or sporadic lymphangioleiomyomatosis (n = 5). The median age of patients was 31 years (18 to 61 years), 89% were white, and 34% were male. The median duration of blinded study treatment was 48 weeks (2 to 115 weeks) for patients receiving everolimus tablets.
The most common adverse reaction reported for everolimus tablets (incidence ≥ 30%) was stomatitis. The most common Grade 3 to 4 adverse reactions (incidence ≥ 2%) were stomatitis and amenorrhea. The most common laboratory abnormalities (incidence ≥ 50%) were hypercholesterolemia, hypertriglyceridemia, and anemia. The most common Grade 3 to 4 laboratory abnormality (incidence ≥ 3%) was hypophosphatemia.
The rate of adverse reactions resulting in permanent discontinuation was 3.8% in the everolimus tablets-treated patients. Adverse reactions leading to permanent discontinuation in the Everolimus tablets arm were hypersensitivity/angioedema/bronchospasm, convulsion, and hypophosphatemia. Dose adjustments (interruptions or reductions) due to adverse reactions occurred in 52% of everolimus tablets-treated patients. The most common adverse reaction leading to everolimus tablets dose adjustment was stomatitis.
Adverse reactions reported with an incidence of ≥ 10% for patients receiving everolimus tablets and occurring more frequently with everolimus tablets than with placebo are presented in Table 14. Laboratory abnormalities are presented in Table 15.
Table 14: Adverse Reactions Reported in ≥ 10% of Everolimus Tablets-Treated Patients with TSC Associated Renal Angiomyolipoma in EXIST-2 | Everolimus Tablets
N = 79
| Placebo
N = 39
|
|---|
| All Grades
%
| Grade 3 to 4
%
| All Grades
%
| Grade 3 to 4
%
|
|---|
| Grading according to NCI CTCAE Version 3.0. Includes stomatitis, aphthous stomatitis, mouth ulceration, gingival pain, glossitis, and glossodynia. No Grade 4 adverse reactions were reported. |
| Gastrointestinal |
| Stomatitis
a | 78 | 6
b | 23 | 0 |
| Vomiting | 15 | 0 | 5 | 0 |
| Diarrhea | 14 | 0 | 5 | 0 |
| General | | | | |
| Peripheral Edema | 13 | 0 | 8 | 0 |
| Infections |
| Upper Respiratory tract infection | 11 | 0 | 5 | 0 |
| Musculoskeletal and connective tissue | | | | |
| Arthralgia | 13 | 0 | 5 | 0 |
| Respiratory, thoracic and mediastinal | | | | |
| Cough | 20 | 0 | 13 | 0 |
| Skin and subcutaneous tissue |
| Acne | 22 | 0 | 5 | 0 |
Amenorrhea occurred in 15% of everolimus tablets -treated females (8 of 52). Other adverse reactions involving the female reproductive system were menorrhagia (10%), menstrual irregularities (10%), and vaginal hemorrhage (8%).
The following additional adverse reactions occurred in less than 10% of everolimus tablets -treated patients: epistaxis (9%), decreased appetite (6%), otitis media (6%), depression (5%), abnormal taste (5%), increased blood luteinizing hormone (LH) levels (4%), increased blood follicle stimulating hormone (FSH) levels (3%), hypersensitivity (3%), ovarian cyst (3%), pneumonitis (1%), and angioedema (1%).
Table 15: Selected Laboratory Abnormalities Reported in Everolimus Tablets-Treated Patients With TSC-Associated Renal Angiomyolipoma in EXIST-2 | Everolimus Tablets
N = 79
| Placebo
N = 39
|
|---|
| All Grades
%
| Grade 3 to 4
%
| All Grades
%
| Grade 3 to 4
%
|
|---|
| Grading according to NCI CTCAE Version 3.0. |
| Hematology |
| Anemia | 61 | 0 | 49 | 0 |
| Leukopenia | 37 | 0 | 21 | 0 |
| Neutropenia | 25 | 1 | 26 | 0 |
| Lymphopenia | 20 | 1
No Grade 4 laboratory abnormalities were reported. | 8 | 0 |
| Thrombocytopenia | 19 | 0 | 3 | 0 |
| Chemistry |
| Hypercholesterolemia | 85 | 1
| 46 | 0 |
| Hypertriglyceridemia | 52 | 0 | 10 | 0 |
| Hypophosphatemia | 49 | 5
| 15 | 0 |
| Increased alkaline phosphatase | 32 | 1
| 10 | 0 |
| Increased AST | 23 | 1
| 8 | 0 |
| Increased ALT | 20 | 1
| 15 | 0 |
| Hyperglycemia (fasting) | 14 | 0 | 8 | 0 |
Updated safety information from 112 patients treated with everolimus tablets for a median duration of 3.9 years identified the following additional adverse reactions and selected laboratory abnormalities: increased partial thromboplastin time (63%), increased prothrombin time (40%), decreased fibrinogen (38%), urinary tract infection (31%), proteinuria (18%), abdominal pain (16%), pruritus (12%), gastroenteritis (12%), myalgia (11%), and pneumonia (10%).
TSC-Associated Subependymal Giant Cell Astrocytoma (SEGA)
The data described below are based on a randomized (2:1), double-blind, placebo-controlled trial (EXIST-1) of everolimus tablets in 117 patients with SEGA and TSC. The median age of patients was 9.5 years (0.8 to 26 years), 93% were white, and 57% were male. The median duration of blinded study treatment was 52 weeks (24 to 89 weeks) for patients receiving everolimus tablets.
The most common adverse reactions reported for everolimus tablets (incidence ≥ 30%) were stomatitis and respiratory tract infection. The most common Grade 3 to 4 adverse reactions (incidence ≥ 2%) were stomatitis, pyrexia, pneumonia, gastroenteritis, aggression, agitation, and amenorrhea. The most common laboratory abnormalities (incidence ≥ 50%) were hypercholesterolemia and elevated partial thromboplastin time. The most common Grade 3 to 4 laboratory abnormality (incidence ≥ 3%) was neutropenia.
There were no adverse reactions resulting in permanent discontinuation. Dose adjustments (interruptions or reductions) due to adverse reactions occurred in 55% of everolimus tablets-treated patients. The most common adverse reaction leading to everolimus tablets dose adjustment was stomatitis.
Adverse reactions reported with an incidence of ≥ 10% for patients receiving everolimus tablets and occurring more frequently with everolimus tablets than with placebo are reported in Table 16. Laboratory abnormalities are presented in Table 17.
Table 16: Adverse Reactions Reported in ≥ 10% of Everolimus Tablets-Treated Patients with TSC Associated SEGA in EXIST-1 | Everolimus Tablets
N = 78
| Placebo
N = 39
|
|---|
| All Grades
%
| Grade 3 to 4
%
| All Grades
%
| Grade 3 to 4
%
|
|---|
| Grading according to NCI CTCAE Version 3.0. |
| Gastrointestinal |
| Stomatitis
Includes mouth ulceration, stomatitis, and lip ulceration. | 62 | 9
No Grade 4 adverse reactions were reported. | 26 | 3
|
| Vomiting | 22 | 1
| 13 | 0 |
| Diarrhea | 17 | 0 | 5 | 0 |
| Constipation | 10 | 0 | 3 | 0 |
| Infections |
| Respiratory tract infection
Includes respiratory tract infection, upper respiratory tract infection, and respiratory tract infection viral. | 31 | 3 | 23 | 0 |
| Gastroenteritis
Includes gastroenteritis, gastroenteritis viral, and gastrointestinal infection. | 10 | 5 | 3 | 0 |
| Pharyngitis streptococcal | 10 | 0 | 3 | 0 |
| General |
| Pyrexia | 23 | 6
| 18 | 3
|
| Fatigue | 14 | 0 | 3 | 0 |
| Psychiatric |
| Anxiety, aggression or other behavioral disturbance
Includes agitation, anxiety, panic attack, aggression, abnormal behavior, and obsessive-compulsive disorder. | 21 | 5
| 3 | 0 |
| Skin and subcutaneous tissue |
| Rash
Includes rash, rash generalized, rash macular, rash maculo-papular, rash papular, dermatitis allergic, and urticaria. | 21 | 0 | 8 | 0 |
| Acne | 10 | 0 | 5 | 0 |
Amenorrhea occurred in 17% of everolimus tablets-treated females aged 10 to 55 years (3 of 18). For this same group of everolimus tablets-treated females, the following menstrual abnormalities were reported: dysmenorrhea (6%), menorrhagia (6%), metrorrhagia (6%), and unspecified menstrual irregularity (6%).
The following additional adverse reactions occurred in less than 10% of everolimus tablets-treated patients: nausea (8%), pain in extremity (8%), insomnia (6%), pneumonia (6%), epistaxis (5%), hypersensitivity (3%), increased blood luteinizing hormone (LH) levels (1%), and pneumonitis (1%).
Table 17: Selected Laboratory Abnormalities Reported in Everolimus Tablets-Treated Patients With TSC-Associated SEGA in EXIST-1 | Everolimus Tablets
N = 78
| Placebo
N = 39
|
|---|
| All Grades
%
| Grade 3 to 4
%
| All Grades
%
| Grade 3 to 4
%
|
|---|
| Grading according to NCI CTCAE Version 3.0. |
| Hematology |
| Elevated partial thromboplastin time | 72 | 3
No Grade 4 laboratory abnormalities were reported. | 44 | 5
|
| Neutropenia | 46 | 9
| 41 | 3
|
| Anemia | 41 | 0 | 21 | 0 |
| Chemistry |
| Hypercholesterolemia | 81 | 0 | 39 | 0 |
| Elevated AST | 33 | 0 | 0 | 0 |
| Hypertriglyceridemia | 27 | 0 | 15 | 0 |
| Elevated ALT | 18 | 0 | 3 | 0 |
| Hypophosphatemia | 9 | 1
| 3 | 0 |
Updated safety information from 111 patients treated with everolimus tablets for a median duration of 47 months identified the following additional notable adverse reactions and selected laboratory abnormalities: decreased appetite (14%), hyperglycemia (13%), hypertension (11%), urinary tract infection (9%), decreased fibrinogen (8%), cellulitis (6%), abdominal pain (5%), decreased weight (5%), elevated creatinine (5%), and azoospermia (1%).
Inhibitors
Avoid the concomitant use of P-gp and strong CYP3A4 inhibitors
[see
Dosage and Administration (2.11),
Clinical Pharmacology (12.3)]
.
Reduce the dose for patients taking TORPENZ with a P-gp and moderate CYP3A4 inhibitor as recommended
[see
Dosage and Administration (2.11),
Clinical Pharmacology (12.3)]
.
Inducers
Increase the dose for patients taking TORPENZ with a P-gp and strong CYP3A4 inducer as recommended
[see
Dosage and Administration (2.12),
Clinical Pharmacology (12.3)]
.
Risk Summary
Based on animal studies and the mechanism of action
[see
Clinical Pharmacology (12.1)]
, everolimus can cause fetal harm when administered to a pregnant woman. There are limited case reports of everolimus use in pregnant women; however, these reports are not sufficient to inform about risks of birth defects or miscarriage. In animal studies, everolimus caused embryo-fetal toxicities in rats when administered during the period of organogenesis at maternal exposures that were lower than human exposures at the recommended dose of everolimus tablets 10 mg orally once daily
(see
Data)
. Advise pregnant women of the potential risk to the fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage is 2% to 4% and 15% to 20% of clinically recognized pregnancies, respectively.
Data
Animal Data
In animal reproductive studies, oral administration of everolimus to female rats before mating and through organogenesis induced embryo-fetal toxicities, including increased resorption, pre-implantation and post-implantation loss, decreased numbers of live fetuses, malformation (e.g., sternal cleft), and retarded skeletal development. These effects occurred in the absence of maternal toxicities. Embryo-fetal toxicities in rats occurred at doses ≥ 0.1 mg/kg (0.6 mg/m
2) with resulting exposures of approximately 4% of the human exposure at the recommended dose of everolimus tablets 10 mg orally once daily based on area under the curve (AUC). In rabbits, embryo-toxicity evident as an increase in resorptions occurred at an oral dose of 0.8 mg/kg (9.6 mg/m
2), approximately 1.6 times the recommended dose of everolimus tablets 10 mg orally once daily or the median dose administered to patients with tuberous sclerosis complex (TSC)-associated subependymal giant cell astrocytoma (SEGA). The effect in rabbits occurred in the presence of maternal toxicities.
In a pre- and post-natal development study in rats, animals were dosed from implantation through lactation. At the dose of 0.1 mg/kg (0.6 mg/m
2), there were no adverse effects on delivery and lactation or signs of maternal toxicity; however, there were reductions in body weight (up to 9% reduction from the control) and in survival of offspring (~5% died or missing). There were no drug-related effects on the developmental parameters (morphological development, motor activity, learning, or fertility assessment) in the offspring.
Risk Summary
There are no data on the presence of everolimus or its metabolites in human milk, the effects of everolimus on the breastfed infant or on milk production. Everolimus and its metabolites passed into the milk of lactating rats at a concentration 3.5 times higher than in maternal serum. Because of the potential for serious adverse reactions in breastfed infants from everolimus, advise women not to breastfeed during treatment with everolimus and for 2 weeks after the last dose.
Pregnancy Testing
Verify the pregnancy status of females of reproductive potential prior to starting TORPENZ
[see
Use in Specific Populations (8.1)]
.
Contraception
TORPENZ can cause fetal harm when administered to pregnant women
[see
Use in Specific Populations (8.1)]
.
Females
Advise female patients of reproductive potential to use effective contraception during treatment with TORPENZ and for 8 weeks after the last dose.
Males
Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TORPENZ and for 4 weeks after the last dose.
Infertility
Females
Menstrual irregularities, secondary amenorrhea, and increases in luteinizing hormone (LH) and follicle stimulating hormone (FSH) occurred in female patients taking TORPENZ. Based on these findings, TORPENZ may impair fertility in female patients
[see
Adverse Reactions (6.1),
Nonclinical Toxicology (13.1)]
.
Males
Cases of reversible azoospermia have been reported in male patients taking everolimus tablets. In male rats, sperm motility, sperm count, plasma testosterone levels and fertility were diminished at AUC similar to those of the clinical dose of everolimus tablets 10 mg orally once daily. Based on these findings, TORPENZ may impair fertility in male patients
[see
Nonclinical Toxicology (13.1)]
.
TSC-Associated SEGA
The safety and effectiveness of everolimus have been established in pediatric patients age 1 year and older with TSC-associated SEGA that requires therapeutic intervention but cannot be curatively resected. Use of everolimus for this indication is supported by evidence from a randomized, double-blind, placebo-controlled trial in adult and pediatric patients (EXIST-1); an open-label, single-arm trial in adult and pediatric patients (Study 2485); and additional pharmacokinetic data in pediatric patients
[see
Adverse Reactions (6.1),
Clinical Pharmacology (12.3),
Clinical Studies (14.5)]
. The safety and effectiveness of everolimus have not been established in pediatric patients less than 1 year of age with TSC-associated SEGA.
In EXIST-1, the incidence of infections and serious infections were reported at a higher frequency in patients < 6 years of age. Ninety-six percent of 23 everolimus tablets-treated patients < 6 years had at least one infection compared to 67% of 55 everolimus tablets-treated patients ≥ 6 years. Thirty-five percent of 23 everolimus tablets-treated patients < 6 years of age had at least 1 serious infection compared to 7% of 55 everolimus tablets-treated patients ≥ 6 years.
Although a conclusive determination cannot be made due to the limited number of patients and lack of a comparator arm in the open label follow-up periods of EXIST-1 and Study 2485, everolimus tablets did not appear to adversely impact growth and pubertal development in the 115 pediatric patients treated with everolimus tablets for a median duration of 4.1 years.
Other Indications
The safety and effectiveness of everolimus in pediatric patients have not been established in:
- Hormone receptor-positive, HER2-negative breast cancer
- TSC-associated renal angiomyolipoma
Exposure-Response Relationship
In patients with TSC-associated subependymal giant cell astrocytoma (SEGA), the magnitude of the reduction in SEGA volume was correlated with the everolimus trough concentration.
Cardiac Electrophysiology
In a randomized, placebo-controlled, cross-over study, 59 healthy subjects were administered a single oral dose of everolimus tablets (20 mg and 50 mg) and placebo. Everolimus tablets at single doses up to 50 mg did not prolong the QT/QTc interval.
Absorption
After administration of everolimus tablets in patients with advanced solid tumors, peak everolimus concentrations are reached 1 to 2 hours after administration of oral doses ranging from 5 mg to 70 mg. Following single doses, C
maxis dose-proportional with daily dosing between 5 mg and 10 mg. With single doses of 20 mg and higher, the increase in C
maxis less than dose-proportional; however, AUC shows dose-proportionality over the 5 mg to 70 mg dose range. Steady-state was achieved within 2 weeks following once-daily dosing.
In patients with TSC-associated SEGA, everolimus C
minwas approximately dose-proportional within the dose range from 1.35 mg/m
2to 14.4 mg/m
2.
Effect of Food
In healthy subjects, a high-fat meal (containing approximately 1,000 calories and 55 grams of fat) reduced systemic exposure to everolimus tablets 10 mg (as measured by AUC) by 22% and the peak blood concentration C
maxby 54%. Light-fat meals (containing approximately 500 calories and 20 grams of fat) reduced AUC by 32% and C
maxby 42%.
Distribution
The blood-to-plasma ratio of everolimus, which is concentration-dependent over the range of 5 to 5,000 ng/mL, is 17% to 73%. The amount of everolimus confined to the plasma is approximately 20% at blood concentrations observed in cancer patients given everolimus tablets 10 mg orally once daily. Plasma protein binding is approximately 74% both in healthy subjects and in patients with moderate hepatic impairment.
Elimination
The mean elimination half-life of everolimus is approximately 30 hours.
Metabolism
Everolimus is a substrate of CYP3A4. Following oral administration, everolimus is the main circulating component in human blood. Six main metabolites of everolimus have been detected in human blood, including three monohydroxylated metabolites, two hydrolytic ring-opened products, and a phosphatidylcholine conjugate of everolimus. These metabolites were also identified in animal species used in toxicity studies and showed approximately 100-times less activity than everolimus itself.
Excretion
No specific elimination studies have been undertaken in cancer patients. Following the administration of a 3 mg single dose of radiolabeled everolimus in patients who were receiving cyclosporine, 80% of the radioactivity was recovered from the feces, while 5% was excreted in the urine. The parent substance was not detected in urine or feces.
Specific Populations
No relationship was apparent between oral clearance and age or sex in patients with cancer.
Patients with Renal Impairment
No significant influence of creatinine clearance (25 to 178 mL/min) was detected on oral clearance (CL/F) of everolimus.
Patients with Hepatic Impairment
Compared to normal subjects, there was a 1.8-fold, 3.2-fold, and 3.6-fold increase in AUC for subjects with mild (Child-Pugh class A), moderate (Child-Pugh class B), and severe (Child-Pugh class C) hepatic impairment, respectively. In another study, the average AUC of everolimus in subjects with moderate hepatic impairment (Child-Pugh class B) was twice that found in subjects with normal hepatic function
[see
Dosage and Administration (2.10),
Use in Specific Populations (8.6)]
.
Pediatric Patients
In patients with TSC-associated SEGA, the mean C
minvalues normalized to mg/m
2dose in pediatric patients (< 18 years of age) were lower than those observed in adults, suggesting that everolimus clearance adjusted to BSA was higher in pediatric patients as compared to adults.
Race or Ethnicity
Based on a cross-study comparison, Japanese patients had on average exposures that were higher than non-Japanese patients receiving the same dose. Oral clearance (CL/F) is on average 20% higher in black patients than in white patients.
Drug Interaction Studies
Effect of CYP3A4 and P-glycoprotein (P-gp) Inhibitors on Everolimus
Everolimus exposure increased when everolimus tablets were coadministered with:
- ketoconazole (a P-gp and strong CYP3A4 inhibitor) – C
maxand AUC increased by 3.9- and 15-fold, respectively.
- erythromycin (a P-gp and moderate CYP3A4 inhibitor) – C
maxand AUC increased by 2- and 4.4-fold, respectively.
- verapamil (a P-gp and moderate CYP3A4 inhibitor) – C
maxand AUC increased by 2.3- and 3.5-fold, respectively.
Effect of CYP3A4 and P-gp Inducers on Everolimus
The coadministration of everolimus tablets with rifampin, a P-gp and strong inducer of CYP3A4, decreased everolimus AUC by 63% and C
maxby 58% compared to everolimus tablets alone
[see
Dosage and Administration (2.12)]
.
Effect of Everolimus on CYP3A4 Substrates
No clinically significant pharmacokinetic interactions were observed between everolimus tablets and the HMG-CoA reductase inhibitors atorvastatin (a CYP3A4 substrate), pravastatin (a non-CYP3A4 substrate), and simvastatin (a CYP3A4 substrate).
The coadministration of an oral dose of midazolam (sensitive CYP3A4 substrate) with everolimus tablets resulted in a 25% increase in midazolam C
maxand a 30% increase in midazolam AUC
0–inf.
The coadministration of everolimus tablets with exemestane increased exemestane C
minby 45% and C2
hby 64%; however, the corresponding estradiol levels at steady state (4 weeks) were not different between the 2 treatment arms. No increase in adverse reactions related to exemestane was observed in patients with hormone receptor-positive, HER2-negative advanced breast cancer receiving the combination.
The coadministration of everolimus tablets with long-acting octreotide increased octreotide C
minby approximately 50%.
Effect of Everolimus on Antiepileptic Drugs (AEDs)
Everolimus increased pre-dose concentrations of the carbamazepine, clobazam, oxcarbazepine, and clobazam's metabolite N-desmethylclobazam by about 10%. Everolimus had no impact on pre-dose concentrations of AEDs that are substrates of CYP3A4 (e.g., clonazepam and zonisamide) or other AEDs, including valproic acid, topiramate, phenobarbital, and phenytoin.
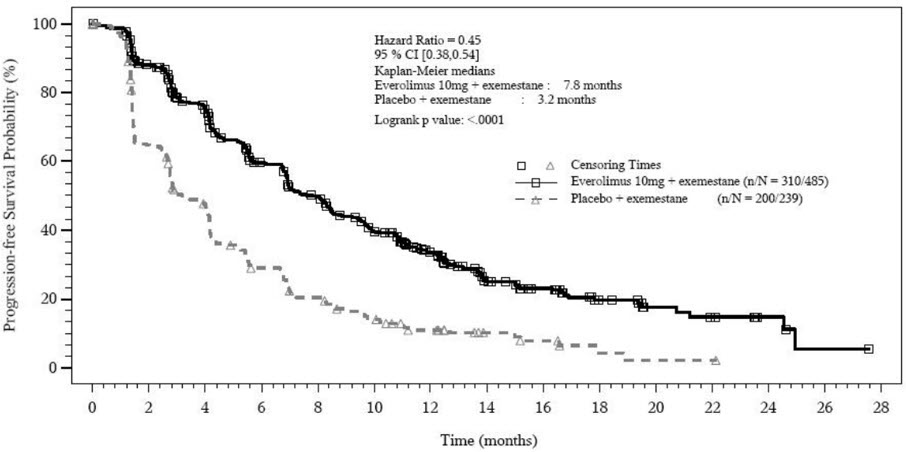
Table 20: Efficacy Results in Hormone-Receptor Positive, HER-2 Negative Breast Cancer in BOLERO-2| Analysis | Everolimus Tablets with Exemestane
N=485
| Placebo with Exemestane
N=239
| Hazard ratio | p-value |
|---|
| Median progression-free survival (months, 95% CI) |
| Investigator | 7.8 | 3.2 | 0.4
Hazard ratio is obtained from the stratified Cox proportional-hazards model by sensitivity to prior hormonal therapy and presence of visceral metastasis | <0.0001
p-value is obtained from the one-sided log-rank test stratified by sensitivity to prior hormonal therapy and presence of visceral metastasis |
| Radiological review | (6.9, 8.5) | (2.8, 4.1) | (0.38, 0.54) | |
| Independent | 11.0 | 4.1 | 0.38
| <0.0001
|
| Radiological review | (9.7, 15.0) | (2.9, 5.6) | (0.3, 0.5) | |
| Best overall response (%, 95 CI) |
| Objective response | 12.6% | 1.7% | n/a
Not applicable | |
| Rate (ORR)
Objective response rate = proportion of patients with CR or PR | (9.8, 15.9) | (0.5, 4.2) | | |
Figure 1: Kaplan-Meier Curves for Progression-Free Survival by Investigator Radiological Review in Hormone Receptor-Positive, HER-2 Negative Breast Cancer in BOLERO-2
EXIST-1
A randomized (2:1), double-blind, placebo-controlled trial (EXIST-1, NCT00789828) of everolimus tablets was conducted in 117 pediatric and adult patients with SEGA and TSC. Eligible patients had at least one SEGA lesion ≥ 1 cm in longest diameter on MRI based on local radiology assessment and one or more of the following: serial radiological evidence of SEGA growth, a new SEGA lesion ≥ 1 cm in longest diameter, or new or worsening hydrocephalus. Patients randomized to the treatment arm received everolimus tablets at a starting dose of 4.5 mg/m
2daily, with subsequent dose adjustments as needed to achieve and maintain everolimus trough concentrations of 5 to 15 ng/mL as tolerated. Everolimus tablets or matched placebo continued until disease progression or unacceptable toxicity. MRI scans for disease assessment were obtained at baseline, 12, 24, and 48 weeks, and annually thereafter.
The main efficacy outcome measure was SEGA response rate based on independent central radiology review. SEGA response was defined as a ≥ 50% reduction in the sum of SEGA volume relative to baseline, in the absence of unequivocal worsening of non-target SEGA lesions, a new SEGA lesion ≥ 1 cm, and new or worsening hydrocephalus. The primary analysis of SEGA response rate was limited to the blinded treatment period and conducted 6 months after the last patient was randomized. The analysis of SEGA response rate was stratified by use of enzyme-inducing antiepileptic drugs (EIAEDs) at randomization (yes vs. no).
Of the 117 patients enrolled, 78 were randomized to everolimus tablets and 39 to placebo. The median age was 9.5 years (0.8 to 26 years); a total of 20 patients were < 3 years, 54 patients were 3 to < 12 years, 27 patients were 12 to < 18 years, and 16 patients were ≥ 18 years; 57% were male, and 93% were white. At baseline, 18% of patients were receiving EIAEDs. Based on central radiology review at baseline, 98% of patients had at least one SEGA lesion ≥ 1.0 cm in longest diameter, 79% had bilateral SEGAs, 43% had ≥ 2 target SEGA lesions, 26% had growth in or into the inferior surface of the ventricle, 9% had evidence of growth beyond the subependymal tissue adjacent to the ventricle, and 7% had radiographic evidence of hydrocephalus. The median values for the sum of all target SEGA lesions at baseline were 1.63 cm
3(0.18 to 25.15 cm
3) and 1.30 cm
3(0.32 to 9.75 cm
3) in the everolimus tablets and placebo arms, respectively. Eight (7%) patients had prior SEGA-related surgery. The median duration of follow-up was 8.4 months (4.6 to 17.2 months) at the time of primary analysis.
The SEGA response rate was statistically significantly higher in everolimus tablets-treated patients (Table 25). At the time of the primary analysis, all SEGA responses were ongoing, and the median duration of response was 5.3 months (2.1 to 8.4 months).
With a median follow-up of 8.4 months, SEGA progression was detected in 15.4% of the 39 patients randomized to receive placebo and none of the 78 patients randomized to receive everolimus tablets. No patient in either treatment arm required surgical intervention.
Table 25: Subependymal Giant Cell Astrocytoma Response Rate in TSC-Associated SEGA in EXIST-1 | Everolimus Tablets
N = 78
| Placebo
N = 39
| p-value |
|---|
| Primary analysis | | | |
| SEGA response rate
Per independent central radiology review. - (%)
| 35 | 0 | < 0.0001 |
| 95% CI | 24, 46 | 0, 9 | |
Patients randomized to placebo were permitted to receive everolimus tablets at the time of SEGA progression or after the primary analysis, whichever occurred first. After the primary analysis, patients treated with everolimus tablets underwent additional follow-up MRI scans to assess tumor status until discontinuation of treatment or completion of 4 years of follow-up after the last patient was randomized. A total of 111 patients (78 patients randomized to everolimus tablets and 33 patients randomized to placebo) received at least one dose of everolimus tablets. Median duration of everolimus tablets treatment and follow-up was 3.9 years (0.2 to 4.9 years).
By four years after the last patient was enrolled, 58% of the 111 patients treated with everolimus tablets had a ≥ 50% reduction in SEGA volume relative to baseline, including 27 patients identified at the time of the primary analysis and 37 patients with a SEGA response after the primary analysis. The median time to SEGA response was 5.3 months (2.5 to 33.1 months). Twelve percent of the 111 patients treated with everolimus tablets had documented disease progression by the end of the follow-up period and no patient required surgical intervention for SEGA during the study.
Study 2485
Study 2485 (NCT00411619) was an open-label, single-arm trial conducted to evaluate the antitumor activity of everolimus tablets 3 mg/m
2/orally once daily in patients with SEGA and TSC. Serial radiological evidence of SEGA growth was required for entry. Tumor assessments were performed every 6 months for 60 months after the last patient was enrolled or disease progression, whichever occurred earlier. The major efficacy outcome measure was the reduction in volume of the largest SEGA lesion with 6 months of treatment, as assessed via independent central radiology review. Progression was defined as an increase in volume of the largest SEGA lesion over baseline that was ≥ 25% over the nadir observed on study.
A total of 28 patients received everolimus tablets for a median duration of 5.7 years (5 months to 6.9 years); 82% of the 28 patients remained on everolimus tablets for at least 5 years. The median age was 11 years (3 to 34 years), 61% male, 86% white.
At the primary analysis, 32% of the 28 patients (95% CI: 16%, 52%) had an objective response at 6 months, defined as at least a 50% decrease in volume of the largest SEGA lesion. At the completion of the study, the median duration of durable response was 12 months (3 months to 6.3 years).
By 60 months after the last patient was enrolled, 11% of the 28 patients had documented disease progression. No patient developed a new SEGA lesion while on everolimus tablets. Nine additional patients were identified as having a ≥ 50% volumetric reduction in their largest SEGA lesion between 1 to 4 years after initiating everolimus tablets, including 3 patients who had surgical resection with subsequent regrowth prior to receiving everolimus tablets.
Non-infectious Pneumonitis
Advise patients of the risk of developing non-infectious pneumonitis and to immediately report any new or worsening respiratory symptoms to their healthcare provider
[see
Warnings and Precautions (5.1)]
.
Infections
Advise patients that they are more susceptible to infections and that they should immediately report any signs or symptoms of infections to their healthcare provider
[see
Warnings and Precautions (5.2)]
.
Hypersensitivity Reactions
Advise patients of the risk of clinically significant hypersensitivity reactions and to promptly contact their healthcare provider or seek emergency care for signs of hypersensitivity reaction, including rash, itching, hives, difficulty breathing or swallowing, flushing, chest pain, or dizziness
[see
Contraindications (4),
Warnings and Precautions (5.3)]
.
Angioedema with Concomitant Use of ACE Inhibitors
Advise patients to avoid ACE inhibitors and to promptly contact their healthcare provider or seek emergency care for signs or symptoms of angioedema
[see
Warnings and Precautions (5.4)]
.
Stomatitis
Advise patients of the risk of stomatitis and to use alcohol-free mouthwashes during treatment
[see
Warnings and Precautions (5.5)]
.
Renal Impairment
Advise patients of the risk of developing kidney failure and the need to monitor their kidney function periodically during treatment
[see
Warnings and Precautions (5.6)]
.
Risk of Impaired Wound Healing
Advise patients that TORPENZ may impair wound healing. Advise patients to inform their healthcare provider of any planned surgical procedure
[see
Warnings and Precautions (5.7)]
.
Geriatric Patients
Inform patients that in a study conducted in patients with breast cancer, the incidence of deaths and adverse reactions leading to permanent discontinuation was higher in patients ≥ 65 years compared to patients < 65 years
[see
Warnings and Precautions (5.8),
Use in Specific Populations (8.5)].
Metabolic Disorders
Advise patients of the risk of metabolic disorders and the need to monitor glucose and lipids periodically during therapy
[see
Warnings and Precautions (5.9)]
.
Myelosuppression
Advise patients of the risk of myelosuppression and the need to monitor CBCs periodically during therapy
[see
Warnings and Precautions (5.10)]
.
Risk of Infection or Reduced Immune Response with Vaccination
Advise patients to avoid the use of live vaccines and close contact with those who have received live vaccines
[see
Warnings and Precautions (5.11)]
.
Embryo-Fetal Toxicity
Advise females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment and for 8 weeks after the last dose. Advise patients to inform their healthcare provider of a known or suspected pregnancy. Advise males with female partners of reproductive potential to use effective contraception during treatment and for 4 weeks after the last dose
[see
Warnings and Precautions (5.13),
Use in Specific Populations (8.1,
8.3)]
.
Radiation Sensitization and Radiation Recall
Radiation sensitization and recall can occur in patients treated with radiation prior to, during, or subsequent to TORPENZ treatment. Advise patients to inform their healthcare provider if they have had or are planning to receive radiation therapy
[see
Warnings and Precautions (5.12)]
.
Lactation
Advise women not to breastfeed during treatment with TORPENZ and for 2 weeks after the last dose
[see
Use in Specific Populations (8.2)]
.
Infertility
Advise males and females of reproductive potential of the potential risk for impaired fertility
[see
Use in Specific Populations (8.3)]
.
TORPENZ is a registered trademark of Upsher-Smith Laboratories, LLC,
All other trademarks are property of their respective owners.
Manufactured for
UPSHER-SMITH LABORATORIES, LLC
Maple Grove, MN 55369
Revised: 3/2026