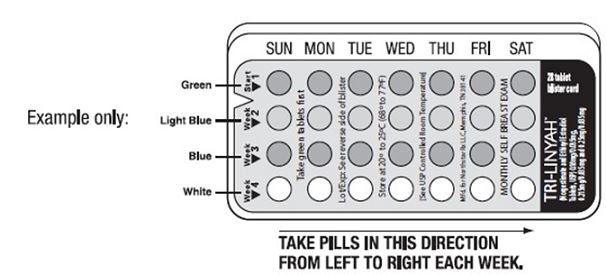
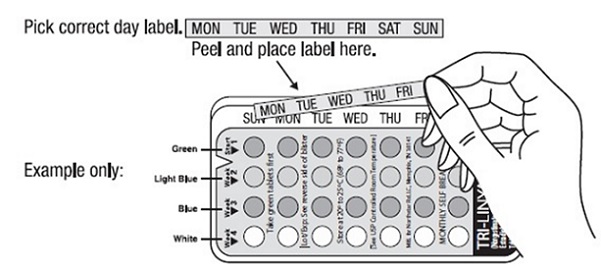
Tri-Linyah Tablets are available in blister cards. Each blister card contains 28 tablets in the following order:
- 7 green, round, biconvex, tablets imprinted “C1” on one side of the tablet and contains 0.180 mg norgestimate and 0.035 mg ethinyl estradiol
- 7 light blue, round, biconvex tablets imprinted “C2” on one side of the tablet and contains 0.215 mg norgestimate and 0.035 mg ethinyl estradiol
- 7 blue, round, biconvex tablets imprinted “C3” on one side of the tablet and contains 0.250 mg norgestimate and 0.035 mg ethinyl estradiol
- 7 white, round, biconvex tablets (non-hormonal placebo) imprinted “P” on one side and “N” on the other side contains inert ingredients
Impaired Liver Function
Do not use Tri-Linyah in women with liver disease, such as acute viral hepatitis or severe (decompensated) cirrhosis of liver [see Contraindications (4)]. Acute or chronic disturbances of liver function may necessitate the discontinuation of COC use until markers of liver function return to normal and COC causation has been excluded. Discontinue Tri-Linyah if jaundice develops.
Liver Tumors
Tri-Linyah is contraindicated in women with benign and malignant liver tumors [see Contraindications (4)]. Hepatic adenomas are associated with COC use. An estimate of the attributable risk is 3.3 cases/100,000 COC users. Rupture of hepatic adenomas may cause death through intra-abdominal hemorrhage.
Studies have shown an increased risk of developing hepatocellular carcinoma in long-term (>8 years) COC users. However, the risk of liver cancers in COC users is less than one case per million users.
Unscheduled Bleeding and Spotting
Unscheduled (breakthrough or intracyclic) bleeding and spotting sometimes occur in patients on COCs, especially during the first three months of use. If bleeding persists or occurs after previously regular cycles, check for causes such as pregnancy or malignancy. If pathology and pregnancy are excluded, bleeding irregularities may resolve over time or with a change to a different contraceptive product.
In clinical trials of norgestimate and ethinyl estradiol tricycle tablets, the frequency and duration of breakthrough bleeding and/or spotting was assessed in 1,647 patients (21,275 evaluable cycles) and 4,826 patients (35,546 evaluable cycles), respectively. A total of 231 (4.8%) women discontinued norgestimate and ethinyl estradiol tricycle tablets, at least in part, due to bleeding or spotting. Based on data from the clinical trials, 13-38% of women using norgestimate and ethinyl estradiol tricycle tablets experienced unscheduled bleeding per cycle in the first year. The percent of women who experienced breakthrough/unscheduled bleeding tended to decrease over time.
Amenorrhea and Oligomenorrhea
Women who use Tri-Linyah may experience amenorrhea. Some women may experience amenorrhea or oligomenorrhea after discontinuation of COCs, especially when such a condition was pre-existent.
If scheduled (withdrawal) bleeding does not occur, consider the possibility of pregnancy. If the patient has not adhered to the prescribed dosing schedule (missed one or more active tablets or started taking them on a day later than she should have), consider the possibility of pregnancy at the time of the first missed period and take appropriate diagnostic measures. If the patient has adhered to the prescribed regimen and misses two consecutive periods, rule out pregnancy.
Breast Cancer
Tri-Linyah is contraindicated in females who currently have or have had breast cancer because breast cancer may be hormonally sensitive [see Contraindications (4)].
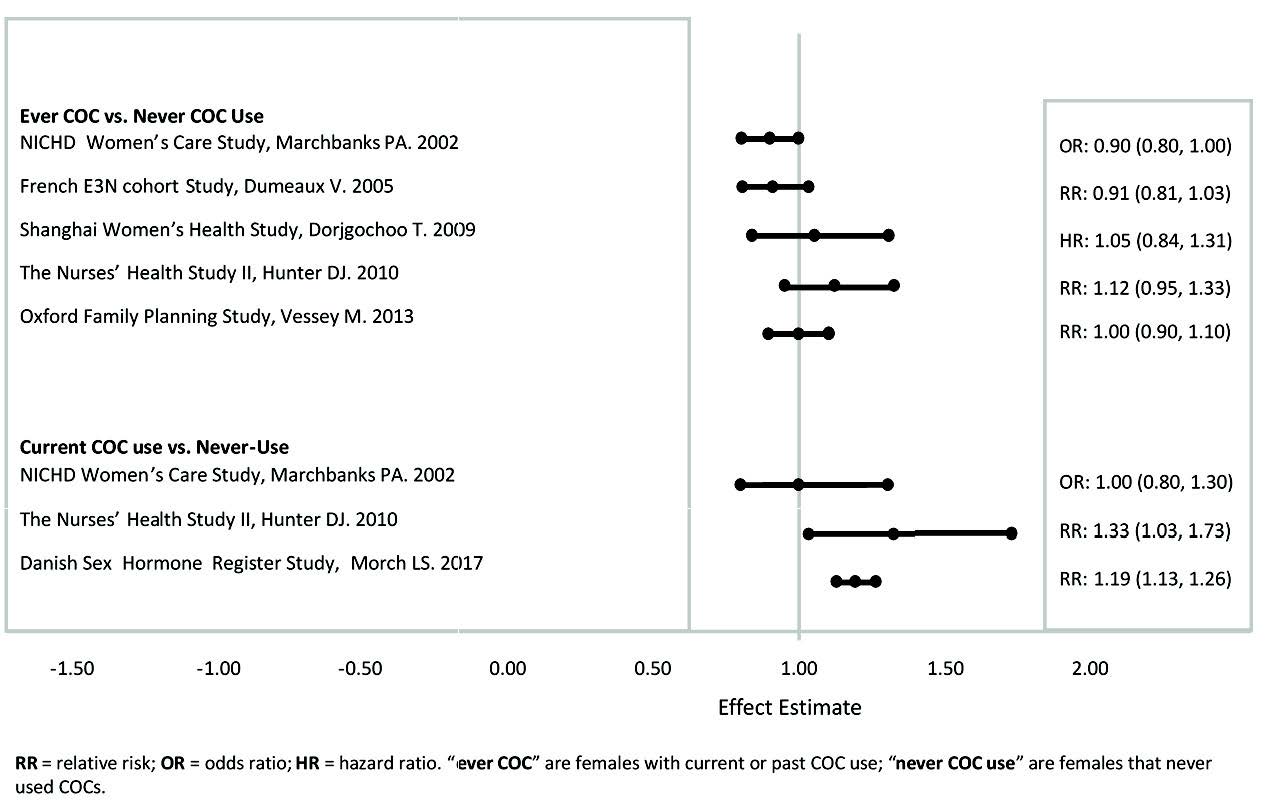
Epidemiology studies have not found a consistent association between use of combined oral contraceptives (COCs) and breast cancer risk. Studies do not show an association between ever (current or past) use of COCs and risk of breast cancer. However, some studies report a small increase in the risk of breast cancer among current or recent users (<6 months since last use) and current users with longer duration of COC use [see Postmarketing Experience (6.2)].
Cervical Cancer
Some studies suggest that COC use has been associated with an increase in the risk of cervical cancer or intraepithelial neoplasia. However, there continues to be controversy about the extent to which such fi ndings may be due to differences in sexual behavior and other factors.
The safety of tri-cycle norgestimate and ethinyl estradiol Tablets was evaluated in 4,826 healthy women of child-bearing potential who participated in 6 clinical trials and received at least 1 dose of tri-cycle norgestimate and ethinyl estradiol Tablets for contraception. Two trials were randomized active-controlled trials and 4 were uncontrolled open-label trials. In 3 trials, subjects were followed for up to 24 cycles; in 2 trials, subjects were followed for up to 12 cycles; and in 1 trial, subjects were followed for up to 6 cycles.
Common Adverse Reactions (≥ 2% of subjects): The most common adverse reactions reported by at least 2% of the 4,826 women were the following in order of decreasing incidence: headache/migraine (33.6%), breast issues (including breast pain, enlargement, and discharge) (8.0%), vaginal infection (7.1%), abdominal/gastrointestinal pain (5.6%), mood disorders (including mood alteration and depression) (3.8%), genital discharge (3.2%), and changes in weight (including weight fluctuation, increased or decreased) (2.5%).
Adverse Reactions Leading to Study Discontinuation: Over the trials, between 9 to 27% of subjects discontinued the trial due to an adverse reaction. The most common adverse reactions (≥1%) leading to discontinuation were: metrorrhagia (4.3%), nausea/vomiting (2.8%), headache/migraine (2.4%), mood disorders (including depression and mood altered) (1.1%), and weight increased (1.1%).
Serious Adverse Reactions: breast cancer (1 subject), carcinoma of the cervix in situ (1 subject), hypertension (1 subject), and migraine (2 subjects).
Substances decreasing the plasma concentrations of COCs
Drugs or herbal products that induce certain enzymes, including cytochrome P450 3A4 (CYP3A4), may decrease the plasma concentrations of COCs and potentially diminish the effectiveness of COCs or increase breakthrough bleeding. Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include phenytoin, barbiturates, carbamazepine, bosentan, felbamate, griseofulvin, oxcarbazepine, rifampicin, topiramate, rifabutin, rufinamide, aprepitant, and products containing St. John's wort. Interactions between hormonal contraceptives and other drugs may lead to breakthrough bleeding and/or contraceptive failure. Counsel women to use an alternative method of contraception or a back-up method when enzyme inducers are used with COCs, and to continue back-up contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability.
Colesevelam: Colesevelam, a bile acid sequestrant, given together with a COC, has been shown to significantly decrease the AUC of EE. The drug interaction between the contraceptive and colesevelam was decreased when the two drug products were given 4 hours apart.
Substances increasing the plasma concentrations of COCs
Co-administration of atorvastatin or rosuvastatin and certain COCs containing ethinyl estradiol (EE) increase AUC values for EE by approximately 20–25%. Ascorbic acid and acetaminophen may increase plasma EE concentrations, possibly by inhibition of conjugation. CYP3A4 inhibitors such as itraconazole, voriconazole, fluconazole, grapefruit juice, or ketoconazole may increase plasma hormone concentrations.
Human immunodeficiency virus (HIV)/Hepatitis C virus (HCV) protease inhibitors and non-nucleoside reverse transcriptase inhibitors
Significant changes (increase or decrease) in the plasma concentrations of estrogen and/or progestin have been noted in some cases of co-administration with HIV protease inhibitors (decrease [e.g., nelfinavir, ritonavir, darunavir/ritonavir, (fos)amprenavir/ritonavir, lopinavir/ritonavir, and tipranavir/ritonavir] or increase [e.g., indinavir and atazanavir/ritonavir])/HCV protease inhibitors (decrease [e.g., boceprevir and telaprevir]) or with non-nucleoside reverse transcriptase inhibitors (decrease [e.g., nevirapine] or increase [e.g., etravirine]).
- Each active green tablet contains 0.18 mg of norgestimate and 0.035 mg of ethinyl estradiol. Inactive ingredients include: FD&C Blue No.2 Aluminum Lake, FD&C Red No.40 Aluminum Lake, FD&C Yellow No. 10 Aluminum Lake, titanium dioxide, iron oxide black,iron oxide yellow, macrogol/ polyethylene glycol 3350 NF, lecithin, talc, polyvinyl alcohol,lactose monohydrate, magnesium stearate and pregelatinized corn starch.
- Each active light blue tablet contains 0.215 mg of norgestimate and 0.035 mg of ethinyl estradiol. Inactive ingredients include: FD&C Blue #2 Aluminum Lake, FD&C Red #40 Aluminum Lake, titanium dioxide, iron oxide black, polyvinyl alcohol, talc, macrogol/polyethylene glycol 3350 NF, lecithin, lactose monohydrate, magnesium stearate and pregelatinized corn starch.
- Each active blue tablet contains 0.25 mg of norgestimate and 0.035 mg of ethinyl estradiol. Inactive ingredients include: FD&C Blue No. 2 Aluminium Lake, FD&C Blue No. 1 Aluminum lake, FD&C Red No. 40 Aluminum Lake, FD&C Yellow No. 10 Aluminum Lake,titanium dioxide, polyvinyl alcohol, talc, macrogol/PEG 3350 NF, lecithin, lactose monohydrate, magnesium stearate and pregelatinized corn starch.
- Each white placebo tablet contains only inert ingredients, as follows: titanium dioxide, polydextrose, hypromellose, triacetin, macrogol/polyethylene glycol, lactose monohydrate, magnesium stearate and pregelatinized corn starch.
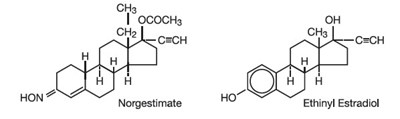
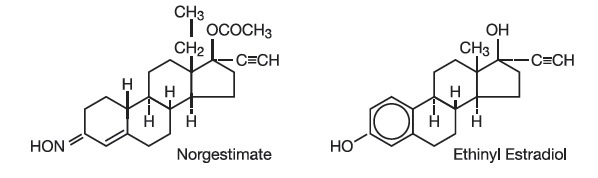
Chemical Structure (Structure)
Absorption
Norgestimate (NGM) and EE are rapidly absorbed following oral administration. NGM is rapidly and completely metabolized by first pass (intestinal and/or hepatic) mechanisms to norelgestromin (NGMN) and norgestrel (NG), which are the major active metabolites of norgestimate.
Peak serum concentrations of NGMN and EE are generally reached by 2 hours after administration of Tri-Linyah. Accumulation following multiple dosing of the 250 mcg NGM / 35 mcg EE dose is approximately 2-fold for NGMN and EE compared with single dose administration. The pharmacokinetics of NGMN is dose-proportional following NGM doses of 180 mcg to 250 mcg. Steady-state concentration of EE is achieved by Day 7 of each dosing cycle. Steady-state concentrations of NGMN and NG are achieved by Day 21. Non-linear accumulation (approximately 8 fold) of NG is observed as a result of high-affinity binding to SHBG, which limits its biological activity (Table 3).
Table 3: Summary of NGMN, NG and EE pharmacokinetic parameters.| Cmax = peak serum concentration, tmax = time to reach peak serum concentration, AUC0–24h = area under serum concentration vs time curve from 0 to 24 hours, t1/2 = elimination half-life, NC = not calculated. |
| NGMN and NG: Cmax = ng/mL, AUC0–24h = h∙ng/mL |
| EE: Cmax = pg/mL, AUC0–24h = h∙pg/mL |
| Mean (SD) Pharmacokinetic Parameters of Norgestimate/Ethinyl Estradiol tri-cyclic Tablets(0.18mg/0.035mg,0.215mg/0.035mg,0.25mg/0.035mg)During a Three Cycle Study |
| Analyte | Cycle | Day | Cmax | tmax (h) | AUC0–24h | t1/2 (h) |
| NGMN | 3 | 7 | 1.80 (0.46) | 1.42 (0.73) | 15.0 (3.88) | NC |
| | 14 | 2.12 (0.56) | 1.21 (0.26) | 16.1 (4.97) | NC |
| | 21 | 2.66 (0.47) | 1.29 (0.26) | 21.4 (3.46) | 22.3 (6.54) |
| NG | 3 | 7 | 1.94 (0.82) | 3.15 (4.05) | 34.8 (16.5) | NC |
| | 14 | 3.00 (1.04) | 2.21 (2.03) | 55.2 (23.5) | NC |
| | 21 | 3.66 (1.15) | 2.58 (2.97) | 69.3 (23.8) | 40.2 (15.4) |
| EE | 3 | 7 | 124 (39.5) | 1.27 (0.26) | 1130 (420) | NC |
| | 14 | 128 (38.4) | 1.32 (0.25) | 1130 (324) | NC |
| | 21 | 126 (34.7) | 1.31 (0.56) | 1090 (359) | 15.9 (4.39) |
Food Effect
The effect of food on the pharmacokinetics of Tri-Linyah has not been studied.
Distribution
NGMN and NG are highly bound (>97%) to serum proteins. NGMN is bound to albumin and not to SHBG, while NG is bound primarily to SHBG. EE is extensively bound (>97%) to serum albumin and induces an increase in the serum concentrations of SHBG.
Metabolism
NGM is extensively metabolized by first-pass mechanisms in the gastrointestinal tract and/or liver. NGM's primary active metabolite is NGMN. Subsequent hepatic metabolism of NGMN occurs and metabolites include NG, which is also active, and various hydroxylated and conjugated metabolites. Although NGMN and its metabolites inhibit a variety of P450 enzymes in human liver microsomes, under the recommended dosing regimen, the in vivo concentrations of NGMN and its metabolites, even at the peak serum levels, are relatively low compared to the inhibitory constant (Ki). EE is also metabolized to various hydroxylated products and their glucuronide and sulfate conjugates.
Excretion
The metabolites of NGMN and EE are eliminated by renal and fecal pathways. Following administration of 14C-norgestimate, 47% (45–49%) and 37% (16–49%) of the administered radioactivity was eliminated in the urine and feces, respectively. Unchanged NGM was not detected in the urine. In addition to 17-deacetyl norgestimate, a number of metabolites of NGM have been identified in human urine following administration of radiolabeled NGM. These include 18, 19-Dinor-17-pregn-4-en-20-yn-3-one,17-hydroxy-13-ethyl,(17α)-(-);18,19-Dinor-5β-17-pregnan-20-yn,3α,17β-dihydroxy-13-ethyl,(17α), various hydroxylated metabolites and conjugates of these metabolites.
Tri-Linyah Tablets are available in a compact blister card (NDC 16714-363-01).
Each blister card (28 tablets) contains in the following order:
- 7 green, round, biconvex, tablets imprinted “C1” on one side of the tablet and contains 0.180 mg norgestimate and 0.035 mg ethinyl estradiol
- 7 light blue, round, biconvex tablets imprinted “C2” on one side of the tablet and contains 0.215 mg norgestimate and 0.035 mg ethinyl estradiol
- 7 blue, round, biconvex tablets imprinted “C3” on one side of the tablet and contains 0.250 mg norgestimate and 0.035 mg ethinyl estradiol
- 7 white, round, biconvex tablets (non-hormonal placebo) imprinted “P” on one side and “N” on the other side contains inert ingredients
Tri-Linyah is available in the following packaging configurations:
Carton of 1 blister card NDC 16714-363-02
Carton of 3 blister cards NDC 16714-363-03
Carton of 6 blister cards NDC 16714-363-04

Northstar Logo (Northstar)
Manufactured for: Northstar Rx LLC
Memphis TN 38141
Toll Free 1-800-206-7821
Manufactured by : Novast Laboratories Ltd.
Nantong,China 226009
Northstar Logo (Northstar)
Manufactured for: Northstar Rx LLC
Memphis TN 38141
Toll Free 1-800-206-7821
Manufactured by: Novast Laboratories Ltd.
Nantong,China 226009
This Patient Information and Instructions for Use has been approved by the U.S. Food and Drug Administration.
Revised: Sep 2022 I0061 Rev.C