Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice.
During clinical development for the approved indications, 34,947 adult patients were exposed to XARELTO.
Hemorrhage
The most common adverse reactions with XARELTO were bleeding complications [see Warnings and Precautions (5.2)].
Nonvalvular Atrial Fibrillation
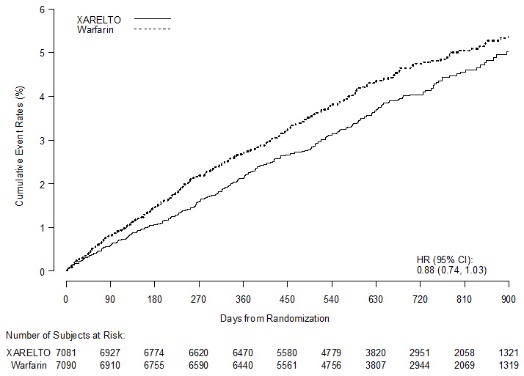
In the ROCKET AF trial, the most frequent adverse reactions associated with permanent drug discontinuation were bleeding events, with incidence rates of 4.3% for XARELTO vs. 3.1% for warfarin. The incidence of discontinuations for non-bleeding adverse events was similar in both treatment groups.
Table 5 shows the number of patients experiencing various types of bleeding events in the ROCKET AF trial.
Table 5: Bleeding Events in ROCKET AFMajor bleeding events within each subcategory were counted once per patient, but patients may have contributed events to multiple subcategories. These events occurred during treatment or within 2 days of stopping treatment.
- On Treatment Plus 2 Days| Parameter | XARELTO
N=7111
n (%/year) | Warfarin
N=7125
n (%/year) | XARELTO vs. Warfarin
HR
(95% CI) |
|---|
| Abbreviations: HR = Hazard Ratio, CI = Confidence interval, CRNM = Clinically Relevant Non-Major. |
Major Bleeding Defined as clinically overt bleeding associated with a decrease in hemoglobin of ≥2 g/dL, a transfusion of ≥2 units of packed red blood cells or whole blood, bleeding at a critical site, or with a fatal outcome. | 395 (3.6) | 386 (3.5) | 1.04 (0.90, 1.20) |
Intracranial Hemorrhage (ICH) Intracranial bleeding events included intraparenchymal, intraventricular, subdural, subarachnoid and/or epidural hematoma. | 55 (0.5) | 84 (0.7) | 0.67 (0.47, 0.93) |
Hemorrhagic Stroke Hemorrhagic stroke in this table specifically refers to non-traumatic intraparenchymal and/or intraventricular hematoma in patients on treatment plus 2 days. | 36 (0.3) | 58 (0.5) | 0.63 (0.42, 0.96) |
Other ICH | 19 (0.2) | 26 (0.2) | 0.74 (0.41, 1.34) |
Gastrointestinal (GI) Gastrointestinal bleeding events included upper GI, lower GI, and rectal bleeding. | 221 (2.0) | 140 (1.2) | 1.61 (1.30, 1.99) |
Fatal Bleeding Fatal bleeding is adjudicated death with the primary cause of death from bleeding. | 27 (0.2) | 55 (0.5) | 0.50 (0.31, 0.79) |
ICH | 24 (0.2) | 42 (0.4) | 0.58 (0.35, 0.96) |
Non-intracranial | 3 (0.0) | 13 (0.1) | 0.23 (0.07, 0.82) |
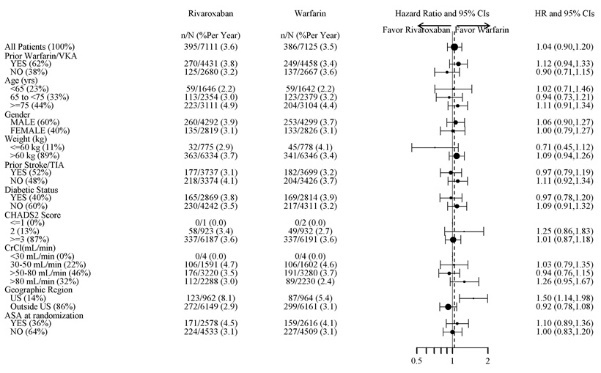
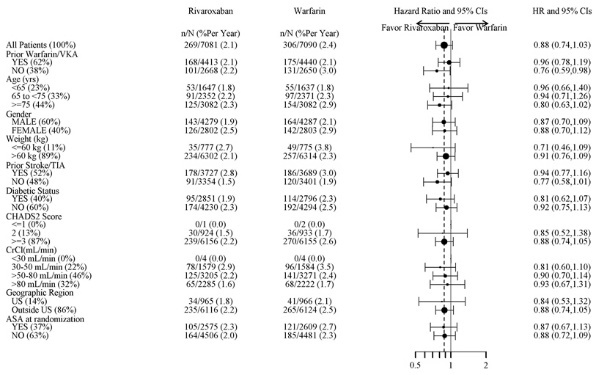
Figure 1 shows the risk of major bleeding events across major subgroups.
| Note: The figure above presents effects in various subgroups all of which are baseline characteristics and all of which were pre-specified (diabetic status was not pre-specified in the subgroup but was a criterion for the CHADS2 score). The 95% confidence limits that are shown do not take into account how many comparisons were made, nor do they reflect the effect of a particular factor after adjustment for all other factors. Apparent homogeneity or heterogeneity among groups should not be over-interpreted. |
Figure 1: Risk of Major Bleeding Events by Baseline Characteristics in ROCKET AF – On Treatment Plus 2 Days |
|
Treatment of Deep Vein Thrombosis (DVT) and/or Pulmonary Embolism (PE)
EINSTEIN DVT and EINSTEIN PE Studies
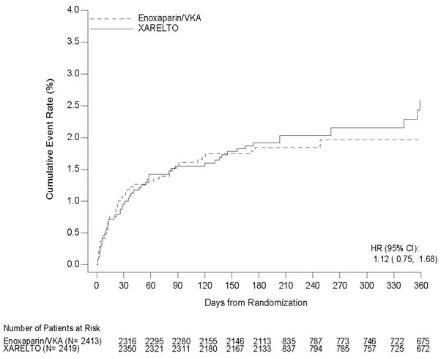
In the pooled analysis of the EINSTEIN DVT and EINSTEIN PE clinical studies, the most frequent adverse reactions leading to permanent drug discontinuation were bleeding events, with XARELTO vs. enoxaparin/Vitamin K antagonist (VKA) incidence rates of 1.7% vs. 1.5%, respectively. The mean duration of treatment was 208 days for XARELTO-treated patients and 204 days for enoxaparin/VKA-treated patients.
Table 6 shows the number of patients experiencing major bleeding events in the pooled analysis of the EINSTEIN DVT and EINSTEIN PE studies.
Table 6: Bleeding EventsBleeding event occurred after randomization and up to 2 days after the last dose of study drug. Although a patient may have had 2 or more events, the patient is counted only once in a category.
in the Pooled Analysis of EINSTEIN DVT and EINSTEIN PE Studies| Parameter | XARELTO
N=4130
n (%) | Enoxaparin/VKA
N=4116
n (%) |
|---|
Major bleeding event | 40 (1.0) | 72 (1.7) |
Fatal bleeding | 3 (<0.1) | 8 (0.2) |
Intracranial | 2 (<0.1) | 4 (<0.1) |
Non-fatal critical organ bleeding | 10 (0.2) | 29 (0.7) |
Intracranial | 3 (<0.1) | 10 (0.2) |
Retroperitoneal | 1 (<0.1) | 8 (0.2) |
Intraocular | 3 (<0.1) | 2 (<0.1) |
Intra-articular | 0 | 4 (<0.1) |
Non-fatal non-critical organ bleeding Major bleeding which is not fatal or in a critical organ, but resulting in a decrease in Hb ≥ 2 g/dL and/or transfusion of ≥2 units of whole blood or packed red blood cells | 27 (0.7) | 37 (0.9) |
Decrease in Hb ≥ 2 g/dL | 28 (0.7) | 42 (1.0) |
Transfusion of ≥2 units of whole blood or packed red blood cells | 18 (0.4) | 25 (0.6) |
Clinically relevant non-major bleeding | 357 (8.6) | 357 (8.7) |
Any bleeding | 1169 (28.3) | 1153 (28.0) |
Reduction in the Risk of Recurrence of DVT and/or PE
EINSTEIN CHOICE Study
In the EINSTEIN CHOICE clinical study, the most frequent adverse reactions associated with permanent drug discontinuation were bleeding events, with incidence rates of 1% for XARELTO 10 mg, 2% for XARELTO 20 mg, and 1% for acetylsalicylic acid (aspirin) 100 mg. The mean duration of treatment was 293 days for XARELTO 10 mg-treated patients and 286 days for aspirin 100 mg-treated patients.
Table 7 shows the number of patients experiencing bleeding events in the EINSTEIN CHOICE study.
Table 7: Bleeding EventsBleeding event occurred after the first dose and up to 2 days after the last dose of study drug. Although a patient may have had 2 or more events, the patient is counted only once in a category.
in EINSTEIN CHOICE| Parameter | XARELTO
10 mg
N=1127
n (%) | Acetylsalicylic Acid (aspirin) 100 mg
N=1131
n (%) |
|---|
Major bleeding event | 5 (0.4) | 3 (0.3) |
Fatal bleeding | 0 | 1 (<0.1) |
Non-fatal critical organ bleeding | 2 (0.2) | 1 (<0.1) |
Non-fatal non-critical organ bleeding Major bleeding which is not fatal or in a critical organ, but resulting in a decrease in Hb ≥ 2 g/dL and/or transfusion of ≥ 2 units of whole blood or packed red blood cells. | 3 (0.3) | 1 (<0.1) |
Clinically relevant non-major (CRNM) bleeding Bleeding which was clinically overt, did not meet the criteria for major bleeding, but was associated with medical intervention, unscheduled contact with a physician, temporary cessation of treatment, discomfort for the patient, or impairment of activities of daily life. | 22 (2.0) | 20 (1.8) |
Any bleeding | 151 (13.4) | 138 (12.2) |
In the EINSTEIN CHOICE study, there was an increased incidence of bleeding, including major and CRNM bleeding in the XARELTO 20 mg group compared to the XARELTO 10 mg or aspirin 100 mg groups.
Prophylaxis of Deep Vein Thrombosis Following Hip or Knee Replacement Surgery
In the RECORD clinical trials, the overall incidence rate of adverse reactions leading to permanent treatment discontinuation was 3.7% with XARELTO.
The rates of major bleeding events and any bleeding events observed in patients in the RECORD clinical trials are shown in Table 8.
Table 8: Bleeding EventsBleeding events occurring any time following the first dose of double-blind study medication (which may have been prior to administration of active drug) until two days after the last dose of double-blind study medication. Patients may have more than one event.
in Patients Undergoing Hip or Knee Replacement Surgeries (RECORD 1–3) | XARELTO 10 mg | Enoxaparin Includes the placebo-controlled period for RECORD 2, enoxaparin dosing was 40 mg once daily (RECORD 1–3) |
|---|
Total treated patients | N=4487
n (%) | N=4524
n (%) |
Major bleeding event | 14 (0.3) | 9 (0.2) |
Fatal bleeding | 1 (<0.1) | 0 |
Bleeding into a critical organ | 2 (<0.1) | 3 (0.1) |
Bleeding that required re-operation | 7 (0.2) | 5 (0.1) |
Extra-surgical site bleeding requiring transfusion of >2 units of whole blood or packed cells | 4 (0.1) | 1 (<0.1) |
Any bleeding event | 261 (5.8) | 251 (5.6) |
Hip Surgery Studies | N=3281
n (%) | N=3298
n (%) |
Major bleeding event | 7 (0.2) | 3 (0.1) |
Fatal bleeding | 1 (<0.1) | 0 |
Bleeding into a critical organ | 1 (<0.1) | 1 (<0.1) |
Bleeding that required re-operation | 2 (0.1) | 1 (<0.1) |
Extra-surgical site bleeding requiring transfusion of >2 units of whole blood or packed cells | 3 (0.1) | 1 (<0.1) |
Any bleeding event | 201 (6.1) | 191 (5.8) |
Knee Surgery Study | N=1206
n (%) | N=1226
n (%) |
Major bleeding event | 7 (0.6) | 6 (0.5) |
Fatal bleeding | 0 | 0 |
Bleeding into a critical organ | 1 (0.1) | 2 (0.2) |
Bleeding that required re-operation | 5 (0.4) | 4 (0.3) |
Extra-surgical site bleeding requiring transfusion of >2 units of whole blood or packed cells | 1 (0.1) | 0 |
Any bleeding event | 60 (5.0) | 60 (4.9) |
Following XARELTO treatment, the majority of major bleeding complications (≥60%) occurred during the first week after surgery.
Prophylaxis of Venous Thromboembolism in Acutely Ill Medical Patients at Risk for Thromboembolic Complications Not at High Risk of Bleeding
In the MAGELLAN study, the most frequent adverse reactions associated with permanent drug discontinuation were bleeding events. Cases of pulmonary hemorrhage and pulmonary hemorrhage with bronchiectasis were observed. Patients with bronchiectasis/pulmonary cavitation, active cancer (i.e., undergoing acute, in-hospital cancer treatment), dual antiplatelet therapy or active gastroduodenal ulcer or any bleeding in the previous three months all had an excess of bleeding with XARELTO compared with enoxaparin/placebo and are excluded from all MAGELLAN data presented in Table 9. The incidence of bleeding leading to drug discontinuation was 2.5% for XARELTO vs. 1.4% for enoxaparin/placebo.
Table 9 shows the number of patients experiencing various types of bleeding events in the MAGELLAN study.
Table 9: Bleeding Events in MAGELLANPatients at high risk of bleeding (i.e. bronchiectasis/pulmonary cavitation, active cancer, dual antiplatelet therapy or active gastroduodenal ulcer or any bleeding in the previous three months) were excluded.
Study–Safety Analysis Set - On Treatment Plus 2 Days| MAGELLAN Study Patients received either XARELTO or placebo once daily for 35 ±4 days starting in hospital and continuing post hospital discharge or received enoxaparin or placebo once daily for 10 ±4 days in the hospital. | XARELTO 10 mg
N=3218
n (%) | Enoxaparin 40 mg /placebo
N=3229
n (%) |
|---|
Major bleeding Defined as clinically overt bleeding associated with a drop in hemoglobin of ≥2 g/dL, a transfusion of ≥2 units of packed red blood cells or whole blood, bleeding at a critical site, or with a fatal outcome. Major bleeding events within each subcategory were counted once per patient, but patients may have contributed events to multiple subcategories. These events occurred during treatment or within 2 days of stopping treatment. | 22 (0.7) | 15 (0.5) |
Critical site bleeding | 7 (0.2) | 4 (0.1) |
Fatal bleeding Fatal bleeding is adjudicated death with the primary cause of death from bleeding. | 3 (<0.1) | 1 (<0.1) |
Clinically relevant non-major bleeding events (CRNM) | 93 (2.9) | 34 (1.1) |
Reduction of Risk of Major Cardiovascular Events in Patients with CAD
In the COMPASS trial overall, the most frequent adverse reactions associated with permanent drug discontinuation were bleeding events, with incidence rates of 2.7% for XARELTO 2.5 mg twice daily vs. 1.2% for placebo on background therapy for all patients with aspirin 100 mg once daily. The incidences of important bleeding events in the CAD and PAD populations in COMPASS were similar.
Table 10 shows the number of patients experiencing various types of major bleeding events in the COMPASS trial.
Table 10: Major Bleeding Events in COMPASS - On Treatment Plus 2 DaysMajor bleeding events within each subcategory were counted once per patient, but patients may have contributed events to multiple subcategories. These events occurred during treatment or within 2 days of stopping treatment in the safety analysis set in COMPASS patients.
| Parameter | XARELTO
N=9134
n (%/year) | Placebo
N=9107
n (%/year) | XARELTO vs. Placebo
HR (95 % CI) |
|---|
| CI: confidence interval; HR: hazard ratio; ISTH: International Society on Thrombosis and Hemostasis |
Modified ISTH Major Bleeding Defined as i) fatal bleeding, or ii) symptomatic bleeding in a critical area or organ, such as intraarticular, intramuscular with compartment syndrome, intraspinal, intracranial, intraocular, respiratory, pericardial, liver, pancreas, retroperitoneal, adrenal gland or kidney; or iii) bleeding into the surgical site requiring reoperation, or iv) bleeding leading to hospitalization. | 263 (1.6) | 144 (0.9) | 1.8 (1.5, 2.3) |
- Fatal bleeding event
Intracranial hemorrhage (ICH)
Non-intracranial | 12 (<0.1)
6 (<0.1)
6 (<0.1) | 8 (<0.1)
3 (<0.1)
5 (<0.1) | 1.5 (0.6, 3.7)
2.0 (0.5, 8.0)
1.2 (0.4, 4.0) |
- Symptomatic bleeding in critical organ (non-fatal)
- ICH (fatal and non-fatal)
Hemorrhagic Stroke
Other ICH | 58 (0.3)
23 (0.1)
18 (0.1)
6 (<0.1) | 43 (0.3)
21 (0.1)
13 (<0.1)
9 (<0.1) | 1.4 (0.9, 2.0)
1.1 (0.6, 2.0)
1.4 (0.7, 2.8)
0.7 (0.2, 1.9) |
- Bleeding into the surgical site requiring reoperation (non-fatal, not in critical organ) | 7 (<0.1) | 6 (<0.1) | 1.2 (0.4, 3.5) |
- Bleeding leading to hospitalization (non-fatal, not in critical organ, not requiring reoperation) | 188 (1.1) | 91 (0.5) | 2.1 (1.6, 2.7) |
Major GI bleeding | 117 (0.7) | 49 (0.3) | 2.4 (1.7, 3.4) |
Reduction of Risk of Major Thrombotic Vascular Events in Patients with Peripheral Artery Disease (PAD), Including Patients after Lower Extremity Revascularization due to Symptomatic PAD
The incidence of premature permanent discontinuation due to bleeding events for XARELTO 2.5 mg twice daily vs. placebo on background therapy with aspirin 100 mg once daily in VOYAGER was 4.1% vs. 1.6% and in COMPASS PAD was 2.7% vs. 1.3%, respectively.
Table 11 shows the number of patients experiencing various types of TIMI (Thrombolysis in Myocardial Infarction) major bleeding events in the VOYAGER trial. The most common site of bleeding was gastrointestinal.
Table 11: Major Bleeding EventsMajor bleeding events within each subcategory were counted once per patient, but patients may have contributed events to multiple subcategories.
in VOYAGER- On Treatment Plus 2 Days | XARELTO
N=3256 | Placebo
N=3248 | XARELTO vs. Placebo
HR (95 % CI) |
|---|
| Parameter | n (%) | Event rate
%/year | n (%) | Event rate
%/year |
|---|
| CABG: Coronary artery bypass graft; CI: confidence interval; HR: hazard ratio; TIMI: Thrombolysis in Myocardial Infarction Bleeding Criteria |
TIMI Major Bleeding
(CABG/non-CABG) | 62 (1.9) | 0.96 | 44 (1.4) | 0.67 | 1.4 (1.0, 2.1) |
Fatal bleeding | 6 (0.2) | 0.09 | 6 (0.2) | 0.09 | 1.0 (0.3, 3.2) |
Intracranial bleeding | 13 (0.4) | 0.20 | 17 (0.5) | 0.26 | 0.8 (0.4, 1.6) |
Clinically overt signs of hemorrhage associated with a drop in hemoglobin of ≥5 g/dL or drop in hematocrit of ≥15% | 46 (1.4) | 0.71 | 24 (0.7) | 0.36 | 1.9 (1.2, 3.2) |
Other Adverse Reactions
Non-hemorrhagic adverse reactions reported in ≥1% of XARELTO-treated patients in the EINSTEIN DVT and EINSTEIN PE studies are shown in Table 12.
Table 12: Other Adverse ReactionsAdverse reaction with Relative Risk >1.5 for XARELTO versus comparator
Reported by ≥1% of XARELTO-Treated Patients in EINSTEIN DVT and EINSTEIN PE StudiesBody System
Adverse Reaction | | |
|---|
EINSTEIN DVT Study | XARELTO 20 mg
N=1718
n (%) | Enoxaparin/VKA
N=1711
n (%) |
Gastrointestinal disorders | | |
Abdominal pain | 46 (2.7) | 25 (1.5) |
General disorders and administration site conditions | | |
Fatigue | 24 (1.4) | 15 (0.9) |
Musculoskeletal and connective tissue disorders | | |
Back pain | 50 (2.9) | 31 (1.8) |
Muscle spasm | 23 (1.3) | 13 (0.8) |
Nervous system disorders | | |
Dizziness | 38 (2.2) | 22 (1.3) |
Psychiatric disorders | | |
Anxiety | 24 (1.4) | 11 (0.6) |
Depression | 20 (1.2) | 10 (0.6) |
Insomnia | 28 (1.6) | 18 (1.1) |
EINSTEIN PE Study | XARELTO 20 mg
N=2412
n (%) | Enoxaparin/VKA
N=2405
n (%) |
Skin and subcutaneous tissue disorders | | |
Pruritus | 53 (2.2) | 27 (1.1) |
Non-hemorrhagic adverse reactions reported in ≥1% of XARELTO-treated patients in RECORD 1–3 studies are shown in Table 13.
Table 13: Other Adverse Drug ReactionsAdverse reaction occurring any time following the first dose of double-blind medication, which may have been prior to administration of active drug, until two days after the last dose of double-blind study medication
Reported by ≥1% of XARELTO-Treated Patients in RECORD 1–3 StudiesBody System
Adverse Reaction | XARELTO
10 mg
N=4487
n (%) | Enoxaparin Includes the placebo-controlled period of RECORD 2, enoxaparin dosing was 40 mg once daily (RECORD 1–3)
N=4524
n (%) |
|---|
Injury, poisoning and procedural complications | | |
Wound secretion | 125 (2.8) | 89 (2.0) |
Musculoskeletal and connective tissue disorders | | |
Pain in extremity | 74 (1.7) | 55 (1.2) |
Muscle spasm | 52 (1.2) | 32 (0.7) |
Nervous system disorders | | |
Syncope | 55 (1.2) | 32 (0.7) |
Skin and subcutaneous tissue disorders | | |
Pruritus | 96 (2.1) | 79 (1.8) |
Blister | 63 (1.4) | 40 (0.9) |
Pediatric Patients
Treatment of Venous Thromboembolism and Reduction in Risk of Recurrent Venous Thromboembolism in Pediatric Patients
The safety assessment is based on data from the EINSTEIN Junior Phase 3 study in 491 patients from birth to less than 18 years of age. Patients were randomized 2:1 to receive body weight-adjusted doses of XARELTO or comparator (unfractionated heparin, low molecular weight heparin, fondaparinux or VKA).
Discontinuation due to bleeding events occurred in 6 (1.8%) patients in the XARELTO group and 3 (1.9%) patients in the comparator group.
Table 14 shows the number of patients experiencing bleeding events in the EINSTEIN Junior study. In female patients who had experienced menarche, ages 12 to <18 years of age, menorrhagia occurred in 23 (27%) female patients in the XARELTO group and 5 (10%) female patients in the comparator group.
Table 14: Bleeding Events in EINSTEIN Junior Study – Safety Analysis Set - Main Treatment PeriodThese events occurred after randomization until 3 months of treatment (1 month for patients <2 years with central venous catheter-related VTE (CVC-VTE). Patients may have more than one event.
| Parameter | XARELTO Treatment schedule: body weight-adjusted doses of XARELTO; randomized 2:1 (XARELTO: Comparator).
N=329
n (%) | Comparator Group Unfractionated heparin (UFH), low molecular weight heparin (LMWH), fondaparinux or VKA.
N=162
n (%) |
|---|
Major bleeding Defined as clinically overt bleeding associated with a decrease in hemoglobin of ≥2 g/dL, a transfusion of ≥2 units of packed red blood cells or whole blood, bleeding at a critical site, or with a fatal outcome. | 0 | 2 (1.2) |
Clinically relevant non-major bleeding Defined as clinically overt bleeding, which did not meet the criteria for major bleeding, but was associated with medical intervention, unscheduled contact with a physician, temporary cessation of treatment, discomfort for the patient, or impairment of activities of daily life. | 10 (3.0) | 1 (0.6) |
Trivial bleeding | 113 (34.3) | 44 (27.2) |
Any bleeding | 119 (36.2) | 45 (27.8) |
Non-bleeding adverse reactions reported in ≥5% of XARELTO-treated patients are shown in Table 15.
Table 15: Other Adverse ReactionsAdverse reaction with Relative Risk >1.5 for XARELTO versus comparator.
Reported in XARELTO-Treated Patients by ≥5% in EINSTEIN Junior Study| Adverse Reaction | XARELTO
N=329
n (%) | Comparator Group
N=162
n (%) |
|---|
Pain in extremity | 23 (7) | 7 (4.3) |
Fatigue The following terms were combined: fatigue, asthenia. | 23 (7) | 7 (4.3) |
A clinically relevant adverse reaction in XARELTO-treated patients was vomiting (10.6% in the XARELTO group vs 8% in the comparator group).
Thromboprophylaxis in Pediatric Patients with Congenital Heart Disease (CHD) after the Fontan Procedure
The data below are based on Part B of the UNIVERSE study which was designed to evaluate the safety and efficacy of XARELTO for thromboprophylaxis in 98 children with CHD after the Fontan procedure who took at least one dose of study drug. Patients in Part B were randomized 2:1 to receive either body weight-adjusted doses of XARELTO or aspirin (approximately 5 mg/kg).
Discontinuation due to bleeding events occurred in 1 (1.6%) patient in the XARELTO group and no patients in the aspirin group.
Table 16 shows the number of patients experiencing bleeding events in the UNIVERSE study.
Table 16: Bleeding Events in UNIVERSE Study - Safety Analysis Set - On Treatment Plus 2 Days| Parameter | XARELTO Treatment schedule: body weight-adjusted doses of XARELTO or aspirin (approximately 5 mg/kg); randomized 2:1 (XARELTO: Aspirin).
N=64
n (%) | Aspirin
N=34
n (%) |
|---|
Major Bleeding Defined as clinically overt bleeding associated with a decrease in hemoglobin of ≥2 g/dL, a transfusion of the equivalent of ≥2 units of packed red blood cells or whole blood, bleeding at a critical site, or with a fatal outcome. | 1 (1.6) | 0 |
Epistaxis leading to transfusion | 1 (1.6) | 0 |
Clinically relevant non-major (CRNM) bleeding Defined as clinically overt bleeding, which did not meet the criteria for major bleeding, but was associated with medical intervention, unscheduled contact with a physician, temporary cessation of treatment, discomfort for the patient, or impairment of activities of daily life. | 4 (6.3) | 3 (8.8) |
Trivial bleeding | 21 (32.8) | 12 (35.3) |
Any bleeding | 23 (35.9) | 14 (41.2) |
Non-bleeding adverse reactions reported in ≥5% of XARELTO-treated patients are shown in Table 17.
Table 17: Other Adverse ReactionsAdverse reaction with Relative Risk >1.5 for XARELTO versus aspirin.
Reported by ≥5% of XARELTO-Treated Patients in UNIVERSE Study (Part B)| Adverse Reaction | XARELTO
N=64
n (%) | Aspirin
N=34
n (%) |
|---|
Cough | 10 (15.6) | 3 (8.8) |
Vomiting | 9 (14.1) | 3 (8.8) |
Gastroenteritis The following terms were combined:
Gastroenteritis: gastroenteritis, gastroenteritis viral
Rash: rash, rash maculo-papular, viral rash | 8 (12.5) | 1 (2.9) |
Rash | 6 (9.4) | 2 (5.9) |