- If the reconstituted XENPOZYME vials are not used immediately, store refrigerated at 2°C to 8°C (36°F to 46°F) for up to 24 hours or at controlled room temperature at 20°C to 25°C (68°F to 77°F) for up to 6 hours. Discard the unused XENPOZYME reconstituted solution after 24 hours if stored refrigerated or 6 hours if stored at controlled room temperature.
- If the diluted solution is not used immediately, refrigerate the diluted solution at 2°C to 8°C (36°F to 46°F) for up to 24 hours or store at room temperature at 20°C to 25°C (68°F to 77°F) for up to 12 hours (inclusive of infusion time), or discard.
- Do not freeze.
Table 4: XENPOZYME Infusion Volumes for Pediatric and Adult Patients Based on Body WeightUse actual or adjusted body weight per patient BMI. Refer to section 2. [see Dosage and Administration (2.2, 2.3)].
| Pediatric Patients (0 to 17 years) | Adult patients (18 years and older) |
|---|
| Body Weight
≥2 kg and <10 kg | Body Weight
≥10 kg and <20 kg | Body Weight
≥20 kg | Body Weight
≥20 kg |
|---|
| XENPOZYME Dose | Total Infusion Volume |
|---|
| 0.03 mg/kg | Actual volume will vary Volume will vary to achieve a final concentration of 0.1 mg/mL
(0.6 mL to 3 mL) | Actual volume will vary
(3 mL to 6 mL) | 5 mL | NA |
| 0.1 mg/kg | Actual volume will vary
(2 mL to 10 mL) | 5 mL | 10 mL | 20 mL |
| 0.3 mg/kg | 5 mL | 10 mL | 20 mL | 100 mL |
| 0.6 mg/kg | 10 mL | 20 mL | 50 mL | 100 mL |
| 1 mg/kg | 20 mL | 50 mL | 100 mL | 100 mL |
| 2 mg/kg | 50 mL | 75 mL | 200 mL | 100 mL |
| 3 mg/kg | 50 mL | 100 mL | 250 mL | 100 mL |
Home Infusion
Home administration under the supervision of a healthcare provider may be considered for patients on maintenance dose [see Dosage and Administration (2.2, 2.3)] and who are tolerating their infusion well. The decision to have patients moved to home infusion should be made after evaluation and recommendation by a physician.
The dose and infusion rate used in the home setting should remain the same as were used in the supervised clinical setting and should not be changed without supervision of a physician. In case of missed dose(s) or delayed infusion, contact a physician as subsequent infusions may occur in a supervised clinical setting.
Adult patients with ASMD type B and type A/B (Trial 1)
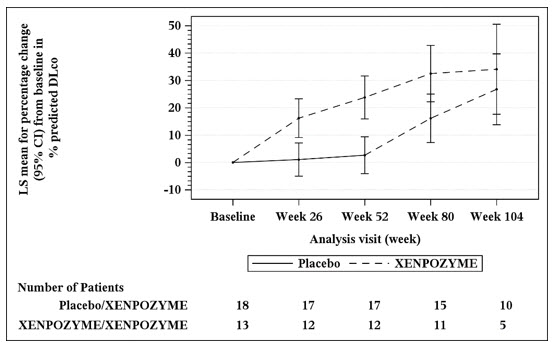
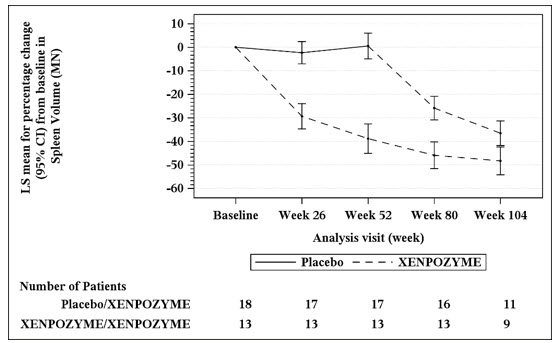
In Trial 1, 13 adult patients received XENPOZYME once every 2 weeks for 52 weeks (primary analysis period (PAP)) at dosages escalating from 0.1 mg/kg to a target dose of 3 mg/kg [see Clinical Studies (14.2)].
Adverse reactions that occurred in at least 7% of XENPOZYME-treated adult patients during the PAP are described in Table 7.
Table 7: Adverse Reactions Occurring at >7% in Adult Patients with ASMD During the 52-Week Primary Analysis Period in Trial 1| Adverse Reaction | XENPOZYME
N=13 | Placebo
N=18 |
|---|
| Headache | 7 (54%) | 8 (44%) |
| Cough | 4 (31%) | 2 (11%) |
| Diarrhea | 2 (15%) | 2 (11%) |
| Hypotension | 2 (15%) | 2 (11%) |
| Ocular hyperemia | 2 (15%) | 1 (6%) |
| Erythema | 1 (8%) | 1 (6%) |
| Asthenia | 1 (8%) | 1 (6%) |
| Pharyngitis | 1 (8%) | 1 (6%) |
| Dyspnea | 1 (8%) | 0 |
| Urticaria | 1 (8%) | 0 |
| Papule | 1 (8%) | 0 |
| Myalgia | 1 (8%) | 0 |
| Throat irritation | 1 (8%) | 0 |
| C-reactive protein abnormal | 1 (8%) | 0 |
Pediatric Patients with ASMD type B and type A/B (Trial 2 and Trial 3)
In Trial 2, 8 pediatric patients less than or equal to 17 years of age received XENPOZYME intravenously once every 2 weeks for 64 weeks [see Clinical Studies (14.3)]. After 64 weeks, all pediatric patients entered into Trial 3.
Adverse reactions that occurred in at least 13% of pediatric patients are described in Table 8.
Table 8: Adverse Reactions Occurring at ≥13% in XENPOZYME-Treated Pediatric Patients with ASMD in Trial 2Duration of treatment in Trial 2 was 64 weeks. All patients continued into Trial 3.
and Trial 3 for an Overall Observation Period of 2.5 to 3.2 Years| Adverse Reactions | XENPOZYME
N=8 |
|---|
| Abdominal pain includes abdominal pain and abdominal pain upper |
| Fatigue includes fatigue and asthenia |
| Rash includes rash and erythema |
| Pyrexia | 8 (100%) |
| Cough | 6 (75%) |
| Diarrhea | 6 (75%) |
| Rhinitis | 6 (75%) |
| Abdominal pain | 5 (63%) |
| Vomiting | 4 (50%) |
| Headache | 4 (50%) |
| Urticaria | 4 (50%) |
| Nausea | 3 (38%) |
| Rash | 3 (38%) |
| Arthralgia | 3 (38%) |
| Pruritus | 2 (25%) |
| Fatigue | 2 (25%) |
| Pharyngitis | 2 (25%) |
| C-reactive protein increased | 1 (13%) |
| Hypotension | 1 (13%) |
| Anaphylactic reaction | 1 (13%) |
| Hypersensitivity | 1 (13%) |
| Infusion site swelling | 1 (13%) |
| Tachycardia | 1 (13%) |
| Pharyngeal swelling | 1 (13%) |
Treatment related serious adverse reactions, hypersensitivity reactions including anaphylaxis, and IARs occurred within 24 hours of infusion and were observed in a higher percentage of pediatric patients than in adult patients.
Laboratory Adverse Reaction
Elevated transaminase levels ranging from 3 times to 14 times the upper limit of normal (ULN) were reported in 4 (13%) adults and 1 (13%) pediatric patient during the XENPOZYME dose escalation phase in clinical trials.
Immunogenicity: Antidrug Antibody-Associated Adverse Reactions
In Trial 1, infusion-associated reactions (including hypersensitivity reactions) occurred in a higher percentage in XENPOZYME-treated patients who developed IgG ADA compared to those who did not develop IgG ADA (73% versus 44%) [see Clinical Pharmacology (12.6) and Clinical Studies (14.2)].
In Trial 2, one XENPOZYME-treated pediatric patient (18-months old) experienced an anaphylactic reaction during the sixth infusion and developed IgE ADA and the highest IgG ADA titers (ADA peak titer 1,600) of the patients in this trial. After treatment discontinuation, XENPOZYME was resumed four months later using a diluted drug solution and a desensitization procedure.
One pediatric patient (16-months old) with ASMD type A, treated with a version of olipudase alfa manufactured from a different process, experienced anaphylactic reactions (both during the fifth and sixth infusions) and developed IgG ADA (highest titer 1,600) and IgE ADA [see Warnings and Precautions (5.1)].
Risk Summary
Based on findings from animal reproduction studies, XENPOZYME may cause embryo-fetal harm when administered to a pregnant female. XENPOZYME dosage initiation or escalation, at any time during pregnancy, is not recommended as it may lead to elevated sphingomyelin metabolite levels that may increase the risk of fetal malformations (see Data), [see Clinical Pharmacology (12.2)]. However, the decision to continue or discontinue XENPOZYME maintenance dosing in pregnancy should consider the female's need for XENPOZYME, the potential drug-related risks to the fetus, and the potential adverse outcomes from untreated maternal ASMD disease.
In an embryo-fetal toxicity study in pregnant mice, a rare malformation (exencephaly) was observed in offspring at an exposure less than the exposure at the maximum recommended human dose (MRHD) of olipudase alfa-rpcp (see Data).
There are no available data on XENPOZYME use in pregnant females to evaluate for a drug associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Advise the pregnant female of the potential risk to the fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, miscarriage, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
In an embryo-fetal development study in pregnant mice, olipudase alfa-rpcp was administered intravenously at doses of 3, 10, or 30 mg/kg daily from gestation day (GD) 6 through GD 15. Exencephaly was observed in 1 litter at each of the 10 and 30 mg/kg dose groups (2 and 3 fetuses, respectively). These data are consistent with published literature reports that brief embryonic exposures to sphingomyelin metabolites or a sphingosine-1-phosphate (S1P) receptor modulator produced neural tube defects, including exencephaly, in chicks and mice.
The developmental No Observed Adverse Effect Level (NOAEL) is 3 mg/kg. The AUC associated with this dose is 0.14-fold the clinical exposure at the MRHD. The developmental Lowest-Observed-Adverse-Effect Level (LOAEL), 10 mg/kg, is also associated with an exposure that is less than the clinical exposure at the MRHD.
In an embryo-fetal development study in pregnant rabbits, olipudase alfa-rpcp was administered intravenously at doses of 3, 10, or 30 mg/kg daily from GD 6 through GD 19. There was no maternal or developmental toxicity. The developmental NOAEL was 30 mg/kg; the AUC0–24 at this dose is approximately 10.5-fold the exposure at the MRHD.
In a study of pre- and postnatal development in mice, olipudase alfa-rpcp was administered intravenously every other day from GD 6 through GD 18; then resumed every other day after parturition, from Lactation Day (LD) 1 through LD 19. Olipudase alfa-rpcp did not induce any effect on maternal reproductive function or on developmental and reproductive parameters of male and female offspring. Therefore, the maternal and developmental NOAELs are 30 mg/kg. Exposures at this dose, based on the embryo-fetal development study, were estimated to be approximately 1.5-fold the MRHD of olipudase alfa-rpcp.
Risk Summary
There are no data on the presence of olipudase alfa-rpcp in human milk, the effects on the breastfed infant, or the effects on milk production. Olipudase alfa-rpcp is present in animal milk. (see Data). When a drug is present in animal milk, it is likely that the drug will be present in human milk. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for XENPOZYME and any potential adverse effects on the breastfed infant from XENPOZYME or from the underlying maternal condition.
Data
Olipudase alfa-rpcp was administered as a single intravenous dose (3 mg/kg) to lactating CD1 mice on post-partum day 7. Milk was not evaluated until post-partum day 9, at which time concentrations of olipudase alfa-rpcp detected were approximately 1.3% the estimated maximal maternal plasma concentration.
Pregnancy Testing
Verify the pregnancy status in females of reproductive potential prior to initiating XENPOZYME.
Contraception
Females
Advise females of reproductive potential to use effective contraception during treatment and for 14 days after the last dose if XENPOZYME is discontinued.
Plasma Ceramide Levels
Ceramide is elevated in plasma of adult and pediatric patients with ASMD. Plasma ceramide levels showed a transient increase after each administration (post infusion) of XENPOZYME. In the dose escalation phase, plasma ceramide levels were substantially increased compared to the baseline level. Plasma ceramide levels gradually decreased following repeated administration of XENPOZYME and the pre-infusion levels were generally lower than the baseline level during the maintenance phase of treatment.
- In adult patients with ASMD in Trial 1 [see Clinical Studies (14.2)], the mean (standard deviation, SD) pre-infusion plasma ceramide concentration was 3.7 (1.4) mg/L at baseline and decreased to 2.2 (0.6) mg/L at Week 52 following treatment with XENPOZYME.
- In pediatric patients with ASMD in Trial 2 [see Clinical Studies (14.3)], the mean (SD) pre-infusion plasma ceramide concentration was 4.7 (0.9) mg/L at baseline and decreased to 1.8 (0.3) mg/L at Week 52 following treatment with XENPOZYME.
Plasma Lysosphingomyelin Levels
Lysosphingomyelin is substantially elevated in plasma of adult and pediatric patients with ASMD. Plasma lysosphingomyelin levels decreased after repeated administration of XENPOZYME.
- In adult patients with ASMD in Trial 1 [see Clinical Studies (14.2)], the mean (SD) pre-infusion plasma lysosphingomyelin concentration was 379 (204) mcg/L at baseline and decreased to 99 (118) mcg/L at Week 52 following treatment with XENPOZYME.
- In pediatric patients with ASMD in Trial 2 [see Clinical Studies (14.3)], the mean (SD) pre-infusion plasma lysosphingomyelin concentration was 625 (339) mcg/L at baseline and decreased to 80 (47) mcg/L at Week 52 following treatment with XENPOZYME.
Liver Sphingomyelin Content
In adult patients, the liver sphingomyelin content, as assessed by histopathology, decreased from baseline to Week 52 in the XENPOZYME treatment group compared to an increase in the placebo group.
Distribution
The mean (SD) volume of distribution of olipudase alfa-rpcp was 13 (2) L in adult patients with ASMD.
Elimination
The mean (SD) clearance of olipudase alfa-rpcp was 0.33 (0.07) L/h and the mean half-life (t1/2) ranged from 32 to 38 hours in adult patients with ASMD.
Metabolism
The metabolic pathway of olipudase alfa-rpcp has not been characterized. Olipudase alfa-rpcp is expected to be metabolized into small peptides and amino acids via catabolic pathways.
Specific Populations
Pediatric Patients
In pediatric patients (1.5 to 17.5 years of age) with ASMD, the mean (SD) Cmax was 24.3 (2.8) mcg/mL and the mean (SD) AUC was 449 (70) mcg∙h/mL at the recommended maintenance dose of 3 mg/kg administered once every 2 weeks.
Carcinogenesis
Studies to evaluate the carcinogenic potential of olipudase alfa-rpcp have not been conducted.
Mutagenesis
Studies to evaluate the mutagenic potential of olipudase alfa-rpcp have not been conducted.
Impairment of Fertility
Intravenous administration of olipudase alfa-rpcp every other day at doses up to 30 mg/kg had no adverse effects in a combined study of fertility in male and female mice. Exposures at this dose, based on the embryo-fetal development study, were estimated to be approximately 1.5-fold those of the MRHD of olipudase alfa-rpcp.
How Supplied
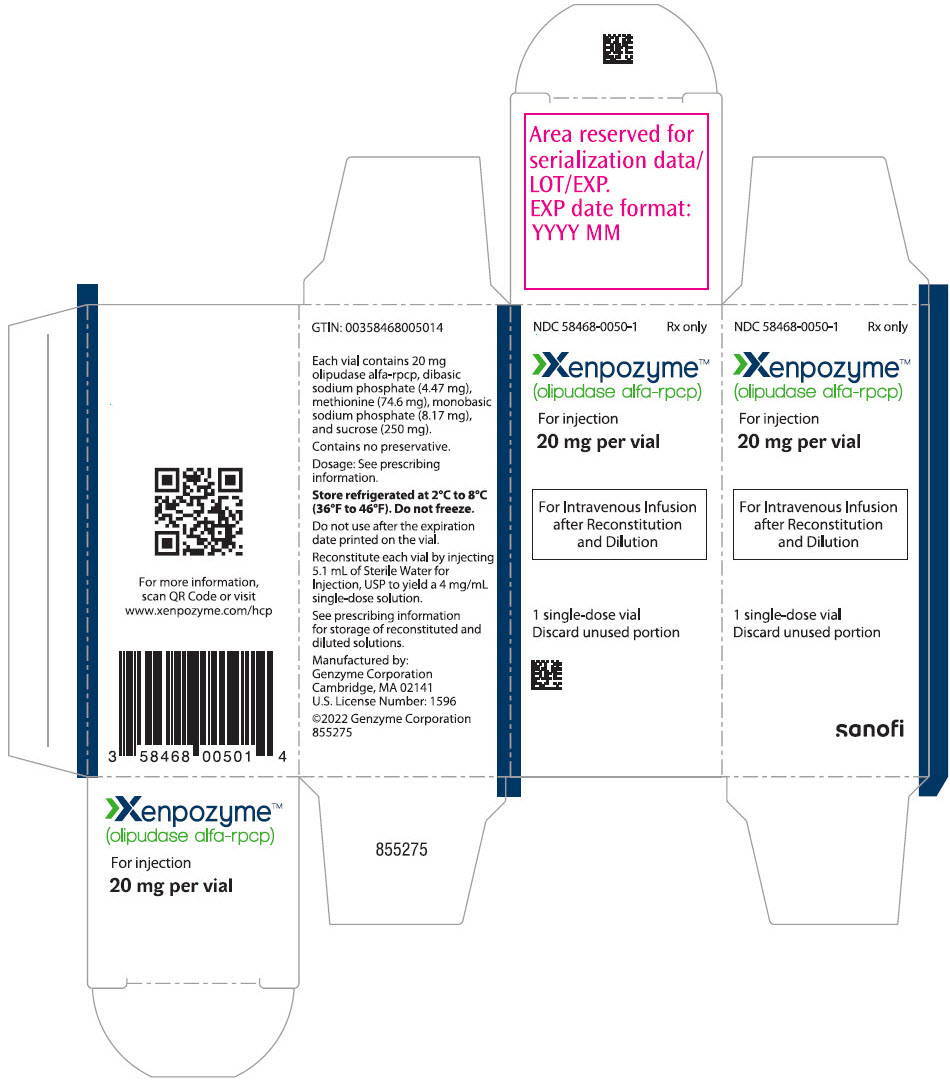
XENPOZYME (olipudase alfa-rpcp) for injection is supplied as a sterile white to off-white lyophilized powder for reconstitution in a single-dose vial. XENPOZYME does not contain any preservatives.
XENPOZYME is available supplied as:
- Carton containing one 20 mg single-dose vial (NDC 58468-0050-1)
- Carton containing one 4 mg single-dose vial (NDC 58468-0051-1)
Hypersensitivity Reactions (Including Anaphylaxis) and Infusion-Associated Reactions (IARs)
Advise the patient and caregiver that reactions related to the infusion may occur during and after XENPOZYME treatment, including life-threatening hypersensitivity reactions, anaphylaxis, and IARs. Inform the patient and/or caregiver of the signs and symptoms of hypersensitivity reactions and IARs and to seek immediate medical care should signs and symptoms occur [see Warnings and Precautions (5.1, 5.2)].
Embryo-Fetal Toxicity
XENPOZYME may cause embryo-fetal harm. Advise the pregnant female and females of reproductive potential of the potential risk to the fetus. Advise a female patient and caregiver to inform their healthcare provider of a known or suspected pregnancy [see Use in Specific Populations (8.1)].
Advise a female of reproductive potential to use effective contraception during treatment and for 14 days after the last dose if XENPOZYME is discontinued [see Use in Specific Populations (8.1, 8.3)].
Manufactured by:
Genzyme Corporation
450 Water Street
Cambridge, MA 02141
U.S. License Number: 1596
©2024 Sanofi. All rights reserved. XENPOZYME is a registered trademark of Genzyme Corporation.