Anemia
New or worsening Grade 3 anemia occurred in 34% of INREBIC-treated patients. The median time to onset of the first Grade 3 anemia was approximately 2 months, with 75% of cases occurring within 3 months. Mean hemoglobin levels reached nadir after 12 to 16 weeks with partial recovery and stabilization after 16 weeks. Red blood cell transfusions were received by 51% of INREBIC-treated patients and permanent discontinuation of INREBIC occurred due to anemia in 1% of patients. Consider dose reduction for patients who become red blood cell transfusion dependent [see Dosage and Administration (2.6)].
Thrombocytopenia
New or worsening Grade ≥3 thrombocytopenia during the randomized treatment period occurred in 12% of INREBIC-treated patients. The median time to onset of the first Grade 3 thrombocytopenia was approximately 1 month; with 75% of cases occurring within 4 months. Platelet transfusions were received by 3.1% of INREBIC-treated patients. Permanent discontinuation of treatment due to thrombocytopenia and bleeding that required clinical intervention both occurred in 2.1% of INREBIC-treated patients.
Obtain a complete blood count (CBC) at baseline, periodically during treatment, and as clinically indicated. For Grade 3 thrombocytopenia with active bleeding or Grade 4 thrombocytopenia, interrupt INREBIC until resolved to less than or equal to Grade 2 or baseline. Restart dose at 100 mg daily below the last given dose and monitor platelets as clinically indicated [see Dosage and Administration (2.6)].
JAKARTA Trial
The safety of INREBIC was evaluated in the randomized treatment period of the JAKARTA trial [see Clinical Studies (14)]. Key eligibility criteria included adult patients with intermediate-2 or high-risk primary MF or post-PV MF or post-ET MF with splenomegaly, platelet count ≥50 × 109/L, and no splenectomy. Patients received INREBIC at 400 mg daily (n=96) or placebo (n=95). Among patients receiving INREBIC, 82% were exposed for more than 6 months and 65% for more than one year. Patients had a median duration of exposure to INREBIC 400 mg daily of 15.5 months compared with placebo where patients were treated for 6 months or until disease progression after which patients were allowed to crossover to active treatment. The median age of patients who received INREBIC was 65 years (range: 27 to 86 years), 59% were male, 90% were White, 8% were Asian, 1% were Black, 1% were Other, and 92% had an Eastern Cooperative Oncology Group (ECOG) performance status of 0 to 1.
Serious adverse reactions occurred in 21% of INREBIC-treated patients. Serious adverse reactions in ≥2% of patients receiving INREBIC 400 mg daily included cardiac failure (5%) and anemia (2%). Fatal adverse reactions of cardiogenic shock occurred in 1% of patients receiving INREBIC 400 mg daily.
Permanent discontinuation due to an adverse reaction occurred in 14% of patients receiving INREBIC. Most frequent reasons for permanent discontinuation in ≥2% of patients receiving INREBIC included cardiac failure (3%), thrombocytopenia, myocardial ischemia, diarrhea, and increased blood creatinine (2% each).
Dosage interruptions due to an adverse reaction during the randomized treatment period occurred in 21% of patients who received INREBIC. Adverse reactions requiring dosage interruption in >3% of patients who received INREBIC included diarrhea and nausea.
Dosage reductions due to an adverse reaction during the randomized treatment period occurred in 19% of patients who received INREBIC. Adverse reactions requiring dosage reduction in >2% of patients who received INREBIC included anemia (6%), diarrhea (3%), vomiting (3%), and thrombocytopenia (2%).
The most common adverse reactions (reported in ≥20%) were diarrhea, nausea, anemia, and vomiting.
Tables 3 and 4 summarize the common adverse reactions and laboratory abnormalities, respectively, in JAKARTA during randomized treatment.
Table 3: Adverse Reactions Reported in ≥5% Patients Receiving INREBIC 400 mg with a Difference between Arms of >5% during Randomized Treatmenta CTCAE version 4.03.
b Only 1 Grade 4 event (anemia).
c Includes cystitis. |
Adverse Reactiona | INREBIC 400 mg
(n=96) | Placebo
(n=95) |
All Grades
% | Grade ≥3b
% | All Grades
% | Grade ≥3
% |
Diarrhea | 66 | 5 | 16 | 0 |
Nausea | 62 | 0 | 15 | 0 |
Anemia | 40 | 30 | 14 | 7 |
Vomiting | 39 | 3.1 | 5 | 0 |
Fatigue or asthenia | 19 | 5 | 16 | 1.1 |
Muscle spasms | 12 | 0 | 1.1 | 0 |
Blood creatinine increased | 10 | 1 | 1.1 | 0 |
Pain in extremity | 10 | 0 | 4.2 | 0 |
Alanine aminotransferase Increased | 9 | 0 | 1.1 | 0 |
Headache | 9 | 0 | 1.1 | 0 |
Weight increased | 9 | 0 | 4.2 | 0 |
Dizziness | 8 | 0 | 3.2 | 0 |
Bone pain | 8 | 0 | 2.1 | 0 |
Urinary tract infectionc | 6 | 0 | 1.1 | 0 |
Dysuria | 6 | 0 | 0 | 0 |
Aspartate aminotransferase increased | 5 | 0 | 1.1 | 0 |
Clinically significant adverse reactions reported in 5% or less of patients: hypertension of all grades was reported in 4.2% of patients and Grade 3 or higher in 3% of INREBIC-treated patients.
Changes in selected postbaseline laboratory values that were observed are shown in Table 4 for the JAKARTA trial during randomized treatment.
Table 4: Selected Laboratory Abnormalities That Have Worsened from Baseline (≥20%) in Patients Receiving INREBIC with a Difference between Arms of >10% When Compared to Placebo in JAKARTA during Randomized Treatment | INREBIC 400 mg
(n=96) | Placebo
(n=95) |
Laboratory Parameter | All Grades
% | Grade ≥3
% | All Grades
% | Grade ≥3
% |
Hematology |
Anemia | 74 | 34 | 32 | 10 |
Thrombocytopenia | 47 | 12 | 26 | 10 |
Neutropenia | 23 | 5 | 13 | 3.3 |
Biochemistry |
Creatinine increased | 59 | 3.1 | 19 | 1.1 |
ALT increased | 43 | 1 | 14 | 0 |
AST increased | 40 | 0 | 16 | 1.1 |
Lipase increased | 35 | 10 | 7 | 2.2 |
Hyponatremia | 26 | 5 | 11 | 4.3 |
Amylase increased | 24 | 2.1 | 5 | 0 |
In FEDR-MF-002, a randomized controlled post-marketing study of INREBIC (n=134) vs. best available therapy (BAT, n=67), the incidence of thiamine levels below the lower limit of normal (< 70 nmol/L) was 21% for INREBIC vs 5% for BAT. Thiamine levels < 30 nmol/L were not observed in the study. The median time to the first low thiamine level after initiation of INREBIC was 30 days. The frequency of low thiamine levels in participants receiving INREBIC was 2% in those receiving thiamine supplementation 100 mg orally per day vs. 39% in those not receiving thiamine supplementation.
Strong CYP3A4 Inhibitors
Coadministration of INREBIC with a strong CYP3A4 inhibitor increases fedratinib exposure [see Clinical Pharmacology (12.3)]. Increased exposure may increase the risk of adverse reactions. Consider alternative therapies that do not strongly inhibit CYP3A4 activity. Alternatively, reduce the dose of INREBIC when administering with a strong CYP3A4 inhibitor [see Dosage and Administration (2.4)].
Strong and Moderate CYP3A4 Inducers
Coadministration of INREBIC with a strong or moderate CYP3A4 inducer can decrease fedratinib exposure [see Clinical Pharmacology (12.3)]. Decreased exposure may reduce the effectiveness of INREBIC. Avoid INREBIC with strong and moderate CYP3A4 inducers.
Dual CYP3A4 and CYP2C19 Inhibitors
Coadministration of INREBIC with a dual CYP3A4 and CYP2C19 inhibitor increases fedratinib exposure [see Clinical Pharmacology (12.3)]. Increased exposure may increase the risk of adverse reactions. Due to potential increase of exposure, patients taking concomitant dual CYP3A4 and CYP2C19 inhibitors require more intensive safety monitoring and, if necessary, dose modifications of INREBIC based on adverse reactions [see Dosage and Administration (2.6)].
CYP3A4, CYP2C19, or CYP2D6 Substrate Drugs
Coadministration of INREBIC with drugs that are CYP3A4 substrates, CYP2C19 substrates, or CYP2D6 substrates increases the concentrations of these drugs, which may increase the risk of adverse reactions of these drugs [see Clinical Pharmacology (12.3)]. Monitor for adverse reactions and adjust the dose of drugs that are CYP3A4, CYP2C19, or CYP2D6 substrates as necessary when coadministered with INREBIC.
OCT2 and MATE1/2-K Substrate Drugs
Coadministration of INREBIC with drugs that are renally excreted via organic cation transporter (OCT2) and multidrug and toxin extrusion (MATE)1/2-K can decrease renal clearance of those drugs [see Clinical Pharmacology (12.3)]. Monitor for adverse reactions and consider dose modifications for drugs that are renally excreted via OCT2 or MATE1/2-K (e.g., metformin), as necessary when coadministered with INREBIC.
Risk Summary
There are no available data on INREBIC use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. In animal reproduction studies, oral administration of fedratinib to pregnant rats during organogenesis at doses considerably lower than the recommended human daily dose of 400 mg/day resulted in adverse developmental outcomes (see Data). Consider the benefits and risks of INREBIC for the mother and possible risks to the fetus when prescribing INREBIC to a pregnant woman.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Adverse outcomes in pregnancy occur regardless of the health of the mother or the use of medications. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
In an embryo-fetal development study in pregnant rats, fedratinib administration at a dose of 30 mg/kg/day during organogenesis (gestation days 6 to 17) was associated with adverse developmental outcomes including skeletal variations (such as additional ossification center of neuronal arches). These effects occurred in rats at approximately 0.1 times the clinical exposure based on AUC at the recommended daily dose. At lower doses of 10 mg/kg/day (0.01 times the clinical exposure at the recommended daily dose), fedratinib administered to pregnant rats resulted in maternal toxicity of decreased gestational weight gain.
In an embryo-fetal development study in pregnant rabbits, fedratinib administration during organogenesis (gestation Days 6 to 18) did not produce developmental or maternal toxicity at doses up to the highest dose level tested, 30 mg/kg/day (approximately 0.08 times the clinical exposure at the recommended daily dose). In a separate study, administration of 80 mg/kg/day fedratinib to rabbits resulted in maternal mortality.
In a pre- and postnatal study in rats, fedratinib was administered to pregnant female rats at doses of 3, 10, or 30 mg/kg/day from Day 6 of gestation through Day 20 of lactation, with weaning on Day 21. A slight decrease in maternal body weight gain during gestation occurred at 30 mg/kg/day. The offspring from the high dose (30 mg/kg) had decreased body weight preweaning in both sexes and postweaning through the maturation phase in males. These effects occurred at exposures approximately 0.1 times the clinical exposure at the recommended daily dose.
Risk Summary
There are no data on the presence of fedratinib or its metabolites in human milk, the effects on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions in a breastfed child, advise patients not to breastfeed during treatment with INREBIC, and for at least 1 month after the last dose.
Cardiac Electrophysiology
The potential for QTc prolongation with fedratinib was evaluated in 31 patients with solid tumors. No large mean increase in the QTc interval (>20 ms) was detected with daily dosing of fedratinib 500 mg (1.25 times the recommended dose) for 14 days.
Absorption
Following 400 mg once daily, fedratinib median time to peak concentrations (Tmax) at steady-state is 3 hours (range: 2 to 4 hours).
Following the administration of a single 400 mg dose of fedratinib delivered orally or via nasogastric tube with contents from four 100-mg capsules dispersed in approximately 180 mL nutritional supplement (Ensure® Plus), the systemic exposures of fedratinib are similar.
Effect of Food
A low-fat, low-calorie (total 162 calories: 6% from fat, 78% from carbohydrate and 16% from protein) or a high-fat, high-calorie (total 815 calories: 52% from fat, 33% from carbohydrate and 15% from protein) meal increased area under the curve over time to infinity (AUCinf) up to 24% and Cmax up to 14% of a single 500 mg dose (1.25 times the recommended dose) of fedratinib.
Distribution
The apparent volume of distribution of fedratinib at steady-state is 1770 L in patients with myelofibrosis at 400 mg once daily dose. Fedratinib is 92% or greater bound to human plasma proteins.
Elimination
Fedratinib pharmacokinetics is characterized by a biphasic disposition with an effective half-life of 41 hours, a terminal half-life of approximately 114 hours, and apparent clearance (CL/F) (%CV) of 13 L/hr (51%) in patients with myelofibrosis.
Metabolism
Fedratinib is metabolized by CYP3A4, CYP2C19, and flavin-containing monooxygenase 3 (FMO3). Fedratinib accounts for approximately 80% of total circulating drug in plasma after oral administration.
Excretion
Following a single oral dose of radiolabeled fedratinib, 77% (23% unchanged) of the administered dose was excreted in feces and 5% (3% unchanged) was eliminated in urine.
Specific Populations
Age (20 years to 95 years), race (White, Asians), sex, body weight (40 kg to 135 kg), mild (Child-Pugh A), moderate (Child-Pugh B), or severe (Child-Pugh C) hepatic impairment, and mild (CLcr 60 mL/min to 89 mL/min by C-G) renal impairment did not have clinically meaningful effects on the pharmacokinetics of fedratinib.
Patients with Renal Impairment
Following a single 300 mg dose (0.75 times the recommended dose) of INREBIC, the AUCinf of fedratinib increased by 1.5-fold in subjects with moderate (CLcr 30 mL/min to 59 mL/min by C-G) renal impairment and 1.9-fold in subjects with severe (CLcr 15 mL/min to 29 mL/min by C-G) renal impairment, compared to that in subjects with normal renal function (CLcr ≥90 mL/min by C-G).
Drug Interaction Studies
Clinical Studies and Model-Informed Approaches
Effect of Strong and Moderate CYP3A4 Inhibitors
Coadministration of ketoconazole (strong CYP3A4 inhibitor: 200 mg twice daily) with a single dose of INREBIC (300 mg; 0.75 times the recommended dose) increased fedratinib AUCinf by 3-fold.
Coadministration of ketoconazole (400 mg once daily) with INREBIC 400 mg once daily is predicted to increase fedratinib AUC at steady state by 2-fold.
Coadministration of moderate CYP3A4 inhibitors, erythromycin (500 mg three times daily) or diltiazem (120 mg twice daily), with INREBIC 400 mg once daily is predicted to increase fedratinib AUC at steady state by 1.2-, and 1.1-fold, respectively.
Effect of Dual CYP3A4 and CYP2C19 Inhibitor
Coadministration of fluconazole (dual CYP3A4 and CYP2C19 inhibitor; 200 mg once daily) with a single dose of fedratinib (100 mg; 0.25 times the recommended dose) increased AUCinf by 1.7-fold.
Coadministration of fluconazole (200 mg once daily) with INREBIC 400 mg once daily is predicted to increase fedratinib AUC at steady state by approximately 1.5-fold.
Effect of Strong and Moderate CYP3A4 Inducers
Coadministration of rifampin (strong CYP3A4 inducer: 600 mg once daily) or efavirenz (moderate CYP3A4 inducer: 600 mg once daily) with a single dose of fedratinib (500 mg; 1.25 times the recommended dose) decreased AUCinf of fedratinib by approximately 81% or 47%, respectively.
Effect of Gastric Acid Reducing Agents
Coadministration of pantoprazole (proton pump inhibitor: 40 mg once daily) with a single dose of INREBIC (500 mg; 1.25 times the recommended dose) increased fedratinib AUCinf by 1.2-fold.
Effect of Fedratinib on Drugs that are CYP3A, CYP2C19, or CYP2D6 Substrates
Coadministration of a single dose of midazolam (CYP3A substrate: 2 mg), omeprazole (CYP2C19 substrate: 20 mg), and metoprolol (CYP2D6 substrate: 100 mg) with fedratinib increased midazolam, omeprazole, or metoprolol AUCinf by 4-, 3-, and 2-fold, respectively.
In Vitro and Clinical Transporter Studies
Fedratinib as a Substrate for Transporters:
Fedratinib is a substrate of P-glycoprotein (P-gp) but not breast cancer resistance protein (BCRP), BSEP, multidrug resistance protein (MRP2), and organic anion transporting polypeptide (OATP)1B1 and OATP1B3 in vitro.
Effect of Fedratinib on Transporter Substrates
Fedratinib inhibits P-gp, BCRP, OATP1B1, OATP1B3, OCT1, OCT2, MATE1, and MATE2-K, but not BSEP, MRP2, and organic anion transporter (OAT)1 and OAT3 in vitro.
Coadministration of a single dose of fedratinib (600 mg; 1.5 times the recommended dose) with a single dose of digoxin (P-gp substrate: 0.25 mg), rosuvastatin (OATP1B1/1B3 and BCRP substrate: 10 mg), and metformin (OCT2 and MATE1/2-K substrate: 1000 mg) had no clinically meaningful effect on the AUCinf of digoxin, rosuvastatin, and metformin. Renal clearance of metformin was decreased by 36% in the presence of fedratinib. Contrary to unchanged PK, the glucose lowering PD effect of metformin in the presence of fedratinib appears reduced, with baseline adjusted glucose AUC being approximately 50% higher in response to an oral glucose challenge.
JAKARTA
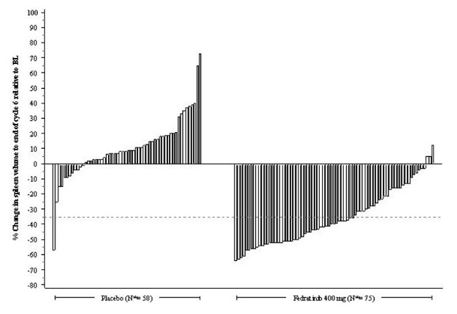
JAKARTA (NCT01437787) was a double-blind, randomized, placebo-controlled trial in patients with intermediate-2 or high-risk myelofibrosis, post-polycythemia vera myelofibrosis or post-essential thrombocythemia myelofibrosis with splenomegaly. A total of 289 patients were randomized to receive either INREBIC 500 mg (N=97), 400 mg (n=96) or placebo (n=96) once daily for at least 6 cycles. The median age was 65 years (range 27 to 86 years), 47% of patients were older than 65 years and 59% were male. Sixty-four percent (64%) of patients had primary MF, 26% had post-polycythemia vera MF, and 10% had post-essential thrombocythemia MF. Fifty-two percent (52%) of patients had intermediate-2 risk, and 48% had high-risk disease. The median baseline hemoglobin level was 10.2 g/dL. The median baseline platelet count was 214 × 109/L; 16% of patients had a platelet count <100 × 109/L and 84% of patients had a platelet count ≥100 × 109/L. Patients had a baseline median palpable spleen length of 15 cm. Patients had a baseline median spleen volume as measured by magnetic resonance imaging (MRI) or computed tomography (CT) of 2568 mL (range of 316 to 8244 mL) (the upper limit of normal is approximately 300 mL). Patients underwent MRI or CT spleen volume assessment (after the third and sixth cycle) with a follow-up scan 4 weeks after Cycle 6.
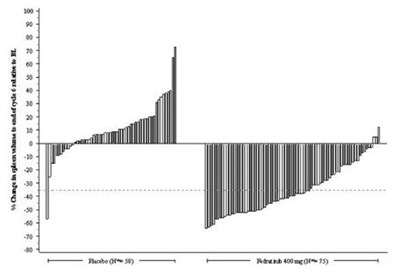
The efficacy of INREBIC in the treatment of patients with primary or secondary myelofibrosis was established based upon the proportion of patients achieving greater than or equal to a 35% reduction from baseline in spleen volume at the End of Cycle 6 as measured by MRI or CT with a follow-up scan 4 weeks later.
Efficacy analyses are presented in Table 5.
Table 5: Percent of Patients Achieving 35% or Greater Reduction from Baseline in Spleen Volume at the End of Cycle 6 in the Phase 3 Study, JAKARTA (ITT Population)Spleen Response by MRI/CT at the End of Cycle 6 with a Follow-up Scan 4 Weeks Later | INREBIC 400 mg
N=96
n (%) | Placebo
N=96
n (%) |
Number (%) of Patients with Spleen Volume Reduction by 35% or More | 35 (37) | 1 (1) |
p-value | p<0.0001 |
Figure 1 shows the percent change in spleen volume from baseline for patients who have an evaluable MRI/CT at the End of Cycle 6.
Figure 1: Percent Change in Spleen Volume from Baseline at the End of Cycle 6 for Each Patient in the Phase 3 Study, JAKARTA
Inrebic-figure-1 (Inrebic Figure 1)
N*: Subjects with available percent change in spleen volume at EOC6.
Based on Kaplan-Meier estimates, the median duration of spleen response was 18.2 months for the INREBIC 400 mg group.
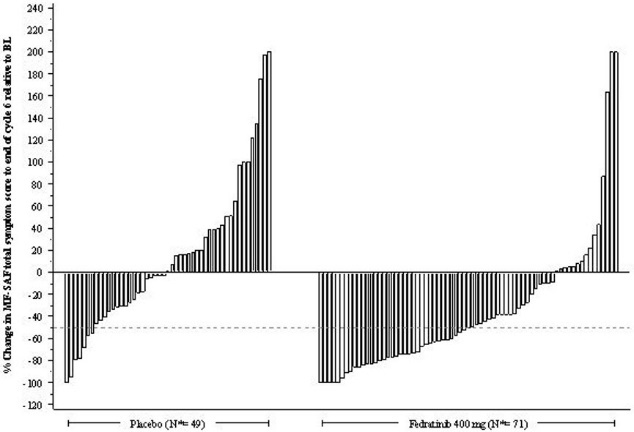
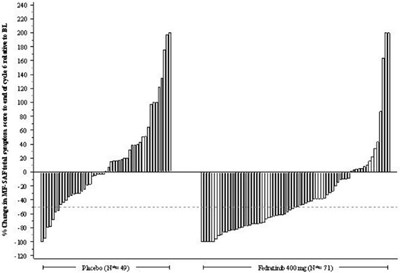
Additional outcomes included the proportion of patients with a 50% or greater reduction in Total Symptom Score from baseline to the End of Cycle 6 as measured by the modified Myelofibrosis Symptom Assessment Form (MFSAF) v2.0 diary.
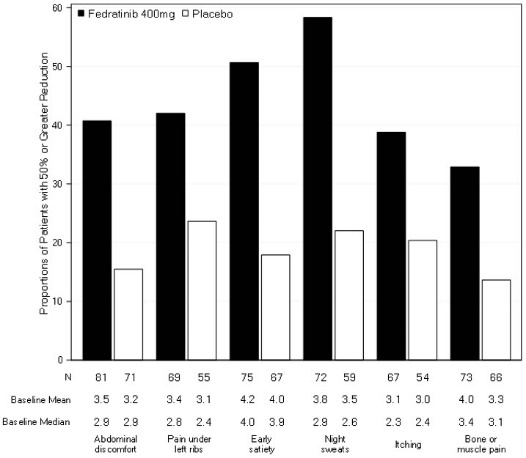
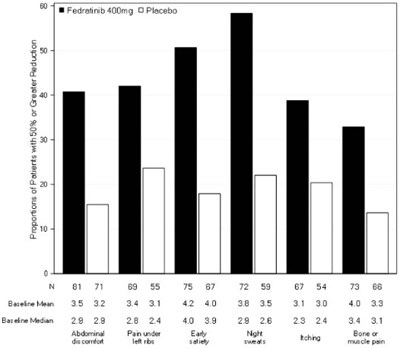
The modified MFSAF v2.0 is a patient diary capturing the 6 core symptoms of MF: night sweats, itching, abdominal discomfort, early satiety, pain under ribs on left side, and bone or muscle pain. The modified MFSAF diary was completed daily during the week prior to Day 1 of each treatment cycle, and at the End of Cycle 6. Symptom scores ranged from 0 ("absent") to 10 ("worst imaginable"). These scores were added to create the Total Symptom Score, which has a maximum score of 60. At baseline, the mean Total Symptom Score was 17.95 in the 400 mg group and 15.45 in the placebo group.
The proportion of patients with a 50% or greater reduction in Total Symptom Score was 40% in the INREBIC 400 mg group and 9% in the placebo group (Table 6). Results are excluded for 22 patients: 6 patients with a baseline Total Symptom Score of zero (2 in the INREBIC 400 mg group and 4 in the placebo group) and 16 patients with missing baseline (5 in the INREBIC 400 mg group and 11 in the placebo group).
Table 6: Improvement in Total Symptom Score in Patients with Myelofibrosis in the Phase 3 Study, JAKARTA | INREBIC 400 mg
(N=89)
n (%) | Placebo
(N=81)
n (%) |
Number (%) of Patients with 50% or Greater Reduction in Total Symptom Score at the End of Cycle 6 | 36 (40) | 7 (9) |
p-value | p<0.0001 |
Figure 2 shows the percent change in Total Symptom Score from baseline at the End of Cycle 6 for each patient.
Figure 2: Percent Change from Baseline in Total Symptom Score at the End of Cycle 6 for Each Patient in the Phase 3 Study, JAKARTA
Inrebic-figure-2 (Inrebic Figure 2)
N*: Subjects with available percent change in Total Symptom Score at EOC6.
Figure 3 displays the proportion of patients with at least a 50% improvement in each of the individual symptoms that comprised the Total Symptom Score indicating that all 6 of the symptoms contributed to the higher Total Symptom Score response rate in the group treated with INREBIC.
Figure 3: Proportion of Patients Achieving 50% or Greater Reduction in Individual Symptom Scores at the End of Cycle 6 with Nonzero Baseline Scores
Inrebic-figure-3 (Inrebic Figure 3)
Encephalopathy, including Wernicke's
Advise patients that serious and fatal encephalopathy, including Wernicke's, has occurred in patients taking INREBIC. Wernicke's encephalopathy is a neurological emergency resulting from acute thiamine (Vitamin B1) deficiency. Advise patients of the need to monitor thiamine levels [see Dosage and Administration (2.1,2.3,2.7), and Warnings and Precautions (5.1)]. Instruct patients that they should receive prophylaxis with thiamine 100 mg orally daily while taking INREBIC [see Dosage and Administration (2.7)]. Advise patients to seek emergency medical attention for any change in mental status such as confusion, drowsiness or memory impairment, cerebellar abnormalities such as ataxia, and ophthalmic abnormalities such as diplopia and nystagmus. Advise patients to contact their healthcare provider right away if they experience nausea, vomiting, diarrhea, and weight loss unresponsive to treatment resulting in malnutrition and lower thiamine levels, which may lead to Wernicke's encephalopathy [see Boxed Warning and Warnings and Precautions (5.1)].
Anemia and Thrombocytopenia
Advise patients that INREBIC is associated with anemia and thrombocytopenia, and of the need to monitor complete blood counts before and during treatment [see Warnings and Precautions (5.2)].
Symptom Exacerbation Following Interruption or Discontinuation of Treatment with INREBIC
Inform patients that after discontinuation of treatment, signs and symptoms from myeloproliferative neoplasms may return. Instruct patients not to interrupt or discontinue INREBIC therapy without consulting their healthcare provider [see Warnings and Precautions (5.10)]
Gastrointestinal Toxicity
Advise patients to contact their healthcare provider if they experience intractable diarrhea, nausea, or vomiting. Prescribers should advise patients of the potential complications of severe diarrhea, nausea, or vomiting [see Warnings and Precautions (5.3)].
Hepatic Toxicity
Advise patients that INREBIC may increase liver enzymes and of the need to monitor liver enzyme levels [see Warnings and Precautions (5.4)].
Amylase and Lipase Elevation
Advise patients that INREBIC may increase amylase and lipase and of the need to monitor amylase and lipase [see Warnings and Precautions (5.5)].
Uveitis
Advise patients that INREBIC can cause uveitis and to contact their healthcare provider if they experience any symptoms, including eye pain, redness, photophobia, floaters, and decreased vision [see Warnings and Precautions (5.6)].
Major Adverse Cardiac Events (MACE)
Advise patients that events of major adverse cardiac events (MACE) including myocardial infarction, stroke, and cardiovascular death, have been reported in clinical studies with another JAK-inhibitor used to treat rheumatoid arthritis, a condition for which INREBIC is not indicated. Advise patients, especially current or past smokers or patients with other cardiovascular risk factors, to be alert for the development of signs and symptoms of cardiovascular events [see Warnings and Precautions (5.6)].
Thrombosis
Advise patients that events of DVT and PE have been reported in clinical studies with another JAK-inhibitor used to treat rheumatoid arthritis, a condition for which INREBIC is not indicated. Advise patients to tell their healthcare provider if they develop any signs or symptoms of a DVT or PE [see Warnings and Precautions (5.7)].
Secondary Malignancies
Advise patients, especially current or past smokers and patients with a known secondary malignancy (other than a successfully treated NMSC), that lymphoma and other malignancies (excluding NMSC) have been reported in clinical studies with another JAK-inhibitor used to treat rheumatoid arthritis, a condition for which INREBIC is not indicated [see Warnings and Precautions (5.8)].
Lactation
Advise patients not to breastfeed during treatment with INREBIC and for at least 1 month after the final dose [see Use in Specific Populations (8.2)].
Missed Dose
Instruct patients that if they miss a dose of INREBIC, skip the dose and take it the next day and return to normal schedule [see Dosage and Administration (2.2)]. Warn patients not to take 2 doses to make up for the missed dose.
Administration Instructions
For patients who cannot swallow INREBIC capsules whole or those with a nasogastric tube, mix the content of the capsule(s) with approximately 180 mL of Ensure® Plus liquid nutritional supplement [see Clinical Pharmacology (12.3)] at room temperature [between 20°C to 25°C (68°F to 77°F)] in a glass container, then promptly take by mouth or give through a nasogastric tube (French size 14 or 16) within 2 hours of preparation. If using a nasogastric tube, flush it with 60 mL of water after administering the mixture [see Dosage and Administration (2.2.)].
Marketed by:
Bristol-Myers Squibb Company
Princeton, NJ 08543 USA
INREBIC® is a trademark of Impact Biomedicines, Inc., a Bristol Myers Squibb company.
INRPI.011/MG.008