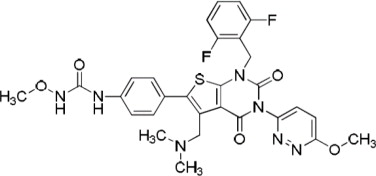
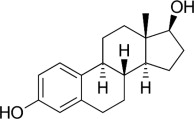
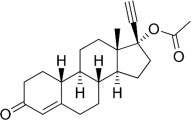
Contraindication in Patients with Hepatic Impairment
MYFEMBREE is contraindicated in patients with known hepatic impairment or disease [see Contraindications (4) and Use in Specific Populations (8.6)]. Steroid hormones may be poorly metabolized in patients with impaired liver function [see Clinical Pharmacology (12.3)].
Transaminase Elevations
Instruct women to promptly seek medical attention for symptoms or signs that may reflect liver injury, such as jaundice or right upper abdominal pain. Acute liver test abnormalities may necessitate the discontinuation of MYFEMBREE use until the liver tests return to normal and MYFEMBREE causation has been excluded.
In placebo-controlled clinical trials, in women with uterine fibroids or endometriosis, elevations (≥ 3 times the upper limit of the normal [ULN] of reference range) in alanine aminotransferase (ALT) occurred in 0.4% (1/254) and 0.7% (3/418) of MYFEMBREE-treated women, respectively, as compared to 0% (0/256) and 0.5% (2/416) of placebo-treated women, respectively; moreover, elevations (≥ 3 times ULN of reference range) in aspartate aminotransferase (AST) occurred in 0.8% (2/254) and 0.2% (1/418) of MYFEMBREE-treated women, respectively, as compared to 0.4% (1/256) and 0.5% (2/416) of placebo-treated women, respectively. No patterns in time to onset of these liver transaminase elevations were identified.
Heavy Menstrual Bleeding Associated with Uterine Leiomyomas
The safety of MYFEMBREE was evaluated in two placebo-controlled clinical trials, Study L1 (LIBERTY 1) and Study L2 (LIBERTY 2), in women with heavy menstrual bleeding associated with uterine fibroids. In these trials, women received a once daily relugolix 40-mg tablet and an over-encapsulated tablet of E2 1 mg and NETA 0.5 mg (relugolix + E2/NETA), which is equivalent to 1 tablet of MYFEMBREE. Across the two trials, 254 women received MYFEMBREE once daily for 24 weeks. Additionally, 256 women received placebo for 24 weeks, and 258 women received relugolix 40-mg monotherapy once daily for 12 weeks followed by MYFEMBREE for 12 weeks [see Clinical Studies (14.1)]. Of these, 476 women were treated with MYFEMBREE in a 28-week extension trial, Study L3 (LIBERTY Extension), for a total treatment duration of up to 12 months. Demographics were similar across the studies; approximately 43% were White, 51% were Black, and approximately 23% were of Hispanic or Latino ethnicity. The mean age at study entry was approximately 42 years (range 19 to 51 years). Of women who completed Study L3, 229 were rerandomized to continue MYFEMBREE or withdraw from therapy (placebo) for an additional 52 weeks (Study L4).
Serious Adverse Reactions
In Studies L1 and L2, serious adverse reactions were reported in 3.1% of MYFEMBREE-treated women as compared to 2.3% of placebo-treated women. In MYFEMBREE-treated women, serious adverse drug reactions included uterine myoma expulsion and menorrhagia experienced by one woman and uterine leiomyoma (prolapse), cholecystitis, and pelvic pain reported for one woman each.
Adverse Reactions Leading to Study Drug Discontinuation
In Studies L1 and L2, 3.9% of women treated with MYFEMBREE discontinued therapy due to adverse reactions, as compared to 4.3% receiving placebo. The most common adverse reaction leading to discontinuation of MYFEMBREE was uterine bleeding (1.2%) with an onset usually reported within the first 3 months of therapy.
Common Adverse Reactions
The most common adverse reactions reported in at least 3% of women treated with MYFEMBREE for heavy menstrual bleeding associated with uterine fibroids and at an incidence greater than placebo during double-blind placebo-controlled treatment are summarized below in Table 1.
Table 1: Adverse Reactions Occurring in 3% or More in Women with Heavy Menstrual Bleeding Associated with Uterine Fibroids Treated with MYFEMBREE in Studies L1 and L2
| Adverse Reaction | MYFEMBREE
(N = 254)
% | Placebo
(N = 256)
% |
|---|
|
|
|
| Vasomotor symptoms1 | 10.6
| 6.6
|
| Abnormal uterine bleeding2 | 6.3
| 1.2
|
| Alopecia
| 3.5
| 0.8
|
| Libido decreased3 | 3.1
| 0.4
|
In Study L1, more women experienced the adverse reaction of new or worsening hypertension with MYFEMBREE as compared to placebo (7.0% vs. 0.8%).
The most common adverse reactions reported during the extension trial, Study L3, were similar to those reported in the placebo-controlled trials.
Less Common Adverse Reactions
Adverse reactions reported in at least 2% and less than 3% of women with heavy menstrual bleeding associated with uterine fibroids in the MYFEMBREE treated group and greater incidence than placebo included irritability, dyspepsia, and breast cyst. Other important adverse reactions reported in MYFEMBREE-treated women included one serious reaction each of uterine myoma expulsion (0.4%) and uterine leiomyoma (prolapse) (0.4%).
Bone Loss
The effect of MYFEMBREE on BMD was assessed by DXA. The least squares mean percent changes from baseline in lumbar spine BMD at Month 6 in Studies L1 and L2 are presented below in Table 2.
Table 2: Mean Percent Change (On-Treatment) from Baseline in Lumbar Spine BMD in Women with Heavy Menstrual Bleeding Associated with Uterine Fibroids in Studies L1 and L2 at Month 6
| MYFEMBREE | Placebo |
|---|
|
| Number of subjects
| 254
| 256
|
Percent change from baseline
(95% CI)
| -0.23
(-0.64, 0.18)
| 0.18
(-0.21, 0.58)
|
| Treatment difference, %
| -0.42
|
In the open-label extension trial, Study L3, women received an additional 28 weeks of MYFEMBREE for a total of up to 52 weeks of treatment. Women from Study L3 showed continued bone loss at Months 6 and 12 when treated with up to 52 weeks of MYFEMBREE. The least squares mean percent changes from baseline in lumbar spine BMD at Months 6 and 12 are presented below in Table 3.
Table 3: Mean Percent Change (On-Treatment) from Baseline* in Lumbar Spine BMD at Month 6* and Month 12 for MYFEMBREE-Treated Women with Heavy Menstrual Bleeding Associated with Uterine Fibroids in Study L3
| Number of Women
(N = 163) |
|---|
| Month 6* | Month 12 |
|---|
|
|
Percent change from baseline*
(95% CI)
| -0.23
(-0.69, 0.24)
| -0.80
(-1.36, -0.25)
|
A separate concurrent prospective observational study enrolled 262 women with heavy menstrual bleeding associated with uterine fibroids who were age-matched to participants of Studies L1 and L2. While these women were not randomized to receive treatment for heavy menstrual bleeding associated with uterine fibroids, women were permitted to receive treatment from their provider during the clinical trials for this indication. Women underwent DXA scans at baseline, Month 6 and Month 12 to monitor for changes in BMD. The mean percent changes from baseline (95% CI) in lumbar spine BMD at Months 6 and 12 were 0.00 (-0.32, 0.31) and -0.41 (-0.77, -0.05), respectively.
A decline in lumbar spine BMD of > 3% was observed in 23% (30/132) of women who had a DXA scan following 12 months of MYFEMBREE treatment in Study L3 and in 17.4% (37/213) of untreated women in the Observational Uterine Fibroids Cohort. A decline of > 8% was seen in 0.8% (1/132) of women treated with MYFEMBREE who completed a DXA scan at Month 12 and in 0.9% (2/213) of untreated women in the Observational Uterine Fibroids Cohort.
In Studies L1, L2, and L3, four of women treated with MYFEMBREE experienced low trauma fractures (defined as a fall from standing height or less). Two women, one from Study L1 and one from Study L2, fractured after 117 and 166 days of treatment with MYFEMBREE. Two women in Study L3, both treated with relugolix monotherapy for 12 weeks prior to MYFEMBREE therapy, fractured after 149 and 164 days of treatment with MYFEMBREE.
Depression, Mood Disorders, and Suicidal Ideation
In Studies L1 and L2, MYFEMBREE was associated with adverse mood changes. A greater proportion of women treated with MYFEMBREE compared to placebo reported depression (including depression, mood swings, and depressed mood) (2.4% vs. 0.8%), irritability (2.4% vs. 0%), and anxiety (1.2% vs. 0.8%).
Resumption of Menstruation after Discontinuation
Post study menstrual status was available for 35 women in Study L1 and 30 women in Study L2 who were treated with MYFEMBREE and prematurely discontinued the study or did not continue into the long-term extension study. For these women, 100% (35/35) in Study L1 and 93.3% (28/30) in Study L2 resumed menses. The mean time from last dose to occurrence of menses was 36 days in Study L1 and 30.7 days in Study L2. Mean time to occurrence of menses was longer for women who achieved amenorrhea (40.6 days and 41.1 days in Studies L1 and L2, respectively) compared with women without amenorrhea (33.0 days and 26.6 days in Studies L1 and L2, respectively) in the last 35 days of treatment. After 12 months of treatment with MYFEMBREE (Study L1 or Study L2, then Study L3) 93.8% (61/65) of women resumed menses. Mean time from last dose of drug to occurrence of menses was 40.5 days. Mean time to occurrence of menses was longer in women who reported amenorrhea over the last 35 days of treatment compared with women without amenorrhea over the last 35 days of treatment (45.6 days vs. 32.6 days, respectively).
Women who did not have a return to menses included those who had surgery, used alternative medications associated with amenorrhea, entered menopause, and unknown cause.
Increases in Lipids
Lipid levels were assessed at baseline and Week 24/End of Treatment in Studies L1 and L2. Among women with normal total cholesterol (< 200 mg/dL) at baseline, increases to 200 to < 240 mg/dL were seen in 13.7% of women treated with MYFEMBREE as compared to 7.7% of women treated with placebo, and increases to ≥ 240 mg/dL were seen in 1.7% and 0.6% of MYFEMBREE- and placebo-treated women, respectively. For women with LDL < 130 mg/dL at baseline, increases to 130 to < 160 mg/dL, 160 to < 190 mg/dL and ≥ 190 mg/dL were seen in 9.3%, 1.5%, and 0.5% of women treated with MYFEMBREE as compared to 6.5%, 0.5% and 0% of women treated with placebo, respectively.
Moderate to Severe Pain Associated with Endometriosis
The safety of MYFEMBREE was evaluated in two placebo-controlled clinical trials, Study S1 and Study S2, in women with moderate to severe pain associated with endometriosis. In these trials, women received once daily one relugolix 40-mg tablet with one over-encapsulated tablet of E2 1 mg and NETA 0.5 mg (relugolix + E2/NETA), which is equivalent to one tablet of MYFEMBREE. Across the two trials, 418 women received MYFEMBREE once daily for 24 weeks, 416 women received placebo for 24 weeks, and 417 women received relugolix 40 mg monotherapy once daily for 12 weeks followed by MYFEMBREE for 12 weeks [see Clinical Studies (14)]. Of these, 799 women were treated with MYFEMBREE in an 80-week extension trial, Study S3, for a total treatment duration of up to 24 months. Demographics were similar across these trials; 91% were white, 6% were Black, and 12% were of Hispanic or Latino ethnicity. The mean age at study entry was 34 years (range 18 to 50 years).
Serious Adverse Reactions
In Studies S1 and S2, serious adverse reactions were reported in 2.9% of MYFEMBREE-treated women as compared to 2.2% of placebo-treated women. In MYFEMBREE-treated women, serious adverse reactions included uterine hemorrhage, suicidal ideation, cholelithiasis, and cholecystitis.
Adverse Reactions Leading to Study Drug Discontinuation
In Studies S1 and S2, 4.5% of MYFEMBREE-treated women discontinued therapy due to adverse reactions as compared to 2.9% of placebo-treated women. The most common adverse reaction (1.7%) leading to discontinuation in MYFEMBREE-treated women was mood-related disorders (including depression, mood swings, altered mood, affect lability, and suicidal ideation).
Common Adverse Reactions
The most common adverse reactions reported in at least 3% of women treated with MYFEMBREE for moderate to severe pain associated with endometriosis and with an incidence greater than placebo during Studies S1 and S2 are summarized below in Table 4.
Table 4: Adverse Reactions Occurring in 3% or More of Women with Moderate to Severe Pain Associated with Endometriosis Treated with MYFEMBREE
| Adverse Reaction | MYFEMBREE
(N = 418)
% | Placebo
(N = 416)
% |
|---|
|
|
|
|
| Headache
| 33.0
| 26.4
|
| Vasomotor symptoms1 | 13.2
| 7.2
|
| Mood disorders2 | 9.1
| 7.2
|
| Abnormal uterine bleeding3 | 6.7
| 4.6
|
| Nausea
| 6.0
| 4.1
|
| Toothache
| 5.5
| 2.4
|
| Back pain
| 4.8
| 2.9
|
| Decreased sexual desire and arousal4 | 4.3
| 1.2
|
| Arthralgia
| 3.6
| 2.2
|
| Fatigue
| 3.1
| 2.4
|
| Dizziness
| 3.1
| 1.2
|
The most common adverse reactions reported in the safety extension trial, Study S3, were similar to those reported in the placebo-controlled trials.
Less Common Adverse Reactions
Adverse reactions reported in at least 2% and less than 3% of women with moderate to severe pain associated with endometriosis in the MYFEMBREE group and with a greater incidence than placebo included diarrhea (2.4%), peripheral edema (2.2%), and vulvovaginal dryness (2.2%).
Bone Loss
The effect of MYFEMBREE on BMD was assessed by DXA. The least squares (LS) mean percent changes from baseline in lumbar spine BMD at Month 6 and for women with moderate to severe pain associated with endometriosis in Studies S1 and S2 are presented in Table 5 .
Table 5: LS Mean Percent Change (On-Treatment) from Baseline in Lumbar Spine BMD in Women with Moderate to Severe Pain Associated with Endometriosis at Month 6 in Studies S1 and S2
| Treatment Month 6 |
|---|
| MYFEMBREE | Placebo |
|---|
|
| Number of subjects
| 418
| 416
|
Percent change from baseline
(95% CI)
| -0.72
(-1.06, -0.38)
| 0.12
(-0.22, 0.47)
|
| Treatment difference, %
| -0.84
|
In the open-label extension, Study S3, women received an additional 80 weeks of MYFEMBREE for a total of up to 24 months of treatment. The least squares (LS) mean percent changes from baseline in lumbar spine BMD at Months 6, 12, and 24 for women treated with MYFEMBREE in Studies S1 and S2 and then continued MYFEMBREE for an additional 80 weeks in Study S3 are presented below in Table 6.
Table 6: LS Mean Percent Change (On-Treatment) from Baseline* in Lumbar Spine BMD at Months 6*, 12, and 24 for Women with Moderate to Severe Pain Associated with Endometriosis Treated with MYFEMBREE in Study S3
| Number of Women
(N = 277) |
|---|
Month 6*
(n=264) | Month 12
(n=228) | Month 24
(n=163) |
|---|
|
|
Percent change from baseline*
(95% CI)
| -0.91
(-1.30, -0.53)
| -0.81
(-1.26, -0.36)
| -0.45
(-1.03, 0.13)
|
Changes in bone mineral density with MYFEMBREE treatment beyond 24 months have not been elucidated.
A separate concurrent prospective observational study enrolled 452 women with moderate to severe pain associated with endometriosis who were age-matched to participants of Studies S1 and S2. While these women were not randomized to receive treatment for moderate to severe pain associated with endometriosis, women were permitted to receive treatment from their provider for this indication. Women underwent DXA scans at baseline and Months 6 and 12 to monitor for changes in BMD. The mean percent changes from baseline (95% CI) in lumbar spine BMD at Months 6 and 12 were 0.35 (0.13, 0.57) and 0.53 (0.24, 0.83), respectively.
In women with moderate to severe pain associated with endometriosis, a decline in lumbar spine BMD of > 3% from pre-treatment baseline was observed in 19.7% (45/228) of women who had a DXA scan following 12 months of MYFEMBREE treatment in Study S3 and in 9.1% (29/320) of untreated women in the Observational Endometriosis Cohort. A decline of > 7% to ≤ 8% from pre-treatment baseline was seen in 0.9% (2/228) of women treated with MYFEMBREE who completed a DXA scan at Month 12 in Study S3 and in 0.6% (2/320) of untreated women in the Observational Endometriosis Cohort.
Following 24 months of MYFEMBREE treatment in Study S3, a decline in lumbar spine BMD of > 3% from pre-treatment baseline occurred in 20.2% (33/163) of women and a decline of > 7% from pre-treatment baseline occurred in 2.5% (4/163) of women. At the femoral neck, a decline in BMD of >7% was observed in 1.8% (3/163) women, one of whom (0.6%) also had a decline in BMD of > 7% at the total hip. The maximum percent decline from pre-treatment baseline at the lumbar spine, femoral neck and total hip at Month 24 was 9.1%, 8.8% and 7.0%, respectively.
BMD loss may not be completely reversible after stopping treatment.
In Study S3, two women sustained fractures after falling. One woman, who was treated for almost 24 weeks with MYFEMBREE following 12 weeks of relugolix monotherapy, sustained a tibia/fibula fracture and one who was treated for 104 weeks with MYFEMBREE, sustained a wrist fracture 144 days after she discontinued MYFEMBREE. The impact of BMD loss on long-term bone health and future fracture risk in premenopausal women is unknown.
Suicidal Ideation and Mood Disorders (Including Depression)
In Studies S1 and S2, a greater proportion of women treated with MYFEMBREE compared with placebo reported mood disorders (including depression) (9.1% vs. 7.2%).
In addition, cases of suicidal ideation were reported in the safety extension trial, Study S3.
Resumption of Menstruation after Discontinuation
Post-study menstrual status was available for 55 women in Study S1 and 59 women in Study S2 who were treated with MYFEMBREE and either prematurely discontinued the study or did not continue into the extension study. For these women, 83.6% (46/55) in Study S1 and 84.7% (50/59) in Study S2 resumed menses. The mean time from last dose to occurrence of menses was 27.1 days in Study S1 and 39.2 days in Study S2. Mean time to occurrence of menses was longer for women who achieved amenorrhea (34.3 days and 42.8 days in Studies S1 and S2, respectively) compared with women without amenorrhea (21.0 days and 32.1 days in Studies S1 and S2, respectively) in the last 28 days of treatment. After 12 months of treatment with MYFEMBREE (Study S1 or Study S2, then Study S3), 97.9% (46/47) of women resumed menses. Mean time from last dose of drug to occurrence of menses was 36.7 days.
Women who did not have a return to menses included those who had surgery, used alternative medications associated with amenorrhea, or became pregnant.
Increases in Lipids
Lipid levels were assessed at baseline and Week 24/End of Treatment in Studies S1 and S2. Among women with normal total cholesterol (< 200 mg/dL) at baseline, increases to ≥ 200 to < 240 mg/dL were seen in 13.6% (41/302) of MYFEMBREE- treated women as compared to 9.3% (27/289) of placebo-treated women, and increases to ≥ 240 mg/dL were seen in 0.7% (2/302) of MYFEMBREE-treated women as compared to 1.0% (3/289) of placebo-treated women. For women with LDL < 130 mg/dL at baseline, increases to 130 to < 160 mg/dL, 160 to < 190 mg/dL and ≥ 190 mg/dL were seen in 8.0%, 0.3%, and 0% of MYFEMBREE-treated women as compared to 7.6%, 0% and 0% of placebo-treated women. Among women with normal HDL at baseline (≥ 60 mg/dL), declines to 40 to < 60 mg/dL occurred in 22.2% (49/221) of MYFEMBREE-treated women as compared to 12.2% (27/221) of placebo-treated women.
P-gp Inhibitors
Co-administration of MYFEMBREE with P-gp inhibitors increases the AUC and maximum concentration (Cmax) of relugolix [see Clinical Pharmacology (12.3)] and may increase the risk of adverse reactions associated with MYFEMBREE. Avoid use of MYFEMBREE with oral P-gp inhibitors.
If use is unavoidable, take MYFEMBREE first, separate dosing by at least 6 hours, and monitor patients for adverse reactions [see Dosage and Administration (2.4)].
Combined P-gp and Strong CYP3A Inducers
Use of MYFEMBREE with combined P-gp and strong CYP3A inducers decreases the AUC and Cmax of relugolix, estradiol, and/or norethindrone [see Clinical Pharmacology (12.3)] and may decrease the therapeutic effects of MYFEMBREE. Avoid use of MYFEMBREE with combined P-gp and strong CYP3A inducers.
Pregnancy Exposure Registry
There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to MYFEMBREE during pregnancy. Pregnant females exposed to MYFEMBREE and healthcare providers are encouraged to call the MYFEMBREE Pregnancy Exposure Registry at 1-855-428-0707.
Risk Summary
MYFEMBREE is contraindicated in pregnancy [see Contraindications (4) and Warnings and Precautions (5.9)]. Based on findings from animal studies and its mechanism of action, MYFEMBREE may cause early pregnancy loss. Discontinue MYFEMBREE if pregnancy occurs during treatment [see Warnings and Precautions (5.9) and Clinical Pharmacology (12.1)].
The limited human data with the use of MYFEMBREE in pregnant women are insufficient to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes [see Data].
In animal reproduction studies, oral administration of relugolix in pregnant rabbits during organogenesis resulted in spontaneous abortion and total litter loss at relugolix exposures about half those at the maximum recommended human dose (MRHD) of 40 mg. In both rabbits and rats, no fetal malformations were present at any dose level tested which were associated with relugolix exposures about half and approximately 300 times exposures in women at the MRHD, respectively [see Data].
Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to estrogens and progestins before conception or during early pregnancy.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. There are insufficient data to conclude whether the presence of uterine fibroids or endometriosis reduces the likelihood of achieving pregnancy or increases the risk of adverse pregnancy outcomes. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the United States general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies are 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
In an embryo-fetal development study, oral administration of relugolix to pregnant rabbits during the period of organogenesis (Days 6 to 18 of gestation) resulted in abortion, total litter loss, or decreased number of live fetuses at a dose of 9 mg/kg/day (about half the human exposure at the maximum recommended human dose [MRHD] of 40 mg daily, based on AUC). No treatment related malformations were observed in surviving fetuses. No treatment related effects were observed at 3 mg/kg/day (about 0.1-fold the MRHD) or lower. The binding affinity of relugolix for rabbit GnRH receptors is unknown.
In a similar embryo-fetal development study, oral administration of relugolix to pregnant rats during the period of organogenesis (Days 6 to 17 of gestation) did not affect pregnancy status or fetal endpoints at doses up to 1000 mg/kg/day (300 times the MRHD), a dose at which maternal toxicity (decreased body weight gain and food consumption) was observed. A no observed adverse effect level (NOAEL) for maternal toxicity was 200 mg/kg/day (86 times the MRHD). In rats, the binding affinity of relugolix for GnRH receptors is more than 1000-fold lower than that in humans, and this study represents an assessment of non-pharmacological targets of relugolix during pregnancy. No treatment related malformations were observed up to 1000 mg/kg/day.
In a pre- and postnatal developmental study in pregnant and lactating rats, oral administration of relugolix to rats during late pregnancy and lactation (Day 6 of gestation to Day 20 of lactation) had no effects on pre- and postnatal development at doses up to 1000 mg/kg/day (300 times the MRHD), a dose in which maternal toxicity was observed (effects on body weight gain). A NOAEL for maternal toxicity was 100 mg/kg/day (34 times the MRHD).
Risk Summary
Detectable amounts of estrogen and progestin have been identified in the breast milk of women receiving estrogen plus progestin therapy and can reduce milk production in breast-feeding women. This reduction can occur at any time but is less likely to occur once breast-feeding is well established.
Relugolix was detected in human breast milk. In a single dose milk-only lactation study in 8 healthy adult lactating women, the mean total amount of relugolix recovered in human breast milk over the first 24 hours was 0.0031 mg and over 120 hours (5 days) was 0.0042 mg following a single, oral, maternal dose of 40 mg. The mean calculated daily infant dose was 0.0006 mg/kg/day using 0.0031mg (the amount recovered in human breast milk over the first 24 hours). The relative infant dose was 0.105% of the maternal weight-adjusted dose of 40 mg.
There are no data on the effects of relugolix or its metabolites on the breastfed child, or the effects on milk production.
The developmental and health benefits of breast-feeding should be considered along with the mother's clinical need for MYFEMBREE and any potential adverse effects on the breastfed child from MYFEMBREE or from the underlying maternal condition.
Pregnancy Testing
MYFEMBREE may delay the ability to recognize pregnancy because it may reduce the intensity, duration, and amount of menstrual bleeding [see Warnings and Precautions (5.8)]. Exclude pregnancy before initiating treatment with MYFEMBREE. Perform pregnancy testing if pregnancy is suspected during treatment with MYFEMBREE and discontinue treatment if pregnancy is confirmed [see Contraindications (4) and Warnings and Precautions (5.8)].
Contraception
Advise women of reproductive potential to use effective non-hormonal contraception during treatment with MYFEMBREE and for at least 1 week following discontinuation. Avoid concomitant use of hormonal contraceptives with MYFEMBREE. The use of estrogen-containing hormonal contraceptives may increase the risk of estrogen-associated adverse events and is expected to decrease the efficacy of MYFEMBREE [see Warnings and Precautions (5.8)].
Cardiac Electrophysiology
At a dose 9 times the maximum approved recommended dose of relugolix, the QT interval was not prolonged to a clinically relevant extent.
The effect of estradiol and norethindrone acetate (two of the components of MYFEMBREE) on the QTc interval has not been studied.
Absorption
The mean (%CV) absolute bioavailability of relugolix is 12% (62%).
Effect of Food
The AUC0-inf and Cmax of relugolix decreased by 38% and 55%, respectively, after administration of MYFEMBREE following consumption of a high-fat, high-calorie meal (i.e., 800-1000 calorie meal in which 50% of calories are derived from fat) compared with the fasted state; however, the decrease in exposure to relugolix is considered not to be clinically meaningful. No clinically meaningful effects of food on the exposure to estradiol or norethindrone were observed.
Distribution
Plasma protein binding of relugolix is 68% to 71%, primarily to albumin and to a lesser extent to α1-acid glycoprotein. The mean blood-to-plasma ratio is 0.78. Estradiol circulates in the blood bound to SHBG (36% to 37%) and to albumin (61%), while only approximately 1% to 2% is unbound. Norethindrone also binds to a similar extent to SHBG (36%) and to albumin (61%).
Elimination
After administration of a single dose of MYFEMBREE, the mean (SD) terminal phase elimination half-life (t1/2) of relugolix, estradiol, and norethindrone are 61.5 (13.2) hours, 16.6 (7.7) hours, and 10.9 (3.1) hours, respectively.
Metabolism
Relugolix is metabolized primarily by CYP3A and to a lesser extent by CYP2C8 in vitro.
Estradiol is converted reversibly to estrone, and both can be converted to estriol, which is a major urinary metabolite. Estrogens also undergo enterohepatic recirculation due to sulfate and glucuronide conjugation in the liver, biliary secretion of conjugates into the intestine, and hydrolysis in the intestine followed by reabsorption.
Norethindrone undergoes extensive biotransformation, primarily by reduction, in addition to sulfation, glucuronidation, and oxidation, respectively, by sulfotransferases (SULTs), glucuronosyltransferases (UGTs), and CYP enzymes, including CYP3A4. The majority of metabolites in the circulation are sulfates, with glucuronides accounting for most of the urinary metabolites.
Excretion
After oral administration of a single 80 mg radiolabeled dose of relugolix, approximately 81% of the radioactivity was recovered in feces (4.2% as unchanged) and 4.1% in urine (2.2% as unchanged).
Estradiol is excreted in the urine as glucuronide and sulfate conjugates. Norethindrone is primarily excreted in urine as various polar metabolites.
Specific Populations
No clinically significant differences in the pharmacokinetics of relugolix were observed based on age (19 to 53 years), race/ethnicity (Asian [49%], White [24%], Black/African American [24%]), body weight (38 to 144 kg), mild to severe renal impairment (creatinine clearance [CLcr] 15 to 89 mL/min, as estimated by the Cockcroft-Gault equation), or mild or moderate hepatic impairment (Child-Pugh A or B). The effects of severe hepatic impairment (Child-Pugh C) or end-stage renal disease with or without hemodialysis on the pharmacokinetics of relugolix have not been studied.
The effects of renal or hepatic impairment on the pharmacokinetics of estradiol or norethindrone have not been studied. However, estradiol blood concentrations are expected to be increased in patients with hepatic impairment compared to patients with normal hepatic function.
Drug Interaction Studies
Clinical Studies
Combined P-gp and Moderate CYP3A Inhibitor: Co-administration of MYFEMBREE with erythromycin (P-gp and moderate CYP3A inhibitor) increased the AUC and Cmax of relugolix by 4.1-fold and 3.8- fold, respectively. No clinically meaningful differences in the pharmacokinetics of unconjugated estradiol, total estrone, unconjugated estrone, and norethindrone were observed.
- Combined P-gp and Strong CYP3A Inducer: Co-administration with rifampin (P-gp and strong CYP3A inducer) decreased the AUC and Cmax of relugolix by 55% and 23%, respectively.
- Other Drugs: No clinically significant differences in the pharmacokinetics of relugolix were observed when co-administered with voriconazole (strong CYP3A inhibitor), fluconazole (moderate CYP3A inhibitor), or atorvastatin (weak CYP3A inhibitor). No clinically significant differences in the pharmacokinetics of midazolam (sensitive CYP3A substrate), rosuvastatin (BCRP substrate), or dabigatran etexilate (P-gp substrate) were observed upon co-administration with relugolix.
In Vitro Studies
- Cytochrome P450 (CYP) Enzymes: Relugolix is a substrate of CYP3A and CYP2C8. Relugolix is an inducer of CYP3A and CYP2B6, but not an inducer of CYP1A2. Relugolix is not an inhibitor of CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, or CYP3A4.
- Transporter Systems: Relugolix is a substrate of P-gp, but not a substrate of BCRP. Relugolix is an inhibitor of BCRP and P-gp, but not an inhibitor of OATP1B1, OATP1B3, OATP2B1, OAT1, OAT3, OCT2, MATE1, MATE2-K, or BSEP.
Carcinogenesis
Relugolix
Two-year carcinogenicity studies were conducted in mice at oral relugolix doses up to 100 mg/kg/day and in rats at doses up to 600 mg/kg/day. Relugolix was not carcinogenic in mice or rats at exposures up to approximately 142 or 423 times, respectively, the exposure in human females at the MRHD of 40 mg daily, based on AUC.
E2/NETA
Long-term continuous administration of natural and synthetic estrogens in certain animal species increases the frequency of carcinomas of the breast, uterus, cervix, vagina, testis, and liver.
Mutagenesis
Relugolix was not mutagenic in the in vitro bacterial reverse mutation (Ames) assay or clastogenic in the in vitro chromosomal aberration assay in Chinese hamster lung cells or the in vivo rat bone marrow micronucleus assay.
Impairment of Fertility
In a fertility study in rats, no effect on female fertility was observed at up to 1000 mg/kg/day (300 times the MRHD of 40 mg daily in women). In rats, the binding affinity of relugolix for GnRH receptors is greater than 1000-fold less than in humans, and this study represents an assessment of non-pharmacological targets of relugolix.
In human GnRH-receptor knock-in mice, administration of relugolix at oral doses of 100 mg/kg and above twice daily to female mice induced a constant diestrus phase and decreased ovarian and uterine weights, effects which were reversible following cessation of treatment. In male knock-in mice, oral administration of relugolix decreased prostate and seminal vesicle weights at doses 3 mg/kg and above twice daily for 28 days, effects which were reversible, except for testis weight, which did not fully recover within 28 days after drug withdrawal.
In a 39-week toxicology study in monkeys, a decrease in the frequency of menses was observed in female monkeys at 50 mg/kg/day (99 times the MRHD of 40 mg daily in women, based on AUC), which was partially reversed following a 13-week recovery period. There were no significant effects on male reproductive organs at oral relugolix doses up to 50 mg/kg/day (approximately 53 times the human exposure at a dose of 120 mg daily in men, based on AUC).
Amenorrhea
In Studies L1 and L2, 50.0% and 50.4% of women treated with MYFEMBREE, respectively, achieved amenorrhea as compared to 6.2% and 3.1% treated with placebo, respectively, over the last 35 days of treatment.
Percent Change in MBL Volume
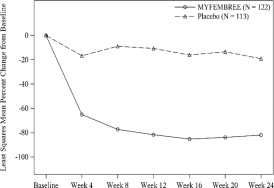
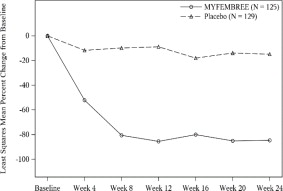
The mean MBL volumes in Studies L1 and L2 at baseline were 243.8 mL and 246.7 mL in the MYFEMBREE group and 223.2 mL and 211.8 mL in the placebo group, respectively. The mean reduction in MBL volume from baseline to Week 24 in the MYFEMBREE group was 82.0% in Study L1 and 84.3% in Study L2, which was greater than placebo (19.1% and 15.1%, respectively).
Reductions in MBL volume for MYFEMBREE and placebo groups are depicted in Figure 1.
Figure 1: Percent Change from Baseline in Menstrual Blood Loss Over 24 weeks
Hemoglobin Levels
For efficacy, a hemoglobin response was defined as a hemoglobin increase > 2 g/dL from baseline to Week 24 in the subgroup of women with anemia at baseline (hemoglobin ≤ 10.5 g/dL). A statistically higher proportion treated with MYFEMBREE compared with placebo had > 2 g/dL improvement in hemoglobin levels, see Table 9.
Table 9: Proportion of Women with Baseline Hgb ≤ 10.5 and > 2 g/dL Improvement in Hemoglobin Levels from Baseline at Week 24
| Study L1 | Study L2 |
|---|
MYFEMBREE
n=43
(N = 122) | Placebo
n=29
(N = 113) | MYFEMBREE
n=40
(N = 125) | Placebo
n=53
(N = 129) |
|---|
|
|
|
| % at Week 24
| 44.2%
| 17.2%
| 55.0%
| 5.7%
|
Difference from placebo, %
5% CI
p-value
| 26.9%
(6.7%, 47.2%)
0.0177
| 49.3%
(32.7%, 66.0%)
<0.0001
|
Recurrence of Heavy Menstrual Bleeding After Discontinuation of MYFEMBREE
In a randomized withdrawal study (L4), 229 women from the open label extension Study L3 were rerandomized to either continue blinded treatment with MYFEMBREE or withdrawal of therapy (placebo) for an additional 52 weeks. The median time to return to heavy menstrual bleeding among women randomized to placebo (treatment withdrawal) was 5.9 weeks.
Reduction in DYS and NMPP NRS Scores
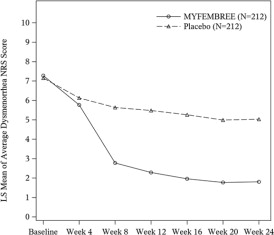
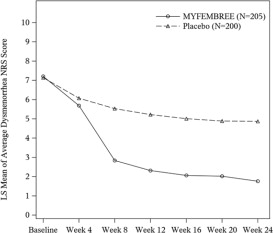
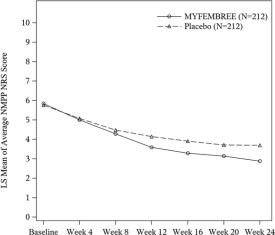
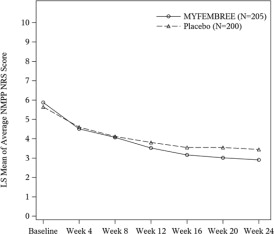
Women treated with MYFEMBREE had a greater reduction in DYS and NMPP NRS scores as compared to placebo from baseline to Week 24 in both Studies S1 and S2 (Figure 2 and Figure 3).
Figure 2: Mean DYS NRS Scores in Study S1 and Study S2 over 24 Weeks
Figure 3: Mean NMPP NRS Scores in Study S1 and Study S2 over 24 Weeks
Reduction in EHP-30 Pain Domain Scores
The impact of moderate to severe pain associated with endometriosis was evaluated using the pain domain from the Endometriosis Health Profile-30 (EHP-30), where the domain score (normalized) ranges from 0 to 100 with a higher score representing greater impact of pain on activities.
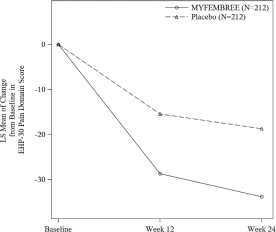
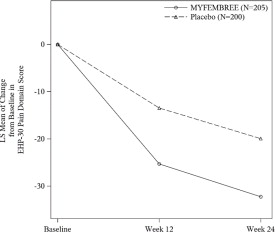
Women taking MYFEMBREE reported an improvement from baseline in EHP-30 pain domain score compared to placebo at Week 24 in both Studies S1 and S2 (Study S1: -33.8 vs. -18.7 with a treatment difference of -15.1 [95% CI: -19.7, -10.5] and Study S2: -32.2 vs. -20.0 with a treatment difference of -12.3 [95% CI: -16.7, -7.8]). Least squares mean changes in EHP-30 pain domain scores over time are shown in Figure 4.
Figure 4: Mean Change in EHP-30 Pain Domain Scores in Studies S1 and S2 over 24 Weeks
Reduction in Dyspareunia
Dyspareunia associated with endometriosis was evaluated in a subgroup of women who engaged in sexual activity with vaginal intercourse at baseline and during treatment (68% of enrolled women). Dyspareunia (pain during sexual intercourse) was assessed daily using an 11-point NRS ranging from 0 (“no pain”) to 10 (“pain as bad as you can imagine”). In Studies S1 and S2, women treated with MYFEMBREE had a greater reduction in dyspareunia from baseline to Week 24 compared with placebo [LS mean change in Study S1: -2.4 vs. -1.7, with a treatment difference of -0.7 (95% CI: -1.3, -0.1); in Study S2: -2.4 vs. -1.9, with a treatment difference of -0.5 (95% CI: -1.0, 0.0)].
Use of Opioid Rescue Analgesics
The opioid analgesics used in the studies were tramadol 50 mg, codeine 30 mg, tramadol/acetaminophen (TRM/APAP) 37.5/325 mg, codeine/APAP at strengths of 15/500 mg, 30/300 mg, and 30/500 mg, and hydrocodone/acetaminophen 5/325 mg. The opioid rescue analgesics used at baseline, Month 3, and Month 6 are shown in Table 11.
The clinical relevance of these data has not been demonstrated.
Table 11: Opioid Rescue Analgesic Use in Studies S1 and S2
| Study S1 | Study S2 |
|---|
MYFEMBREE
(N = 212) | Placebo
(N = 212) | MYFEMBREE
(N = 205) | Placebo
(N = 200) |
|---|
|
|
|
Tablets per month at baseline
Mean (SD)
Median (Min, Max)
|
9.1 (12.36)
4.2
(0.6, 60.7)
|
11.7 (11.95)
7.2
(0.5, 54.6)
|
9.0 (13.51)
5.6
(0.7, 106.9)
|
10.0 (12.82)
6.1
(0.4, 86.3)
|
Tablets per month at Month 3
Mean (SD)
Median (Min, Max)
|
3.9 (7.98)
0.0
(0.0, 32.0)
|
8.2 (11.48)
3.2
(0.0, 40.8)
|
3.4 (8.26)
0.0
(0.0, 57.6)
|
7.5 (23.49)
2.4
(0.0, 215.2)
|
Tablets per month at Month 6
Mean (SD)
Median (Min, Max)
|
4.8 (10.38)
0.0
(0.0, 45.4)
|
10.7 (28.93)
3.2
(0.0, 40.8)
|
2.4 (5.02)
0.0
(0.0, 28.0)
|
5.6 (14.16)
1.2
(0.0, 120.8)
|
| Number and % of subjects on any dose of opioid rescue at baseline who were off opioid at Month 3*
| 33/64
(51.6%)
| 10/56
(17.9%)
| 46/100
(46.0%)
| 27/94
(28.7%)
|
| Number and % of subjects on any dose of opioid rescue at baseline who were off opioid at Month 6*
| 39/64
(60.9%)
| 18/56
(32.1%)
| 65/100
(65.0%)
| 38/94
(40.4%)
|
| Number and % of subjects not on opioid rescue at baseline who were on opioid at Month 3#
| 4/148
(2.7%)
| 10/156
(6.4%)
| 6/105
(5.7%)
| 15/106
(14.2%)
|
| Number and % of subjects not on any dose of opioid rescue at baseline who were on opioid at Month 6#
| 5/148
(3.4%)
| 12/156
(7.7%)
| 2/105
(1.9%)
| 12/106
(11.3%)
|
Thromboembolic Disorders and Vascular Events
Advise patients that use of estrogen and progestin combinations may increase the risk of venous and arterial thrombotic/thromboembolic events, especially in women at high risk for these events [see Boxed Warning, Contraindications (4) and Warnings and Precautions (5.1)].
Bone Loss
Advise patients about the risk of bone loss. Advise patients that supplementary calcium and vitamin D may be beneficial if dietary intake of calcium and vitamin D is not adequate. Advise women that oral iron supplementation should not be taken at the same time as calcium and vitamin D [see Warnings and Precautions (5.2) and Adverse Reactions (6.1)].
Suicidal Ideation and Mood Disorders (Including Depression)
Advise patients that depression, mood disorders, and suicidal ideation may occur with MYFEMBREE use. Instruct women with new onset or worsening depression, anxiety, or other mood changes to promptly seek medical attention [see Warnings and Precautions (5.4) and Adverse Reactions (6.1)].
Hepatic Impairment and Transaminase Elevations
Advise women to promptly seek medical attention in case of signs or symptoms that may reflect liver injury, such as jaundice [see Warnings and Precautions (5.5)].
Change in Menstrual Bleeding Pattern and Reduced Ability to Recognize Pregnancy
Advise patients that MYFEMBREE may delay the recognition of pregnancy because it may reduce the duration and amount of menstrual bleeding. Advise patients to use effective non-hormonal contraception while taking MYFEMBREE and to discontinue MYFEMBREE if pregnancy is diagnosed [see Warnings and Precautions (5.8)]. Advise pregnant patients that there is a pregnancy registry that monitors pregnancy outcomes in women exposed to MYFEMBREE during pregnancy [see Use in Specific Populations (8.1, 8.3)].
Alopecia
Advise women with uterine fibroids that alopecia, hair loss, and hair thinning in no specific pattern may occur with MYFEMBREE. Advise these women that hair loss and hair thinning may not resolve completely after stopping MYFEMBREE. Advise these women to contact their healthcare provider if they have concerns about changes to their hair [see Warnings and Precautions (5.11) and Adverse Reactions (6.1)].
Females of Reproductive Potential
Advise women to use effective non-hormonal contraception while taking MYFEMBREE and for one week after discontinuing treatment and to discontinue MYFEMBREE if pregnancy is confirmed. Advise pregnant patients that there is a pregnancy registry that monitors pregnancy outcomes in women exposed to MYFEMBREE during pregnancy [see Use in Specific Populations (8.1, 8.3)].
Drug Interactions
Advise women to report their use of any other prescription or nonprescription medications or dietary supplements. Co-administration with certain drugs may decrease the therapeutic effects of MYFEMBREE [see Drug Interactions (7.1)].
Administration Instructions
- Advise women to begin taking MYFEMBREE as soon as possible after the start of menses but no later than 7 days after menses has started [see Dosage and Administration (2.2)].
- Advise women to take any missed dose of MYFEMBREE as soon as possible the same day and then resume regular dosing the next day at the usual time [see Dosage and Administration (2.3)].
- Advise women taking oral P-gp inhibitors to take MYFEMBREE first and separate dosing by at least 6 hours [see Dosage and Administration (2.4)].
Manufactured by Patheon Inc., 2100 Syntex Court, Mississauga, Ontario L5N 7K9, Canada
Distributed by: Sumitomo Pharma America, Inc., 84 Waterford Drive, Marlborough, MA 01752
214846 MS 008