Opioid-Induced Hyperalgesia (OIH) occurs when an opioid analgesic paradoxically causes an increase in pain, or an increase in sensitivity to pain. This condition differs from tolerance, which is the need for increasing doses of opioids to maintain a defined effect [see Dependence (9.3)]. Symptoms of OIH include (but may not be limited to) increased levels of pain upon opioid dosage increase, decreased levels of pain upon opioid dosage decrease, or pain from ordinarily non-painful stimuli (allodynia). These symptoms may suggest OIH only if there is no evidence of underlying disease progression, opioid tolerance, opioid withdrawal, or addictive behavior.
Cases of OIH have been reported, both with short-term and longer-term use of opioid analgesics. Though the mechanism of OIH is not fully understood, multiple biochemical pathways have been implicated. Medical literature suggests a strong biologic plausibility between opioid analgesics and OIH and allodynia. If a patient is suspected to be experiencing OIH, carefully consider appropriately decreasing the dose of the current opioid analgesic or opioid rotation (safely switching the patient to a different opioid moiety) [see Dosage and Administration (2.6), Warnings and Precautions (5.12)].
Less Frequently Observed Adverse Reactions
Cardiac disorders: tachycardia, bradycardia, palpitations
Eye disorders: vision blurred, diplopia, miosis, visual impairment
Gastrointestinal disorders: constipation, ileus, diarrhea, abdominal pain
General disorders and administration site conditions: weakness, feeling abnormal, chills, injection site urticaria, fatigue, injection site reactions, peripheral edema
Hepatobiliary disorders: biliary colic
Immune system disorders: anaphylactic reactions, hypersensitivity reactions
Investigations: hepatic enzymes increased
Metabolism and nutrition disorders: decreased appetite
Musculoskeletal and connective tissue disorders: muscle rigidity
Nervous system disorders: headache, tremor, paraesthesia, nystagmus, increased intracranial pressure, syncope, taste alteration, involuntary muscle contractions, presyncope, convulsion, drowsiness, dyskinesia, hyperalgesia, lethargy, myoclonus, somnolence
Psychiatric disorders: agitation, mood altered, nervousness, anxiety, depression, hallucination, disorientation, insomnia, abnormal dreams
Renal and urinary disorders: urinary retention, urinary hesitation, antidiuretic effects
Reproductive system and breast disorders: erectile dysfunction
Respiratory, thoracic, and mediastinal disorders: bronchospasm, laryngospasm, dyspnea, oropharyngeal swelling
Skin and subcutaneous tissue disorders: injection site pain, urticaria, rash, hyperhidrosis
Vascular disorders: flushing, hypotension, hypertension
Serotonin syndrome: Cases of serotonin syndrome, a potentially life-threatening condition, have been reported during concomitant use of opioids with serotonergic drugs.
Adrenal insufficiency: Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Anaphylaxis: Anaphylaxis has been reported with ingredients contained in DILAUDID INJECTION.
Androgen deficiency: Cases of androgen deficiency have occurred with use of opioids for an extended period of time [see Clinical Pharmacology (12.2)].
Hyperalgesia and Allodynia: Cases of hyperalgesia and allodynia have been reported with opioid therapy of any duration [see Warnings and Precautions (5.5)]
Hypoglycemia: Cases of hypoglycemia have been reported in patients taking opioids. Most reports were in patients with at least one predisposing risk factor (e.g., diabetes).
Opioid-induced esophageal dysfunction (OIED): Cases of OIED have been reported in patients taking opioids and may occur more frequently in patients taking higher doses of opioids, and/or in patients taking opioids longer term [see Warnings and Precautions (5.10)].
Adverse Reactions from Observational Studies
A prospective, observational cohort study estimated the risks of addiction, abuse, and misuse in patients initiating long-term use of Schedule II opioid analgesics between 2017 and 2021. Study participants included in one or more analyses had been enrolled in selected insurance plans or health systems for at least one year, were free of at least one outcome at baseline, completed a minimum number of follow-up assessments, and either: 1) filled multiple extended-release/long-acting opioid analgesic prescriptions during a 90-day period (n=978); or 2) filled any Schedule II opioid analgesic prescriptions covering at least 70 of 90 days (n=1,244). Those included also had no dispensing of the qualifying opioids in the previous 6 months.
Over 12 months:
- approximately 1% to 6% of participants across the two cohorts newly met criteria for addiction, as assessed with two validated interview-based measures of moderate-to-severe opioid use disorder based on Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5) criteria, and
- approximately 9% and 22% of participants across the two cohorts newly met criteria for prescription opioid abuse and misuse [defined in Drug Abuse and Dependence (9.2)], respectively, as measured with a validated self-reported instrument.
A retrospective, observational cohort study estimated the risk of opioid-involved overdose or opioid overdose-related death in patients with new long-term use of Schedule II opioid analgesics from 2006 through 2016 (n=220,249). Included patients had been enrolled in either one of two commercial insurance programs, one managed care program, or one Medicaid program for at least 9 months. New long-term use was defined as having Schedule II opioid analgesic prescriptions covering at least 70 days’ supply over the 3 months prior to study entry and none during the preceding 6 months. Patients were excluded if they had an opioid-involved overdose in the 9 months prior to study entry. Overdose was measured using a validated medical code-based algorithm with linkage to the National Death Index database. The 5-year cumulative incidence estimates for opioid-involved overdose or opioid overdose-related death ranged from approximately 1.5% to 4% across study sites, counting only the first event during follow-up. Approximately 17% of first opioid overdoses observed over the entire study period (5-11 years, depending on the study site) were fatal. Higher baseline opioid dose was the strongest and most consistent predictor of opioid-involved overdose or opioid overdose-related death. Study exclusion criteria may have selected patients at lower risk of overdose, and substantial loss to follow-up (approximately 80%) also may have biased estimates.
The risk estimates from the studies described above may not be generalizable to all patients receiving opioid analgesics, such as those with exposures shorter or longer than the duration evaluated in the studies.
Risk Summary
Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome [see Warnings and Precautions (5.4)]. There are no available data with DILAUDID INJECTION in pregnant women to inform a drug-associated risk for major birth defects and miscarriage or adverse maternal outcomes. There are adverse outcomes reported with fetal exposure to opioid analgesics (see Clinical Considerations).
In animal reproduction studies, reduced postnatal survival of pups, and decreased body weight were noted following oral treatment of pregnant rats with hydromorphone during gestation and through lactation at doses 0.8 times the human daily dose of 24 mg/day (HDD), respectively. In published studies, neural tube defects were noted following subcutaneous injection of hydromorphone to pregnant hamsters at doses 6.4 times the HDD and soft tissue and skeletal abnormalities were noted following subcutaneous continuous infusion of 3 times the HDD to pregnant mice. No malformations were noted at 4 or 40.5 times the HDD in pregnant rats or rabbits, respectively [see Data]. Based on animal data, advise pregnant women of the potential risk to a fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Risk Summary
Low levels of opioid analgesics have been detected in human milk. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for DILAUDID INJECTION and any potential adverse effects on the breastfed infant from DILAUDID INJECTION or from the underlying maternal condition.
Clinical Considerations
Monitor infants exposed to DILAUDID INJECTION through breast milk for excess sedation and respiratory depression. Withdrawal symptoms can occur in breastfed infants when maternal administration of hydromorphone is stopped, or when breast-feeding is stopped.
Infertility
Use of opioids for an extended period of time may cause reduced fertility in females and males of reproductive potential. It is not known whether these effects on fertility are reversible [see Adverse Reactions (6), Clinical Pharmacology (12.2), Nonclinical Toxicology (13.1)].
Clinical Presentation
Acute overdose with hydromorphone can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, hypoglycemia, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis, rather than miosis, may be seen with hypoxia in overdose situations [see Clinical Pharmacology (12.2)]. Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication.
Treatment of Overdose
In case of overdose, priorities are the reestablishment of a patent airway and protected airway and institution of assisted or controlled ventilation, if needed. Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or arrhythmias will require advanced life-support measures.
For clinically significant respiratory or circulatory depression secondary to hydromorphone overdose, administer an opioid overdose reversal agent such as naloxone or nalmefene.
Because the duration of opioid reversal is expected to be less than the duration of hydromorphone in DILAUDID INJECTION, carefully monitor the patient until spontaneous respiration is reliably reestablished. If the response to an opioid overdose reversal agent is suboptimal or only brief in nature, administer additional reversal agent as directed by the product's prescribing information.
In an individual physically dependent on opioids, administration of the recommended usual dosage of the opioid overdose reversal agent will precipitate an acute withdrawal syndrome. The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the reversal agent administered. If a decision is made to treat serious respiratory depression in the physically dependent patient, administration of the reversal agent should be initiated with care and by titration with smaller than usual doses of the reversal agent.
Effects on the Central Nervous System
Hydromorphone produces respiratory depression by direct effect on brain stem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation.
Hydromorphone causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origin may produce similar findings). Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations.
Effects on the Gastrointestinal Tract and Other Smooth Muscle
Hydromorphone causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm, resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED).
Effects on the Cardiovascular System
Hydromorphone produces peripheral vasodilation which may result in orthostatic hypotension or syncope, manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes, and sweating and/or orthostatic hypotension.
Effects on the Endocrine System
Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans [see Adverse Reactions (6)]. They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon.
Use of opioids for an extended period of time may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date [see Adverse Reactions (6)].
Effects on the Immune System
Opioids have been shown to have a variety of effects on components of the immune system in in vitro and animal models. The clinical significance of these findings is unknown. Overall, the effects of opioids appear to be modestly immunosuppressive.
Concentration–Efficacy Relationships
The minimum effective analgesic concentration will vary widely among patients, especially among patients who have been previously treated with opioid agonists. The minimum effective analgesic concentration of hydromorphone for any individual patient may increase over time due to an increase in pain, the development of a new pain syndrome, and/or the development of analgesic tolerance [see Dosage and Administration (2.1, 2.2)].
Concentration–Adverse Reaction Relationships
There is a relationship between increasing hydromorphone plasma concentration and increasing frequency of dose-related opioid adverse reactions such as nausea, vomiting, CNS effects, and respiratory depression. In opioid-tolerant patients, the situation may be altered by the development of tolerance to opioid-related adverse reactions [see Dosage and Administration (2.1, 2.2)].
Distribution
At therapeutic plasma levels, hydromorphone is approximately 8-19% bound to plasma proteins. After an intravenous bolus dose, the steady state of volume of distribution [mean (%CV)] is 302.9 (32%) liters.
Elimination
The systemic clearance is approximately 1.96 (20%) liters/minute. The terminal elimination half-life of hydromorphone after an intravenous dose is about 2.3 hours.
Metabolism
Hydromorphone is extensively metabolized via glucuronidation in the liver, with greater than 95% of the dose metabolized to hydromorphone-3- glucuronide along with minor amounts of 6-hydroxy reduction metabolites.
Excretion
Only a small amount of the hydromorphone dose is excreted unchanged in the urine. Most of the dose is excreted as hydromorphone-3-glucuronide along with minor amounts of 6-hydroxy reduction metabolites.
Special Populations
Hepatic Impairment
After oral administration of hydromorphone at a single 4 mg dose (2 mg hydromorphone immediate-release tablets), mean exposure to hydromorphone (Cmax and AUC∞) is increased 4-fold in patients with moderate (Child-Pugh Group B) hepatic impairment compared with subjects with normal hepatic function. Patients with moderate hepatic impairment should be started at one-fourth to one-half the recommended starting dose and closely monitored during dose titration. The pharmacokinetics of hydromorphone in patients with severe hepatic impairment has not been studied. A further increase in Cmax and AUC of hydromorphone in this group is expected and should be taken into consideration when selecting a starting dose [see Use in Specific Populations (8.6)].
Renal Impairment
The pharmacokinetics of hydromorphone following an oral administration of hydromorphone at a single 4 mg dose (2 mg hydromorphone immediate-release tablets) are affected by renal impairment. Mean exposure to hydromorphone (Cmax and AUC0-∞) is increased by 2-fold in patients with moderate (CLcr = 40 - 60 mL/min) renal impairment and increased by 4-fold in patients with severe (CLcr< 30 mL/min) renal impairment compared with normal subjects (CLcr> 80 mL/min). In addition, in patients with severe renal impairment, hydromorphone appeared to be more slowly eliminated with a longer terminal elimination half-life (40 hr) compared to patients with normal renal function (15 hr). Start patients with renal impairment on one-fourth to one-half the usual starting dose depending on the degree of impairment. Patients with renal impairment should be closely monitored during dose titration [see Use in Specific Populations (8.7)].
Geriatric Population
In the geriatric population, age has no effect on the pharmacokinetics of hydromorphone.
Sex
Sex has little effect on the pharmacokinetics of hydromorphone. Females appear to have a higher Cmax (25%) than males with comparable AUC0- 24 values. The difference observed in Cmax may not be clinically relevant.
Carcinogenesis
Long term studies in animals to evaluate the carcinogenic potential of hydromorphone have not been conducted.
Mutagenesis
Hydromorphone was positive in the mouse lymphoma assay in the presence of metabolic activation, but was negative in the mouse lymphoma assay in the absence of metabolic activation. Hydromorphone was not mutagenic in the in vitro bacterial reverse mutation assay (Ames assay). Hydromorphone was not clastogenic in either the in vitro human lymphocyte chromosome aberration assay or the in vivo mouse micronucleus assay.
Impairment of Fertility
Reduced implantation sites and viable fetuses were noted at 2.1 times the human daily dose of 32 mg/day in a study in which female rats were treated orally with 1.75, 3.5, or 7 mg/kg/day hydromorphone hydrochloride (0.5, 1.1, or 2.1 times a human daily dose of 24 mg/day (HDD) based on body surface area) beginning 14 days prior to mating through Gestation Day 7 and male rats were treated with the same hydromorphone hydrochloride doses beginning 28 days prior to and throughout mating.
Addiction, Abuse, and Misuse
Inform patients that the use of DILAUDID INJECTION, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose and death [see Warnings and Precautions (5.1)].
Life-Threatening Respiratory Depression
Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when starting DILAUDID INJECTION or when the dosage is increased, and that it can occur even at recommended dosages.
Hyperalgesia and Allodynia
Advise patients to inform their healthcare provider if they experience symptoms of hyperalgesia, including worsening pain, increased sensitivity to pain, or new pain [see Warnings and Precautions (5.5); Adverse Reactions (6.2)].
Serotonin Syndrome
Inform patients that opioids could cause a rare but potentially life-threatening condition called serotonin syndrome resulting from concomitant administration of serotonergic drugs. Warn patients of the symptoms of serotonin syndrome and to seek medical attention right away if symptoms develop after discharge from hospital. Instruct patients to inform their healthcare providers if they are taking, or plan to take serotonergic medications [see Drug Interactions (7)].
Constipation
Advise patients of the potential for severe constipation, including management instructions and when to seek medical attention [see Adverse Reactions (6)].
Healthcare professionals can telephone Fresenius Kabi USA, LLC at 1-800-551-7176 for information or to report adverse events on this product.
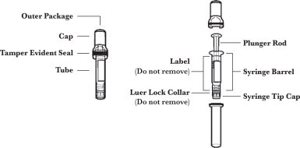
- 1.Once removed from the bundle, inspect the outer packaging by verifying:
- -Integrity of the tube and the cap.
- -Tamper evident seal is intact (outer shrink wrap is not broken).
Do not use if the outer packaging has been damaged.
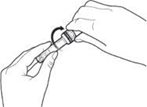
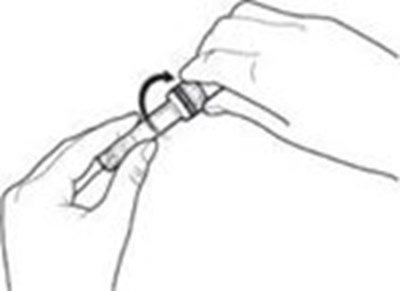
- 2.Hold the outer packaging with both hands. To break the tamper evident seal, hold the tube and the cap close to the seal, and twist until broken. (See Figure 2)
- Figure 2
-
Dilau-img-02.jpg (Dilau Img 02)
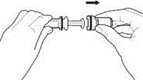
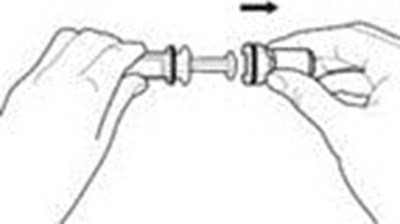
- 3.Remove the cap of the outer packaging by pulling it straight away from the tube to avoid dislodging the plunger rod of the syringe. (See Figure 3)
- Figure 3
-
Dilau-img-03.jpg (Dilau Img 03)
- 4.Remove the syringe from the tube.
- 5.Visually inspect the syringe. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
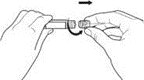
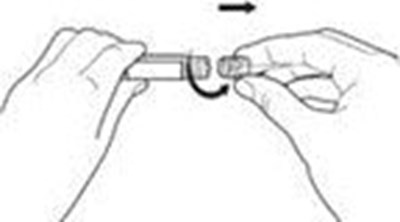
- 6.Twist off the syringe tip cap. Do not remove the plastic wrap label around the luer lock collar. (See Figure 4)
- Figure 4
-
Dilau-img-04.jpg (Dilau Img 04)
- 7.Expel air bubble(s). Adjust the dose (if applicable).
- 8.Administer the dose ensuring that pressure is maintained on the plunger rod during the entire administration.
- 9.Discard the used syringe into an appropriate receptacle.
For more information concerning this drug, please call Fresenius Kabi USA, LLC at 1-800-551-7176.
To report SUSPECTED ADVERSE REACTIONS, contact Fresenius Kabi USA, LLC at 1-800-551-7176 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.

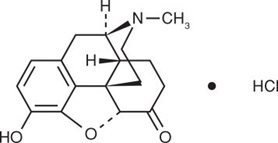
Dilau-img-05.jpg (Dilau Img 05)
Lake Zurich, IL 60047
www.fresenius-kabi.com/us
451594D
Dilaudid is a licensed trademark of Purdue Pharma L.P.
U.S. Patents 9731082, 10661018, 11426522, 10064998, 10792431, 10814059, and 11400206