Other
Cardiovascular Thrombotic Events
- Non-steroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use. [see Warnings and Precautions (5.1)].
- CALDOLOR is contraindicated in the setting of coronary artery bypass graft (CABG) surgery [see Contraindications (4) and Warnings and Precautions (5.1)].
- NSAIDs cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms. Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events [see Warnings and Precautions (5.2)].
- Use the lowest effective dosage for the shortest possible duration.
- Avoid administration of more than one NSAID at a time.
- Avoid use in patients at higher risk unless benefits are expected to outweigh the increased risk of bleeding. For such patients, as well as those with active GI bleeding, consider alternate therapies other than NSAIDs.
- Remain alert for signs and symptoms of GI ulceration and bleeding during NSAID therapy.
- If a serious GI adverse event is suspected, promptly initiate evaluation and treatment, and discontinue CALDOLOR until a serious GI adverse event is ruled out.
- In the setting of concomitant use of low-dose aspirin for cardiac prophylaxis, monitor patients more closely for evidence of GI bleeding [see Drug Interactions (7)].
Gastrointestinal Bleeding, Ulceration and Perforation
For Analgesia (pain):
The dose is 400 mg to 800 mg intravenously every 6 hours as necessary. Infusion time must be at least 30 minutes. Maximum daily dose is 3,200 mg.
For Fever:
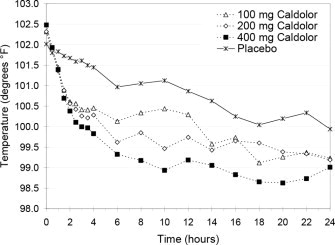
The dose is 400 mg intravenously, followed by 400 mg every 4 to 6 hours or 100 mg to 200 mg every 4 hours as necessary. Infusion time must be at least 30 minutes. Maximum daily dose is 3,200 mg.
For Analgesia (pain) and Fever:
Ages 12 to 17 years
The dose is 400 mg intravenously every 4 to 6 hours as necessary. Infusion time must be at least 10 minutes. Maximum daily dose is 40 mg/kg or 2,400 mg, whichever is less.
Ages 6 months to less than 12 years
The dose is 10 mg/kg intravenously up to a maximum single dose of 400 mg every 4 to 6 hours as necessary. Infusion time must be at least 10 minutes. Maximum daily dose is 40 mg/kg or 2,400 mg, whichever is less.
* Maximum daily dose is 40 mg/kg or 2,400 mg, whichever is less. | ||||
| Age Group | Dose | Dosing Interval | Min infusion time | Max daily dose |
6 months to less than 12 years | 10 mg/kg up to 400 mg max | Every 4 to 6 hours as necessary | 10 minutes | *40 mg/kg or 2,400 mg |
| 12 to 17 years | 400 mg | Every 4 to 6 hours as necessary | 10 minutes | *40 mg/kg or 2,400 mg |
Ages 3 months to less than 6 months
The dose is a single dose at 10 mg/kg intravenously up to a maximum single dose of 100 mg. Infusion time must be at least 10 minutes.
Status Post Coronary Artery Bypass Graft (CABG) Surgery
Two large, controlled clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10-14 days following CABG surgery found an increased incidence of myocardial infarction and stroke. NSAIDs are contraindicated in the setting of CABG [see Contraindications (4)].
Post-MI Patients
Observational studies conducted in the Danish National Registry have demonstrated that patients treated with NSAIDs in the post-MI period were at increased risk of reinfarction, CV-related death, and all-cause mortality beginning in the first week of treatment. In this same cohort, the incidence of death in the first year post-MI was 20 per 100 person years in NSAID-treated patients compared to 12 per 100 person years in non-NSAID exposed patients. Although the absolute rate of death declined somewhat after the first year post-MI, the increased relative risk of death in NSAID users persisted over at least the next four years of follow-up.
Avoid the use of CALDOLOR in patients with a recent MI unless the benefits are expected to outweigh the risk of recurrent CV thrombotic events. If CALDOLOR is used in patients with a recent MI, monitor patients for signs of cardiac ischemia.
Risk Factors for GI Bleeding, Ulceration and Perforation
Patients with a prior history of peptic ulcer disease and/or GI bleeding who used NSAIDs had a greater than 10-fold increased risk for developing a GI bleed compared to patients without these risk factors. Other factors that increase the risk of GI bleeding in patients treated with NSAIDs include longer duration of NSAID therapy; concomitant use of oral corticosteroids, aspirin, anticoagulants, or selective serotonin reuptake inhibitors (SSRIs); smoking; use of alcohol; older age; and poor general health status. Most postmarketing reports of fatal GI events occurred in elderly or debilitated patients. Additionally, patients with advanced liver disease and/or coagulopathy are at increased risk for GI bleeding.
Strategies to Minimize the GI Risks in NSAID-treated patients:
Renal Toxicity
Long-term administration of NSAIDs has resulted in renal papillary necrosis and other renal injury.
Renal toxicity has also been seen in patients in whom renal prostaglandins have a compensatory role in the maintenance of renal perfusion. In these patients, administration of an NSAID may cause a dose dependent reduction in prostaglandin formation and, secondarily, in renal blood flow, which may precipitate overt renal decompensation. Patients at greatest risk of this reaction are those with impaired renal function, dehydration, hypovolemia, heart failure, liver dysfunction, those taking diuretics and ACE inhibitors or ARBs, and the elderly. Discontinuation of NSAID therapy is usually followed by recovery to the pretreatment state.
No information is available from controlled clinical studies regarding the use of CALDOLOR in patients with advanced renal disease. The renal effects of CALDOLOR may hasten the progression of renal dysfunction in patients with preexisting renal disease.
Correct volume status in dehydrated or hypovolemic patients prior to initiating CALDOLOR. Monitor renal function in patients with renal or hepatic impairment, heart failure, dehydration, or hypovolemia during use of CALDOLOR [see Drug Interactions (7)]. Avoid the use of CALDOLOR in patients with advanced renal disease unless the benefits are expected to outweigh the risk of worsening renal function. If CALDOLOR is used in patients with advanced renal disease, monitor patients for signs of worsening renal function.
Hyperkalemia
Increases in serum potassium concentration, including hyperkalemia, have been reported with use of NSAIDs, even in some patients without renal impairment. In patients with normal renal function, these effects have been attributed to a hyporeninemic-hypoaldosteronism state.
Premature Closure of Fetal Ductus Arteriosus
Avoid use of NSAIDs, including CALDOLOR, in pregnant women at about 30 weeks gestation and later. NSAIDs, including CALDOLOR, increase the risk of premature closure of the fetal ductus arteriosus at approximately this gestational age.
Oligohydramnios/Neonatal Renal Impairment
Use of NSAIDs, including CALDOLOR, at about 20 weeks gestation or later in pregnancy may cause fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation.
Oligohydramnios is often, but not always, reversible with treatment discontinuation. Complications of prolonged oligohydramnios may, for example, include limb contractures and delayed lung maturation. In some postmarketing cases of impaired neonatal renal function, invasive procedures such as exchange transfusion or dialysis were required.
If NSAID treatment is necessary between about 20 weeks and 30 weeks gestation, limit CALDOLOR use to the lowest effective dose and shortest duration possible. Consider ultrasound monitoring of amniotic fluid if CALDOLOR treatment extends beyond 48 hours. Discontinue CALDOLOR if oligohydramnios occurs and follow up according to clinical practice [see Use in Specific Populations (8.1)].
Adult Population
During clinical development, 560 patients were exposed to CALDOLOR, 438 in pain and 122 with fever. In the pain studies, CALDOLOR was started intra-operatively and administered at a dose of 400 mg or 800 mg every six hours for up to three days. In the fever studies, CALDOLOR was administered at doses of 100 mg, 200 mg, or 400 mg every four or six hours for up to 3 days. The most frequent type of adverse reaction occurring with oral ibuprofen is gastrointestinal.
Pain Studies
The incidence rates of adverse reactions listed in the following table were derived from multi-center, controlled clinical studies in post-operative patients comparing CALDOLOR to placebo in patients also receiving morphine as needed for post-operative pain.
* All patients received concomitant morphine during these studies. | |||
| Event | CALDOLOR | Placebo (N=287) | |
| 400 mg (N=134) | 800 mg (N=304) | ||
| Any Reaction | 118 (88%) | 260 (86%) | 258 (90%) |
| Nausea | 77 (57%) | 161 (53%) | 179 (62%) |
| Vomiting | 30 (22%) | 46 (15%) | 50 (17%) |
| Flatulence | 10 (7%) | 49 (16%) | 44 (15%) |
| Headache | 12 (9%) | 35 (12%) | 31 (11%) |
| Hemorrhage | 13 (10%) | 13 (4%) | 16 (6%) |
| Dizziness | 8 (6%) | 13 (4%) | 5 (2%) |
| Edema peripheral | 1 (<1%) | 9 (3%) | 4 (1%) |
| Urinary retention | 7 (5%) | 10 (3%) | 10 (3%) |
| Anemia | 5 (4%) | 7 (2%) | 6 (2%) |
| Decreased hemoglobin | 4 (3%) | 6 (2%) | 3 (1%) |
| Dyspepsia | 6 (4%) | 4 (1%) | 2 (<1%) |
| Wound hemorrhage | 4 (3%) | 4 (1%) | 4 (1%) |
| Abdominal discomfort | 4 (3%) | 2 (<1%) | 0 |
| Cough | 4 (3%) | 2 (<1%) | 1 (<1%) |
| Hypokalemia | 5 (4%) | 3 (<1%) | 8 (3%) |
Fever Studies
Fever studies were conducted in febrile hospitalized patients with malaria and febrile hospitalized patients with varying causes of fever. In hospitalized febrile patients with malaria, the adverse reactions observed in at least two CALDOLOR-treated patients included abdominal pain and nasal congestion.
In hospitalized febrile patients (all causes), adverse reactions observed in more than two patients in any given treatment group are presented in the table below.
| Event | CALDOLOR | Placebo N=28 | ||
| 100 mg N=30 | 200 mg N=30 | 400 mg N=31 | ||
| Any Reaction | 27 (87%) | 25 (83%) | 23 (74%) | 25 (89%) |
| Anemia | 5 (17%) | 6 (20%) | 11 (36%) | 4 (14%) |
| Eosinophilia | 7 (23%) | 7 (23%) | 8 (26%) | 7 (25%) |
| Hypokalemia | 4 (13%) | 4 (13%) | 6 (19%) | 5 (18%) |
| Hypoproteinemia | 3 (10%) | 0 | 4 (13%) | 2 (7%) |
| Neutropenia | 2 (7%) | 2 (7%) | 4 (13%) | 2 (7%) |
| Blood urea increased | 0 | 0 | 3 (10%) | 0 |
| Hypernatremia | 2 (7%) | 0 | 3 (10%) | 0 |
| Hypertension | 0 | 0 | 3 (10%) | 0 |
| Hypoalbuminemia | 3 (10%) | 1 (3%) | 3 (10%) | 1 (4%) |
| Hypotension | 0 | 2 (7%) | 3 (10%) | 1 (4%) |
| Diarrhea | 3 (10%) | 3 (10%) | 2 (7%) | 2 (7%) |
| Pneumonia bacterial | 3 (10%) | 1 (3%) | 2 (7%) | 0 |
| Blood LDH increased | 3 (10%) | 2 (7%) | 1 (3%) | 1 (4%) |
| Thrombocythemia | 3 (10%) | 2 (7%) | 1 (3%) | 0 |
| Bacteremia | 4 (13%) | 0 | 0 | 0 |
Pediatric Population
A total of 143 pediatric patients ages 6 months and older have received CALDOLOR in controlled clinical trials. The most common adverse reactions (incidence greater than or equal to 2%) in pediatric patients treated with CALDOLOR were infusion site pain, vomiting, nausea, anemia and headache.
Twenty-one hospitalized patients ages 3 months to less than 6 months were treated with CALDOLOR for pain or fever in an open-label, non-controlled clinical study; 18 of 21 patients were treated with a single dose.
Risk Summary
Use of NSAIDs, including CALDOLOR, can cause premature closure of the fetal ductus arteriosus and fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. Because of these risks, limit dose and duration of CALDOLOR use between about 20 and 30 weeks of gestation, and avoid CALDOLOR use at about 30 weeks of gestation and later in pregnancy (see Clinical Considerations, Data).
Premature Closure of Fetal Ductus Arteriosus
Use of NSAIDs, including CALDOLOR, at about 30 weeks gestation or later in pregnancy increases the risk of premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment
Use of NSAIDs at about 20 weeks gestation or later in pregnancy has been associated with cases of fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment.
Data from observational studies regarding other potential embryofetal risks of NSAID use in women in the first or second trimesters of pregnancy are inconclusive.
Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization. In animal studies, administration of prostaglandin synthesis inhibitors such as ibuprofen resulted in increased pre- and post-implantation loss. Prostaglandins also have been shown to have an important role in fetal kidney development. In published animal studies, prostaglandin synthesis inhibitors have been reported to impair kidney development when administered at clinically relevant doses.
The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations
Fetal/Neonatal Adverse Reactions
Premature Closure of Fetal Ductus Arteriosus:
Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy, because NSAIDs, including CALDOLOR, can cause premature closure of the fetal ductus arteriosus (see Data).
Oligohydramnios/Neonatal Renal Impairment:
If an NSAID is necessary at about 20 weeks gestation or later in pregnancy, limit the use to the lowest effective dose and shortest duration possible. If CALDOLOR treatment extends beyond 48 hours, consider monitoring with ultrasound for oligohydramnios. If oligohydramnios occurs, discontinue CALDOLOR and follow up according to clinical practice (see Data).
Labor or Delivery
There are no studies on the effects of CALDOLOR during labor or delivery. In animal studies, NSAIDs, including ibuprofen, inhibit prostaglandin synthesis, cause delayed parturition, and increase the incidence of stillbirth.
Data
Human Data
Premature Closure of Fetal Ductus Arteriosus:
Published literature reports that the use of NSAIDs at about 30 weeks of gestation and later in pregnancy may cause premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment:
Published studies and postmarketing reports describe maternal NSAID use at about 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation. In many cases, but not all, the decrease in amniotic fluid was transient and reversible with cessation of the drug. There have been a limited number of case reports of maternal NSAID use and neonatal renal dysfunction without oligohydramnios, some of which were irreversible. Some cases of neonatal renal dysfunction required treatment with invasive procedures, such as exchange transfusion or dialysis.
Methodological limitations of these postmarketing studies and reports include lack of a control group; limited information regarding dose, duration, and timing of drug exposure; and concomitant use of other medications. These limitations preclude establishing a reliable estimate of the risk of adverse fetal and neonatal outcomes with maternal NSAID use. Because the published safety data on neonatal outcomes involved mostly preterm infants, the generalizability of certain reported risks to the full-term infant exposed to NSAIDs through maternal use is uncertain.
Animal Data
In a published study, female rabbits given 7.5, 20, or 60 mg/kg ibuprofen (0.04, 0.12, or 0.36-times the maximum recommended human daily dose of 3200 mg of ibuprofen based on body surface area) from Gestation Days 1 to 29, no clear treatment-related adverse developmental effects were noted. This dose was associated with significant maternal toxicity (stomach ulcers, gastric lesions). In the same publication, female rats were administered 7.5, 20, 60, 180 mg/kg ibuprofen (0.02, 0.06, 0.18, 0.54-times the maximum daily dose) did not result in clear adverse developmental effects. Maternal toxicity (gastrointestinal lesions) was noted at 20 mg/kg and above.
In a published study, rats were orally dosed with 300 mg/kg ibuprofen (0.912-times the maximum human daily dose of 3200 mg based on body surface area) during Gestation Days 9 and 10 (critical time points for heart development in rats). Ibuprofen treatment resulted in an increase in the incidence of membranous ventricular septal defects. This dose was associated with significant maternal toxicity including gastrointestinal toxicity. One incidence each of a membranous ventricular septal defect and gastroschisis was noted in fetuses from rabbits treated with 500 mg/kg (3-times the maximum human daily dose) from Gestation Day 9-11.
Risk Summary
No lactation studies have been conducted with CALDOLOR; however, limited published literature reports that, following oral administration, ibuprofen is present in human milk at relative infant doses of 0.06% to 0.6% of the maternal weight-adjusted daily dose. There are no reports of adverse effects on the breastfed infant and no effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for CALDOLOR and any potential adverse effects on the breastfed infant from the CALDOLOR or from the underlying maternal condition.
Infertility
Females
Based on the mechanism of action, the use of prostaglandin-mediated NSAIDs, including CALDOLOR, may delay or prevent rupture of ovarian follicles, which has been associated with reversible infertility in some women. Published animal studies have shown that administration of prostaglandin synthesis inhibitors has the potential to disrupt prostaglandin- mediated follicular rupture required for ovulation. Small studies in women treated with NSAIDs have also shown a reversible delay in ovulation. Consider withdrawal of NSAIDs, including CALDOLOR in women who have difficulties conceiving or who are undergoing investigation of infertility.
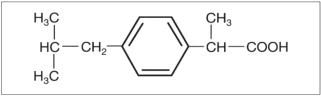
CALDOLOR 800 mg/8 mL (100 mg/mL) vial: Each 1 mL of solution contains 100 mg of ibuprofen, USP, 78 mg of arginine (at a molar ratio of 0.92:1 arginine:ibuprofen), and 10% arginine solution and hydrochloric acid as pH adjusters in Water for Injection, USP. The solution pH is about 7.4.
CALDOLOR 800 mg/200 mL (4 mg/mL) polypropylene flexible bag: Each 1 mL of solution contains 4 mg of ibuprofen, USP, 3.11 mg of dibasic sodium phosphate, as a buffering agent; 6.30 mg sodium chloride as a tonicity agent; and sodium hydroxide as a pH adjuster in Water for Injection, USP. The solution is iso-osmotic with an approximate pH of 7.4.
CALDOLOR is sterile and is intended for intravenous administration only.
Drug Interaction Studies
Aspirin: When NSAIDs were administered with aspirin, the protein binding of NSAIDs were reduced, although the clearance of free NSAID was not altered. The clinical significance of this interaction is not known. See Table 3 for clinically significant drug interactions of NSAIDs with aspirin [see Drug Interactions (7)].
Carcinogenesis
Long-term studies in animals to evaluate the carcinogenic potential of ibuprofen have not been conducted.
Mutagenesis
In published studies, ibuprofen was not mutagenic in the in vitro bacterial reverse mutation assay (Ames assay).
Impairment of Fertility
In a published study, dietary administration of ibuprofen to male and female rats 8-weeks prior to and during mating at dose levels of 20 mg/kg (0.06-times the MRHD based on body surface area comparison) did not impact male or female fertility or litter size.
In other studies, adult mice were administered ibuprofen intraperitoneally at a dose of 5.6 mg/kg/day (0.0085-times the MRHD based on body surface area comparison) for 35 or 60 days in males and 35 days in females. There was no effect on sperm motility or viability in males, but decreased ovulation was reported in females.
Cardiovascular Thrombotic Events
Advise patients to be alert for the symptoms of cardiovascular thrombotic events, including chest pain, shortness of breath, weakness, or slurring of speech, and to report any of these symptoms to their health care provider immediately [see Warnings and Precautions (5.1)].
Gastrointestinal Bleeding, Ulceration, and Perforation
Advise patients to report symptoms of ulcerations and bleeding, including epigastric pain, dyspepsia, melena, and hematemesis to their health care provider. In the setting of concomitant use of low-dose aspirin for cardiac prophylaxis, inform patients of the increased risk for and the signs and symptoms of GI bleeding [see Warnings and Precautions (5.2)].
Hepatotoxicity
Inform patients of the warning signs and symptoms of hepatotoxicity (e.g., nausea, fatigue, lethargy, pruritus, diarrhea, jaundice, right upper quadrant tenderness, and “flu-like” symptoms). If these occur, instruct patients to stop CALDOLOR and seek immediate medical therapy [see Warnings and Precautions (5.3)].
Heart Failure and Edema
Advise patients to be alert for the symptoms of congestive heart failure including shortness of breath, unexplained weight gain, or edema and to contact their healthcare provider if such symptoms occur [see Warnings and Precautions (5.5)].
Anaphylactic Reactions
Inform patients of the signs of an anaphylactic reaction (e.g., difficulty breathing, swelling of the face or throat). Instruct patients to seek immediate emergency help if these occur [see Contraindications (4) and Warnings and Precautions (5.7)].
Serious Skin Reactions including DRESS
Advise patients to stop taking CALDOLOR immediately if they develop any type of rash or fever and to contact their healthcare provider as soon as possible [see Warnings and Precautions (5.9, 5.10].
Female Fertility
Advise females of reproductive potential who desire pregnancy that NSAIDs, including CALDOLOR, may be associated with a reversible delay in ovulation [see Use in Specific Populations (8.3)]
Fetal Toxicity
Inform pregnant women to avoid use of CALDOLOR and other NSAIDs starting at 30 weeks gestation because of the risk of the premature closing of the fetal ductus arteriosus. If treatment with CALDOLOR is needed for a pregnant woman between about 20 to 30 weeks gestation, advise her that she may need to be monitored for oligohydramnios, if treatment continues for longer than 48 hours I [see Warnings and Precautions (5.10) and Use in Specific Populations (8.1)].
Avoid Concomitant Use of NSAIDs
Inform patients that the concomitant use of CALDOLOR with other NSAIDs or salicylates (e.g., diflunisal, salsalate) is not recommended due to the increased risk of gastrointestinal toxicity, and little or no increase in efficacy [see Warnings and Precautions (5.2) and Drug Interactions (7)]. Alert patients that NSAIDs may be present in “over the counter” medications for treatment of colds, fever, or insomnia.
Use of NSAIDS and Low-Dose Aspirin
Inform patients not to use low-dose aspirin concomitantly with CALDOLOR until they talk to their healthcare provider [see Drug Interactions (7)].
Manufactured for:
Cumberland Pharmaceuticals Inc.
Nashville, TN 37203
US Patent Number 6,727,286, 8,871,810, 8,735,452, 9,012,508, 9,072,661, 9,072,710, 9,114,068, 9,138,404, 9,295,639, and 9,649,284
CALDOLOR® is a registered trademark of Cumberland Pharmaceuticals Inc.